Item 1: About you
Your SSN, or Medicare Number if you already have Part B, your name and name at birth if different, sex, date of birth, state or country of birth, mailing address, permanent residence, phone and email.
CMS-18-F-5
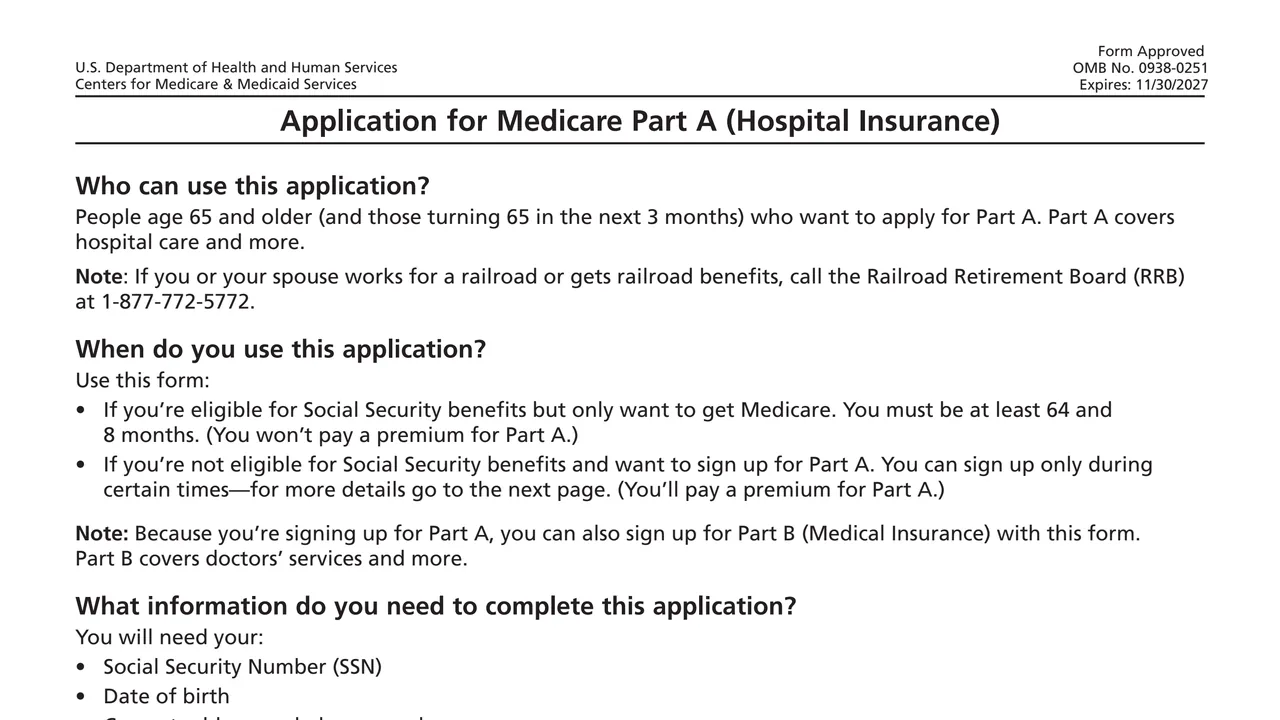
Application for Medicare Part A (Hospital Insurance)

Form CMS-18-F-5 is the Application for Medicare Part A (Hospital Insurance) from the Centers for Medicare & Medicaid Services, part of the U.S. Department of Health and Human Services. The form says it is for people age 65 and older, and those turning 65 in the next 3 months, who want to apply for Part A. It lists two uses: people eligible for Social Security benefits who only want Medicare, and people not eligible for Social Security benefits who want to sign up for Part A and, the form says, pay a premium for it.
The form notes that because you're signing up for Part A, you can also sign up for Part B (Medical Insurance) with it. The two application pages ask about you, your work history, citizenship, marital status, premium Part A and Part B enrollment, current or prior health coverage, and signatures. Step-by-step instructions follow on pages 3 to 5.
The completed, signed application (pages 1 and 2) goes to your local Social Security office, and the CMS page says by mail, fax or in person. You can fill it out free in your browser on this page and download the result without an account.
Your SSN, or Medicare Number if you already have Part B, your name and name at birth if different, sex, date of birth, state or country of birth, mailing address, permanent residence, phone and email.
Total earnings last year and expected earnings this year, with none written if there are none, and whether you worked in the railroad industry after January 1, 1937.
Whether you are a U.S. citizen and, if not, lawful presence and residence dates, whether you resided in the U.S. without a break for 5 years, your addresses for the last 5 years and time outside the U.S.
Your current spouse's name, date of birth, SSN and date of marriage, and any former marriage that lasted 10 or more years or ended in death.
Whether you still want Part A if you have to pay a premium, whether you want Part B, Medicaid, employer, union or international volunteer health coverage with dates, and OPM retirement benefits.
A written signature and date. If the form is signed by mark (X), a witness who knows the person applying also signs, with their name and the date.
Your SSN, date of birth, current address and phone number, and work history. Signing up for premium Part A or for Part B during a Special Enrollment Period also calls for Form CMS-L564 completed by your employer, the form says.
Enter your personal information, earnings, citizenship and marital status. The step-by-step instructions on pages 3 to 5 say which items to skip based on your answers.
Answer item 5. The instructions say that if you don't qualify for Part A without a premium and want to buy it, you also sign up for Part B.
Answer items 6a to 6h. The instructions say item 6d only lists work and health coverage since you turned 65, with all dates as mm/dd/yyyy.
Sign item 7b in writing, not printed, and date it. A form signed by mark (X) also needs a witness's name, signature and date.
Send the completed, signed application (pages 1 and 2) to your local Social Security office. The CMS page says by mail, fax or in person. Find an office at SSA.gov/locator.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
To your local Social Security office, by mail, fax or in person according to the CMS page. The CMS address in the Paperwork Reduction Act notice is for comments on the form only, and the form says anything else sent there is destroyed.
The form says it lasts 7 months, beginning 3 months before the month you turn 65 and ending 3 months after, and that coverage begins the month after you sign up.
January 1 to March 31 each year, with coverage starting the month after you sign up. The form says that in most cases a late enrollment penalty is added to the monthly premium, and it describes the Part A and Part B penalty rules.
The form describes one for people covered under a group health plan based on current employment, open while covered and for 8 months after the coverage or employment ends, whichever happens first, and one for some international volunteers. It says COBRA and retiree plans don't count as coverage based on current employment.
The form says that people applying after age 65 stop contributing to an HSA before applying for Medicare to avoid IRS penalties, and that premium-free Part A starts up to 6 months back from when you apply, but not earlier than the month you turned 65.
Social Security: 1-800-772-1213, TTY 1-800-325-0778, with Spanish service by pressing 2, or your local office at SSA.gov/locator. The form estimates an average of 15 minutes per response.

CMS-L564
45 fields, 2 pages

CMS-40B
47 fields, 3 pages

CMS-43
155 fields, 6 pages

CMS-10797
72 fields, 6 pages
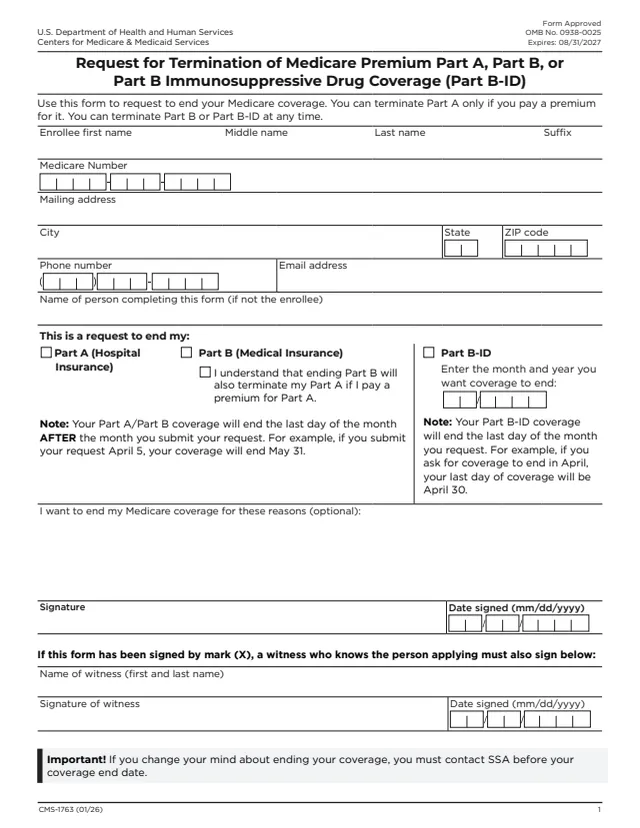
CMS-1763
29 fields, 2 pages
The form names who can use it and when.
No tool matches that search.
The form says people age 65 and older, and those turning 65 in the next 3 months, who want to apply for Part A.
Yes. The form says that because you're signing up for Part A, you can also sign up for Part B. Item 5b asks whether you want Part B, and the form notes a monthly premium for it.
The form says people eligible for Social Security benefits who only want Medicare won't pay a premium for Part A, and people not eligible for Social Security benefits who sign up will pay one. It does not list amounts.
The form says to send the completed, signed application (pages 1 and 2) to your local Social Security office. The CMS page says by mail, fax or in person. Find an office at SSA.gov/locator.
The form lists Form CMS-L564, completed by your employer, if you're signing up for Part A and have to pay a premium for it, or for Part B, during a Special Enrollment Period.
The form says that if you're applying after age 65, stop contributing to your HSA before applying for Medicare to avoid IRS penalties. It points to IRS.gov for more on HSAs.
If the application is signed by mark (X), the form says a witness who knows the person applying also signs, and enters their name and the date signed.
