Enrollee information
First, middle and last name, suffix, Medicare Number, mailing address, city, state, ZIP code, phone number and email address.
CMS-1763
Request for Termination of Premium Hospital Insurance of Supplementary Medical Insurance
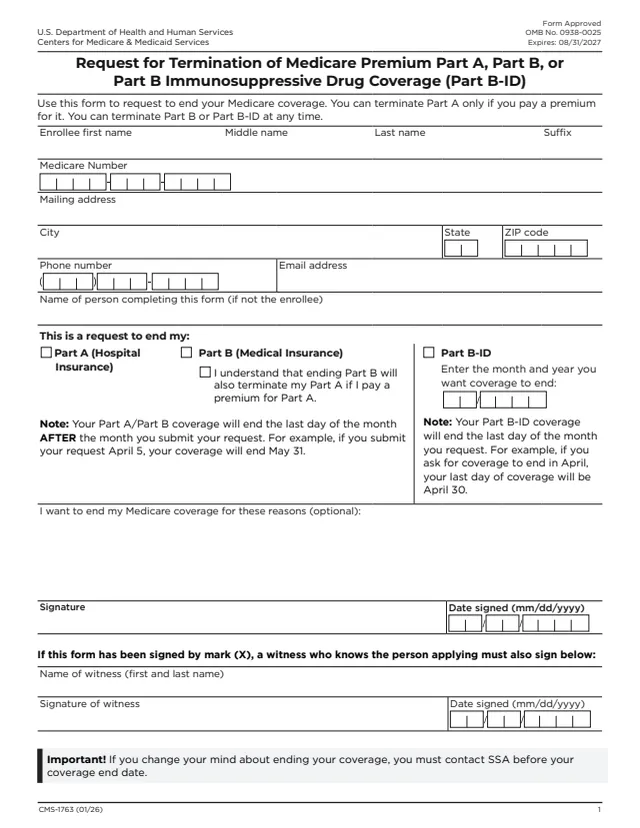
Form CMS-1763 is the Request for Termination of Medicare Premium Part A, Part B, or Part B Immunosuppressive Drug Coverage (Part B-ID) from the Centers for Medicare & Medicaid Services (CMS), part of the U.S. Department of Health and Human Services. The form says to use it to request to end your Medicare coverage. It says Part A can be ended only if you pay a premium for it, and Part B or Part B-ID can be ended at any time.
The one-page form asks for the enrollee's name, Medicare Number, mailing address, phone and email, the name of anyone completing it for the enrollee, which coverage to end, optional reasons, and a signature, with a witness if it is signed by mark (X). Notes on the form explain when each kind of coverage ends.
The completed, signed form goes to your local Social Security office by mail or fax. You can fill it out free in your browser on this page and download the result without an account.
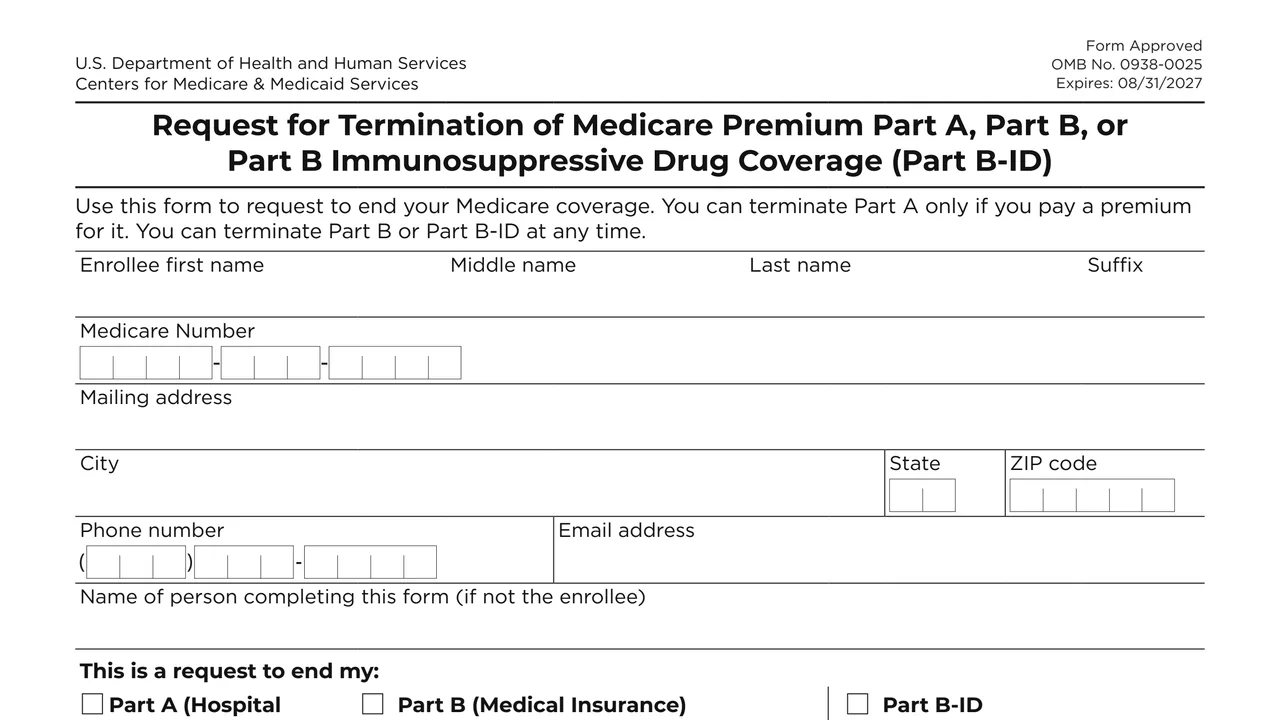
First, middle and last name, suffix, Medicare Number, mailing address, city, state, ZIP code, phone number and email address.
The name of the person completing this form, if it is not the enrollee.
Boxes for Part A (Hospital Insurance), Part B (Medical Insurance) and Part B-ID, with a field for the month and year you want Part B-ID coverage to end.
Notes say Part A or Part B coverage ends the last day of the month after the month you submit the request, and Part B-ID coverage ends the last day of the month you request.
Optional reasons for ending coverage, the signature and date signed (mm/dd/yyyy), and the witness name, signature and date if the form is signed by mark (X).
The form says Part A can be ended only if a premium is paid for it, while Part B and Part B-ID can be ended at any time.
Enter the enrollee's name, Medicare Number, mailing address, phone and email, and the name of the person completing the form if it is not the enrollee.
Check Part A, Part B or Part B-ID. For Part B-ID, enter the month and year you want coverage to end.
The form marks the reasons for ending Medicare coverage as optional.
Sign and enter the date signed. A form signed by mark (X) also needs a witness's name, signature and date.
Mail or fax the completed, signed form to your local Social Security office. Find an office at SSA.gov/locator.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
To your local Social Security office by mail or fax. Find an office at SSA.gov/locator. The CMS address on page 2 is for comments on the time estimate and the form, not for requests.
The last day of the month after the month you submit the request. The form's example: a request submitted April 5 ends coverage May 31.
The last day of the month you request. The form's example: asking for coverage to end in April makes April 30 the last day of coverage.
The form says that if you change your mind about ending coverage, contact SSA before your coverage end date.
The form estimates an average of 10 minutes per response, including reviewing instructions and gathering the information.

CMS-40B
47 fields, 3 pages

CMS-10798
32 fields, 3 pages

CMS-L564
45 fields, 2 pages

CMS-10106
44 fields, 3 pages

CMS-1490S
49 fields, 18 pages

CMS-20027
20 fields, 1 page
The form is for people who want to end certain Medicare coverage. It says which coverage can be ended and when.
No tool matches that search.
Only premium Part A. The form says you can terminate Part A only if you pay a premium for it.
The form says Part A or Part B ends the last day of the month after the month you submit the request, for example May 31 for a request submitted April 5. Part B-ID ends the last day of the month you request.
The form says ending Part B also terminates Part A if you pay a premium for Part A.
The form says to mail or fax the completed, signed form to your local Social Security office. Find an office near you at SSA.gov/locator.
The form says to contact SSA before your coverage end date if you change your mind about ending your coverage.
No. The form marks the reasons for ending Medicare coverage as optional.
The form has a field for the name of the person completing it, if not the enrollee. If the form is signed by mark (X), a witness who knows the person also signs and dates it.