Information page
What Part B-ID covers, when it can be signed up for and when it starts, the mailing address, help phone numbers and where to get the form in another format.
CMS-10798
Application for Enrollment in Part B Immunosuppressive Drug Coverage

Form CMS-10798 is the Application for Medicare Part B Immunosuppressive Drug Coverage from the Centers for Medicare & Medicaid Services. The form says it is for people who only have Medicare because of End-Stage Renal Disease (ESRD) and who lost, or will be losing, their Medicare coverage after a kidney transplant. It describes Part B-ID as coverage that helps pay for immunosuppressive drugs beyond 36 months after a kidney transplant, and says it covers only those drugs and no other items or services.
The one page application asks for a Social Security Number or Medicare Number, name, addresses and phone number. The applicant attests to not having certain other coverage, answers whether they will notify Social Security within 60 days of getting such coverage, and signs. The form says Part B-ID has a monthly premium and an annual deductible. It does not list amounts.
The completed, signed form is mailed to the Social Security Administration address printed on it, and the form says Part B-ID can also be applied for by phone. You can fill it out free in your browser on this page and download the result without an account.

What Part B-ID covers, when it can be signed up for and when it starts, the mailing address, help phone numbers and where to get the form in another format.
Social Security Number or Medicare Number, if the applicant has one, and first, middle and last name and suffix.
Home address (left blank if there is none), mailing address if different, phone number and an optional email address, with a box authorizing Social Security and Medicare to send emails about benefits and coverage.
A statement that the applicant has no Employer Group Health Plan or Individual Health Plan, no TRICARE for Life, no Medicaid or CHIP that includes immunosuppressive drugs, and no VA enrollment or eligibility for those drugs from the VA.
A Yes or No answer to whether the applicant will notify Social Security within 60 days of obtaining any of the excluded coverages.
A statement about false statements, with the text of 18 U.S. Code 1035 in a footnote, then the signature and date signed (mm/dd/yyyy), plus a witness block for a signature by mark.
An information page comes before the one page application, followed by a page with the mailing address, Privacy Act and PRA statements.
It says who Part B-ID is for, what it covers, when it starts and that it has a monthly premium and an annual deductible.
Enter the Social Security Number or the Medicare Number, then the full name.
Enter a home address or leave it blank if there is none, a mailing address if different, a phone number and, optionally, an email address.
Read the list of excluded coverage and answer Yes or No to the question about notifying Social Security within 60 days.
Sign and enter the date. A form signed by mark (X) also needs a witness's name, signature and date.
The form says to mail the completed, signed form to Social Security Administration, Office of Central Operations, PO Box 32914, Baltimore, Maryland 21298.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
Social Security Administration, Office of Central Operations, PO Box 32914, Baltimore, Maryland 21298. The CMS address in the PRA statement is for comments on the form only, and the form says not to send applications there.
The form says Part B-ID can also be applied for by calling 1-877-465-0355 (TTY 1-800-325-0778).
The form says enrolling before Medicare coverage ends starts Part B-ID the month after Medicare ends. Enrolling after Medicare ends starts it the month after enrollment.
The form says there is a monthly premium and an annual deductible for Part B-ID. It does not list amounts and points to Medicare.gov/basics/end-stage-renal-disease for more information.
Social Security: 1-800-772-1213, TTY 1-800-325-0778, with Spanish service by pressing 2. In person help is at local Social Security offices (SSA.gov/locator), and free counseling from your State Health Insurance Assistance Program at shiphelp.org.
The form estimates an average of 10 minutes per response. Medicare information in large print, braille or audio is available through 1-800-MEDICARE (1-800-633-4227), TTY 1-877-486-2048.

CMS-43
155 fields, 6 pages

CMS-40B
47 fields, 3 pages

CMS-10797
72 fields, 6 pages

CMS-18-F-5
127 fields, 7 pages
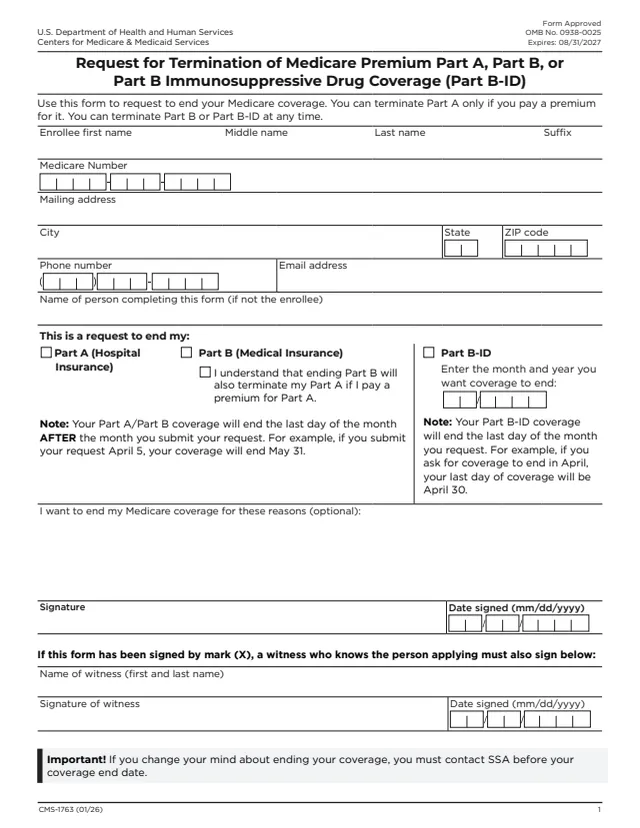
CMS-1763
29 fields, 2 pages

CMS-10106
44 fields, 3 pages
The form's first page says who it is for and when it can be used.
No tool matches that search.
The form says it is for people who only have Medicare because of End-Stage Renal Disease and lost, or will be losing, their Medicare coverage after a kidney transplant. It also says Part B-ID is only for people without certain other coverage, like a group health plan, TRICARE, or Medicaid that covers immunosuppressive drugs.
The form gives Social Security Administration, Office of Central Operations, PO Box 32914, Baltimore, Maryland 21298.
The form says yes, by calling 1-877-465-0355. TTY users can call 1-800-325-0778.
The form says it can be signed up for anytime. Enrolling before Medicare coverage ends starts Part B-ID the month after Medicare ends; enrolling after starts it the month after enrollment.
The form says it helps pay for immunosuppressive drugs beyond 36 months after a kidney transplant, covers only those drugs and no other items or services, and isn't a substitute for full health coverage.
The form says there is a monthly premium and an annual deductible. It does not list amounts.
The form asks a Yes or No question: whether you will notify Social Security within 60 days of obtaining any of the excluded coverages it lists.