Beneficiary and claim
The beneficiary's name and Medicare number, the item or service being appealed, and the date it was received.
CMS-20027
MEDICARE REDETERMINATION REQUEST FORM

Form CMS-20027 is the Medicare Redetermination Request Form from the Centers for Medicare & Medicaid Services. Its title calls it the 1st level of appeal: it asks for a redetermination of an initial determination on a Medicare claim for an item or service. The form is marked OMB Exempt.
The form identifies the beneficiary, the item or service being appealed and the date of the initial determination notice. It then asks why the person appealing does not agree with the decision and what additional information Medicare should consider. The person appealing can be the beneficiary, a provider or supplier, or a representative.
The form asks for a copy of the initial determination notice and for any evidence, or a statement of what will be sent and when. You can fill it out free in your browser on this page and download the result without an account.
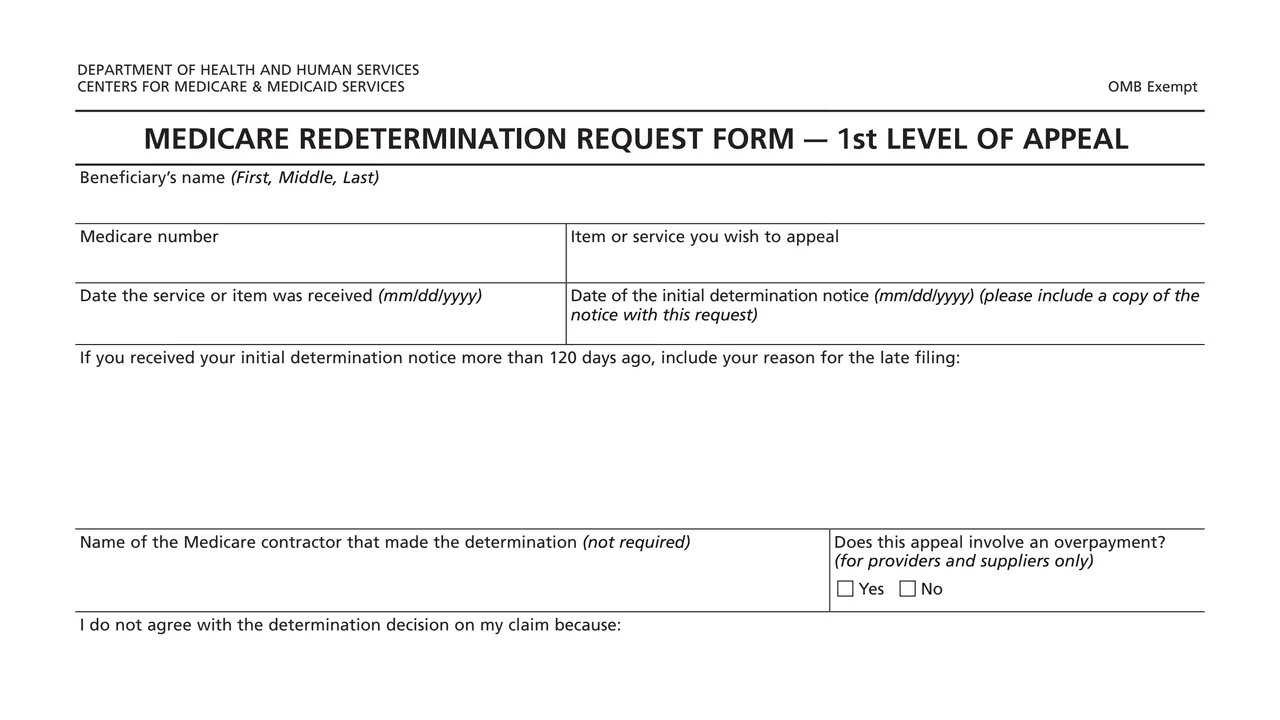
The beneficiary's name and Medicare number, the item or service being appealed, and the date it was received.
The date of the initial determination notice, a late filing reason if that notice came more than 120 days ago, and the name of the Medicare contractor that made the determination, which is not required.
A yes or no box asking whether the appeal involves an overpayment, for providers and suppliers only.
Space to explain why the person appealing does not agree with the determination, and space for additional information Medicare should consider.
A choice between I have evidence to submit and I do not have evidence to submit.
Beneficiary, provider or supplier, or representative, with name, street address, city, state, ZIP code and phone, plus an optional email and date of appeal.
The form asks for the date of the notice and says to include a copy of it with the request.
Enter the beneficiary's name, Medicare number, the item or service being appealed and the date it was received.
Write why you do not agree with the determination and any additional information Medicare should consider. A notice older than 120 days also needs a reason for the late filing.
Attach the evidence, or a statement explaining what you intend to submit and when. The form says more evidence can come later, but all evidence has to be received before the redetermination is issued.
Check beneficiary, provider or supplier, or representative, and add the name, street address and telephone number.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form does not print a mailing address. It asks for the name of the Medicare contractor that made the determination, which is not required, and for a copy of the initial determination notice.
If the initial determination notice was received more than 120 days ago, the form asks for the reason for the late filing.
Additional evidence may be sent later, but the form says all evidence must be received before the redetermination is issued.
The form says the information is collected under section 1869(a)(3) of the Social Security Act and used to document the appeal. Giving it is voluntary, but leaving out any part may affect the determination of the appeal.

CMS-10106
44 fields, 3 pages

CMS-1490S
49 fields, 18 pages

CMS-40B
47 fields, 3 pages

CMS-L564
45 fields, 2 pages
The form has three boxes for the person appealing.
No tool matches that search.
The form's title calls it the 1st level of appeal. Form CMS-20027 asks for a redetermination of the initial determination on a Medicare claim for an item or service.
The form asks for a reason for late filing if the initial determination notice was received more than 120 days ago.
The form asks for the date of the initial determination notice and says to include a copy of the notice with the request.
Yes. The form says additional evidence may be submitted later, but all evidence must be received before the redetermination is issued. It asks for a statement of what you intend to submit and when.
The form lets the person appealing be the beneficiary, a provider or supplier, or a representative.
No. The form marks the name of the Medicare contractor that made the determination as not required.