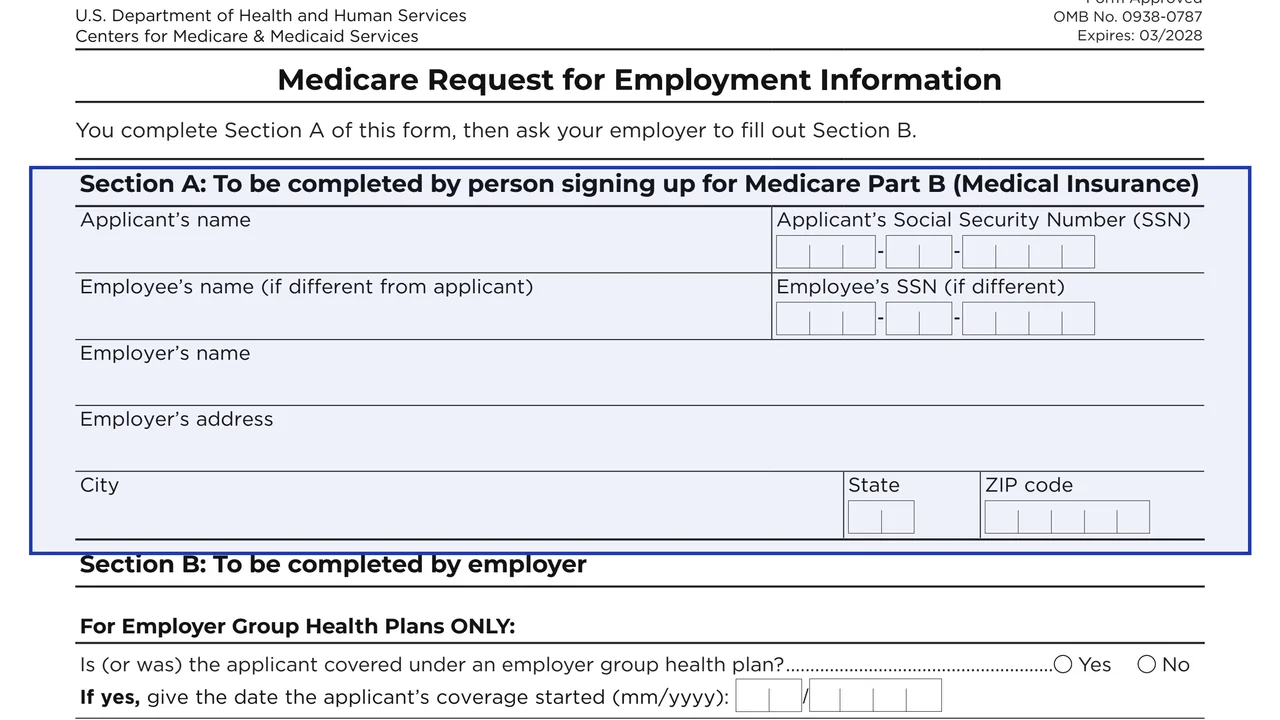
Section A: Applicant
The applicant's name and Social Security Number, the employee's name and SSN if different, and the employer's name and address.
CMS-L564
Medicare Request for Employment Information

Form CMS-L564 is the Medicare Request for Employment Information from the Centers for Medicare & Medicaid Services, part of the U.S. Department of Health and Human Services. The form says it is used to show proof of group health plan coverage based on current employment so you can enroll in Medicare. You complete Section A, then ask your employer to fill out Section B.
The form goes with Form CMS-40B, the request to enroll in Medicare Part B. Item 3 of CMS-40B asks for dates of employment and health coverage and says to have your employer fill out CMS-L564 and return it with the application. Both forms are mailed or faxed together to your local Social Security office.
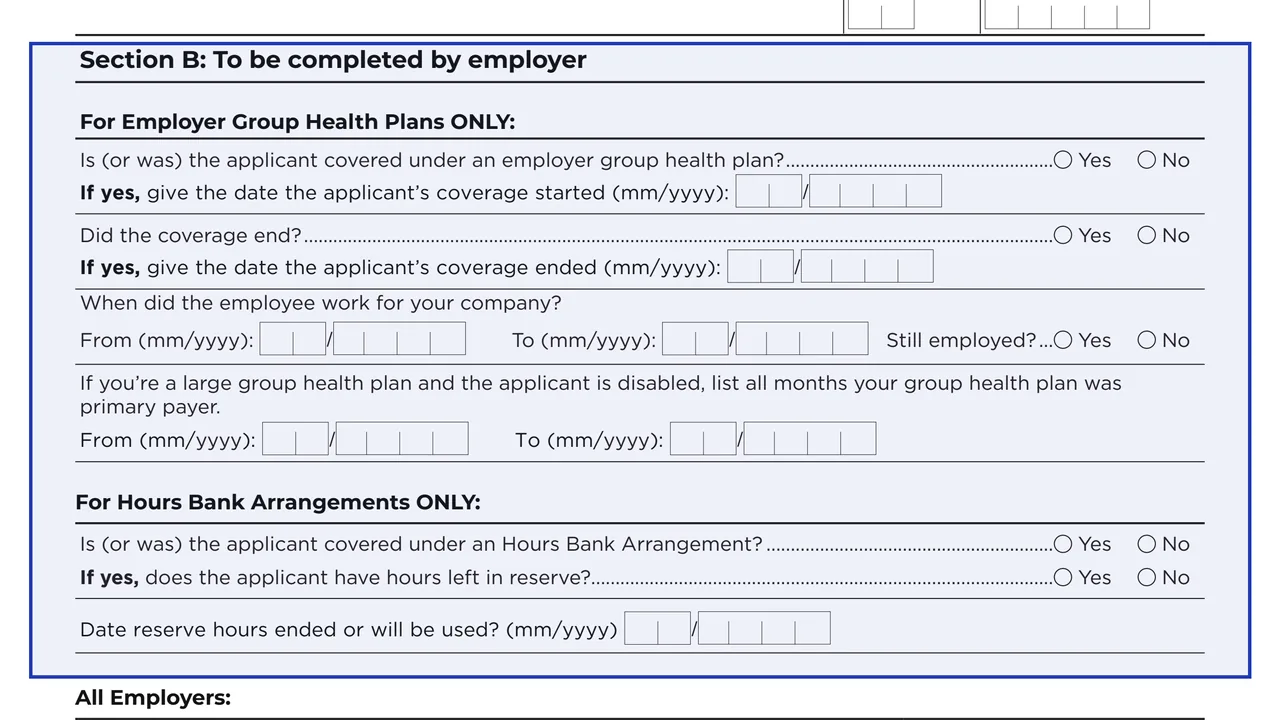
Section B covers employer group health plans, hours bank arrangements and the signature of a company official. You can fill it out free in your browser on this page and download the result without an account.

The applicant's name and Social Security Number, the employee's name and SSN if different, and the employer's name and address.
For employer group health plans only: whether the applicant is (or was) covered and the start date, and whether the coverage ended and the end date (mm/yyyy).
When the employee worked for the company, from and to (mm/yyyy), and whether the employee is still employed.
If the employer is a large group health plan and the applicant is disabled, the months the plan was primary payer, from and to.
For hours bank arrangements only: whether the applicant is (or was) covered, whether hours are left in reserve, and the date reserve hours ended or will be used.
For all employers: the signature, title and phone number of a company official and the date signed.
Enter the applicant's name and SSN, the employee's name and SSN if different, and the employer's name and address.
The form says to ask your employer to fill out Section B with the coverage, employment and, if it applies, hours bank details.
A company official signs and dates Section B and adds their title and phone number.
Fill out Form CMS-40B, the request to enroll in Medicare Part B, including the employment and coverage dates in its item 3.
Mail or fax CMS-L564 together with CMS-40B to your local Social Security office. Find an office at SSA.gov/locator.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
Mail or fax it together with Form CMS-40B to your local Social Security office. Find an office at SSA.gov/locator. The CMS address in the Paperwork Reduction Act notice is for comments on the form only.
The form says enrolling this way requires group health plan coverage through your or your spouse's current employment since the first month you were eligible for Part B, and that the coverage has not ended more than 8 months ago.
For people who qualify for Medicare because of a disability, the form says the coverage is large group health plan coverage based on your, your spouse's or a family member's current employment.
Social Security: 1-800-772-1213, TTY 1-800-325-0778, with Spanish service by pressing 2, or in person at a local office. Free counseling is available from your State Health Insurance Program (SHIP) at shiphelp.org.
Medicare information is available in large print, braille or audio. Visit Medicare.gov/about-us/accessibility-nondiscrimination-notice or call 1-800-MEDICARE (1-800-633-4227), TTY 1-877-486-2048.
The form estimates an average of 15 minutes per response, including reviewing the instructions and gathering the information.

CMS-40B
47 fields, 3 pages
CMS-1763
29 fields, 2 pages

CMS-10106
44 fields, 3 pages

CMS-1490S
49 fields, 18 pages

CMS-20027
20 fields, 1 page
The form has one section for the person signing up for Part B and one for the employer.
No tool matches that search.
Two people. The person signing up for Medicare Part B completes Section A, and the employer completes Section B, which a company official signs.
No. The form says to mail or fax it together with Form CMS-40B to your local Social Security office. Find one at SSA.gov/locator.
The form says the group health plan coverage can be through your or your spouse's current employment. Section A has fields for the employee's name and SSN when they differ from the applicant's.
It says group health plan coverage through your or your spouse's current employment since the first month you were eligible for Part B is needed, and that the coverage has not ended more than 8 months ago.
The form says the coverage is large group health plan coverage based on your, your spouse's or a family member's current employment. A large group health plan lists the months it was primary payer.
It is filled out only for hours bank arrangements. It asks whether the applicant is or was covered, whether hours are left in reserve, and the date reserve hours ended or will be used.
The form lists Social Security at 1-800-772-1213 (TTY 1-800-325-0778), in-person help at a local Social Security office, and free counseling from your local SHIP at shiphelp.org.