Header
Medicare Certification Number, name of facility and survey date.
CMS-643
Hospice Survey AND Deficiencies Report
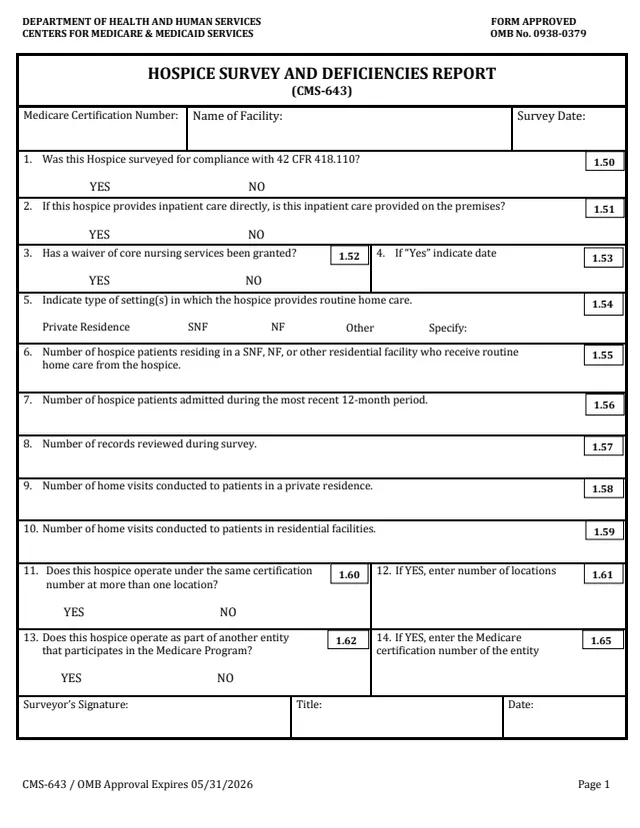
Form CMS-643 is the Hospice Survey and Deficiencies Report from the Centers for Medicare & Medicaid Services (CMS), part of the U.S. Department of Health and Human Services. It records the results of a survey of a hospice and is signed by the surveyor. The CMS forms page lists a revision date of 2008-06-01 and OMB No. 0938-0379.
Page 1 identifies the hospice by Medicare Certification Number, facility name and survey date, then asks 14 questions about inpatient care, any waiver of core nursing services, settings for routine home care, patient and visit counts, extra locations and links to another Medicare entity. Page 2 lists deficiencies by data tag number and Condition of Participation (COP) or standard number. Page 3 holds the surveyor's attestation statement and the Paperwork Reduction Act statement.
The PRA statement calls this a mandatory information collection and estimates an average of twenty-four hours per response. You can fill it out free in your browser on this page and download the result without an account.
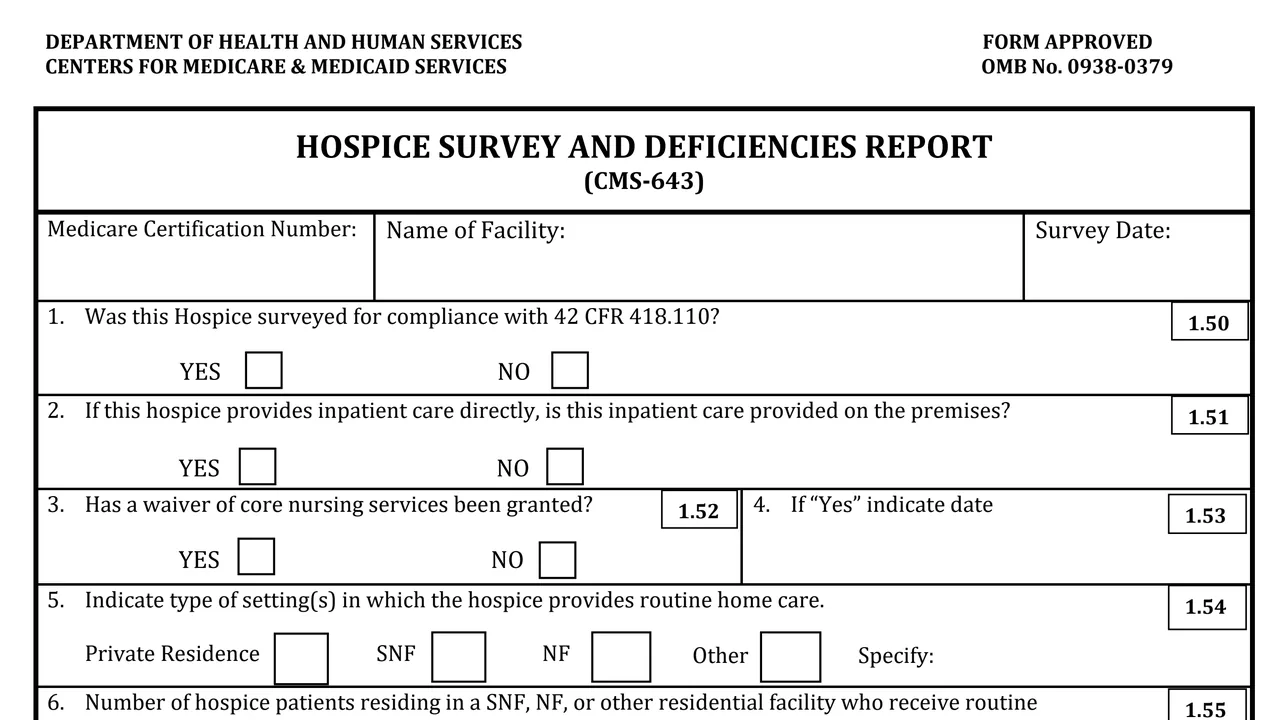
Medicare Certification Number, name of facility and survey date.
Compliance survey under 42 CFR 418.110, inpatient care on the premises, any waiver of core nursing services and its date, and the settings for routine home care: private residence, SNF, NF or other.
Hospice patients in a SNF, NF or other residential facility who receive routine home care, patients admitted in the most recent 12-month period, records reviewed, and home visits to private residences and to residential facilities.
Whether the hospice operates under the same certification number at more than one location and how many, and whether it operates as part of another Medicare entity, with that entity's certification number.
A table with Data Tag Number, COP/Standard No. and Comments columns, with Page __ of __ numbering for more pages.
The surveyor certifies having reviewed each CMS hospice Condition of Participation and related standards, and that except as indicated on the form the facility was found to comply. Signature, title and date follow.
Each item on page 1 also carries a data number from 1.50 to 1.65.
Enter the Medicare Certification Number, the name of the facility and the survey date.
Mark yes or no for each question, add the waiver date if one was granted, and mark each setting for routine home care, specifying any other setting.
Fill in the numbers asked in items 6 to 10, such as patients admitted in the most recent 12-month period and home visits conducted.
Answer items 11 and 13. A yes on item 11 adds the number of locations, and a yes on item 13 adds the Medicare certification number of the other entity.
On page 2, list each deficiency with its data tag number, COP or standard number and comments, and number the pages.
The surveyor signs page 1 and the attestation statement on page 3, with title and date.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form does not print a mailing address. Its CMS disclosure says questions or concerns about where to submit documents go to [email protected].
The form says not to send applications, claims, payments, medical records or documents with sensitive information to the PRA Reports Clearance Office. That CMS address is for comments on the time estimate.
The PRA statement says this is a mandatory information collection.
The form estimates an average of twenty-four hours per response, including reviewing instructions, searching data resources, gathering the data and completing and reviewing it.
The form shows OMB No. 0938-0379. Its page footers say OMB Approval Expires 05/31/2026, its PRA statement gives 09/30/2022, and the CMS page lists 2019-04-30.
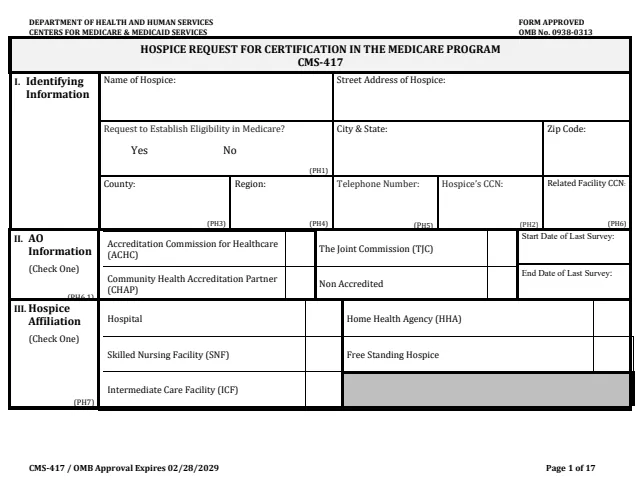
CMS-417
117 fields, 17 pages

CMS-2802B
42 fields, 1 page
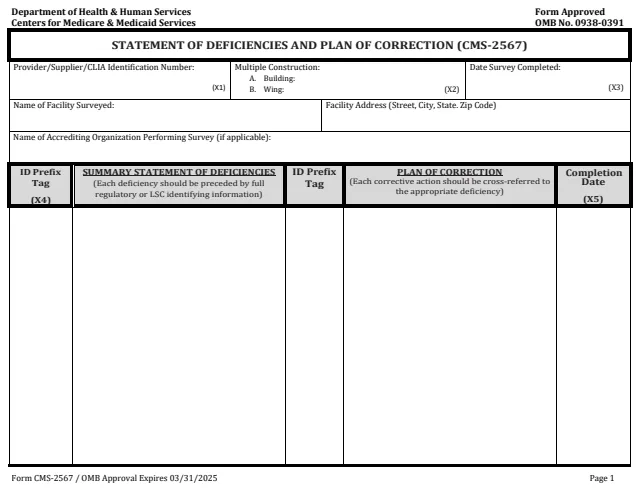
CMS-2567
22 fields, 5 pages
CMS-1539
51 fields, 2 pages

CMS-801
13 fields, 1 page

CMS-807
11 fields, 2 pages
The report is completed and signed by a surveyor about a hospice.
No tool matches that search.
The form is signed by the surveyor, on page 1 and in the attestation statement on page 3, with title and date.
Deficiencies, each with a data tag number, a COP/Standard number and comments. Pages are numbered Page __ of __.
That they reviewed each CMS hospice Condition of Participation and related standards, and that except as indicated on the form the facility was found to comply with the CMS standards and/or the Conditions of Participation.
The PRA statement estimates an average of twenty-four hours per response.
The form's page footers say OMB Approval Expires 05/31/2026, its PRA statement gives 09/30/2022 and the CMS page lists 2019-04-30. All three dates are before October 20, 2026.
The form's CMS disclosure points questions or concerns about where to submit documents to [email protected].