CMS-1539

MEDICARE/MEDICAID CERTIFICATION AND TRANSMITTAL

Agency
CMS
Revision
07/84
Fillable fields
51
Pages
2
Official source
CMS form page
Checked
October 20, 2026
Fill CMS-1539 online
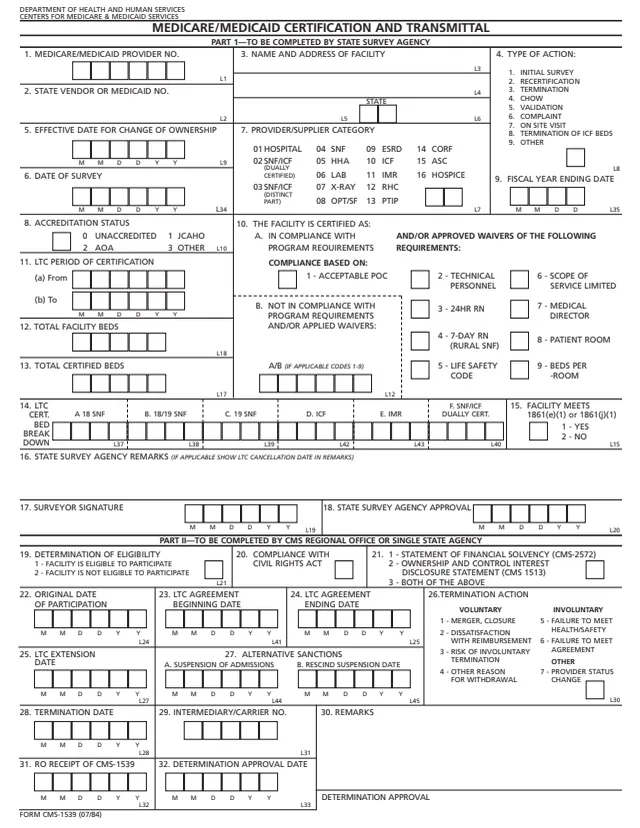
Page 1 of form CMS-1539

Form CMS-1539: Medicare/Medicaid Certification and Transmittal

Form CMS-1539 is the Medicare/Medicaid Certification and Transmittal from the Centers for Medicare & Medicaid Services, part of the U.S. Department of Health and Human Services. It records one facility's survey and certification result. The form says Part I is to be completed by the State survey agency and Part II by the CMS Regional Office or Single State Agency.

Part I covers the facility's provider and vendor numbers, the type of action, survey dates, the provider or supplier category, accreditation, compliance status, bed counts, remarks and the surveyor's signature. Part II covers the eligibility determination, civil rights compliance, ownership and solvency statements, agreement dates, termination action and alternative sanctions.

The form is dated 07/84 and the CMS page lists its OMB number as exempt. You can fill it out free in your browser on this page and download the result without an account.

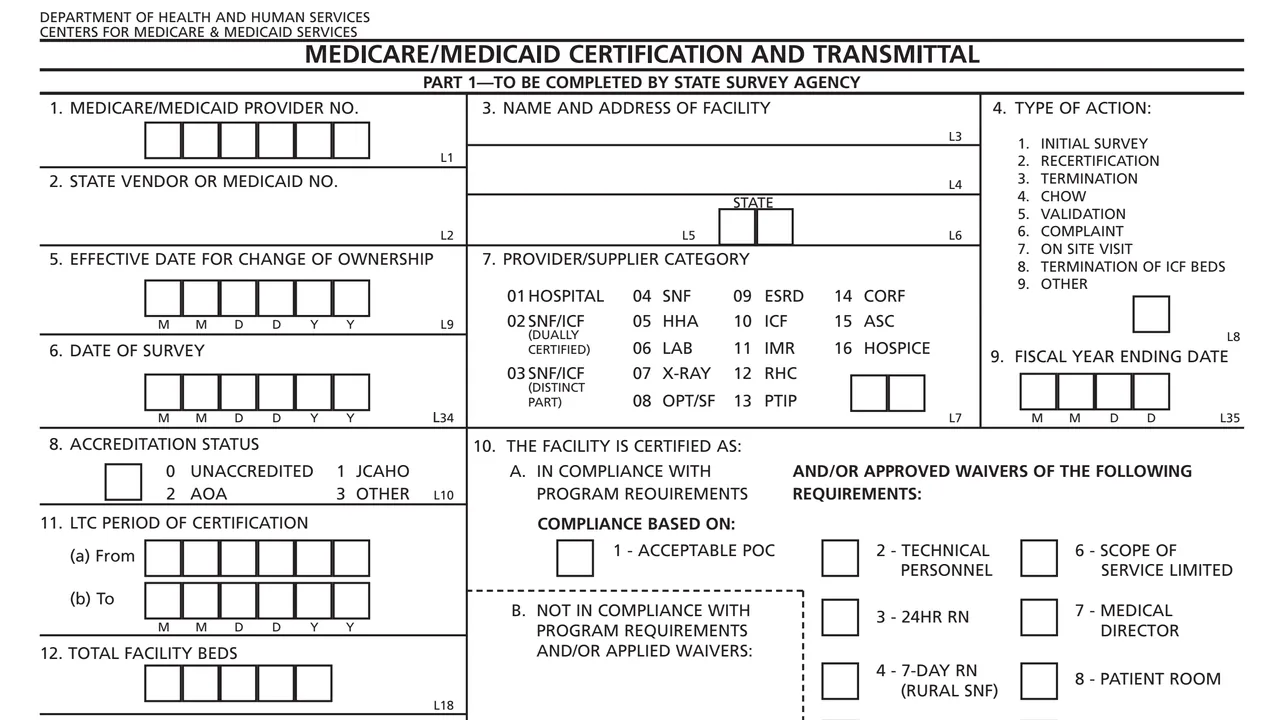
Top of page 1 of Form CMS-1539: Medicare/Medicaid Certification and Transmittal, as printed by CMS

What's on Form CMS-1539

Items 1 to 9: facility and action

Medicare/Medicaid provider number, State vendor or Medicaid number, facility name and address, type of action, change of ownership date, survey date, provider or supplier category, accreditation status and fiscal year ending date.

Items 10 to 15: compliance and beds

Whether the facility is certified as in compliance or not in compliance, with waiver codes, the LTC period of certification, total facility beds, total certified beds, the LTC certified bed breakdown and a yes or no for section 1861(e)(1) or 1861(j)(1).

Items 16 to 18: remarks and signatures

State survey agency remarks, which the form says should show any LTC cancellation date, the surveyor's signature and the State survey agency approval, each with a date.

Items 19 to 21: eligibility and statements

Whether the facility is eligible to participate, compliance with the Civil Rights Act, and whether the statement of financial solvency (CMS-2572), the ownership and control interest disclosure statement (CMS 1513) or both apply.

Items 22 to 27: dates, termination and sanctions

Original date of participation, LTC agreement beginning, ending and extension dates, the termination action code, and alternative sanctions: suspension of admissions and rescind suspension date.

Items 28 to 32: closing entries

Termination date, intermediary or carrier number, remarks, the date the Regional Office received the CMS-1539, and the determination approval date.

Items are numbered 1 to 32 across the two parts.

How Form CMS-1539 is completed

  1. 1

    Identify the facility

    In Part I, enter the provider number, State vendor or Medicaid number and the facility's name and address.

  2. 2

    Record the action and survey

    Pick the type of action, such as initial survey, recertification, complaint or validation, and enter the survey date, provider or supplier category and accreditation status.

  3. 3

    Record compliance and beds

    Mark item 10 and any waiver codes, then enter the LTC certification period, bed totals and the LTC certified bed breakdown where they apply.

  4. 4

    Add remarks and sign Part I

    Enter State survey agency remarks, then the surveyor signature and the State survey agency approval with dates.

  5. 5

    Complete Part II

    The CMS Regional Office or Single State Agency records eligibility, statements, agreement dates, any termination or sanction, and the determination approval date.

Why fill Form CMS-1539 on indox

You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.

  • Fill the form right in your browser, no software to install
  • Free to fill and free to download, with no account
  • The official blank straight from the CMS, not a copy someone retyped
  • Works on a phone, tablet or computer

What the form and the CMS page say

Copies

The second page of the PDF carries five copy labels: CMS Regional Office, Single State Agency, State Survey Agency (twice) and Courtesy Copy.

Where it goes

The form prints no mailing address. Its parts are marked for the State survey agency and for the CMS Regional Office or Single State Agency.

Termination codes

Item 26 lists voluntary reasons (merger or closure, dissatisfaction with reimbursement, risk of involuntary termination, other reason for withdrawal), involuntary reasons (failure to meet health and safety, failure to meet agreement) and provider status change.

OMB status and instructions

The CMS page lists the OMB number as exempt and its special instructions as N/A. The form prints no separate instructions.

Who uses Form CMS-1539?

  • State survey agencies

    Part I is marked to be completed by the State survey agency. Item 18 is the State survey agency's approval with a date.

  • Surveyors

    Item 17 is the surveyor's signature with a date, next to the State survey agency remarks in item 16.

  • CMS Regional Office or Single State Agency

    Part II is marked to be completed by the CMS Regional Office or Single State Agency. It holds the eligibility determination and the determination approval date.

  • The facility on the form

    The form records one facility's name, address, provider number and category. Neither part is marked for the facility to complete.

The form names who completes each part. Both parts are marked for government agencies.

Official sources and the blank

Do it all with indox

View all 94 tools

Questions about Form CMS-1539

Who completes Form CMS-1539?

The form says Part I is to be completed by the State survey agency and Part II by the CMS Regional Office or Single State Agency.

What types of action can Form CMS-1539 record?

Item 4 lists initial survey, recertification, termination, CHOW, validation, complaint, on site visit, termination of ICF beds and other.

Which facility types does item 7 cover?

Item 7 has 16 numbered provider and supplier categories, among them hospital, SNF, HHA, lab, X-ray, ESRD, ICF, RHC, CORF, ASC and hospice.

Which other forms does Form CMS-1539 refer to?

Item 21 refers to the statement of financial solvency (CMS-2572) and the ownership and control interest disclosure statement (CMS 1513), with a code for both.

Where is an LTC cancellation date recorded?

Item 16, State survey agency remarks, says to show the LTC cancellation date in the remarks if applicable.

Does Form CMS-1539 have an OMB number?

The CMS page lists the OMB number as exempt. The form is dated 07/84.