Items 1 to 6: facility and administrator
Name of facility, provider number, street address, telephone, name of administrator and the administrator's qualification: RN, physician, undergrad degree or other.
CMS-1572
HHA SURVEY REPORT
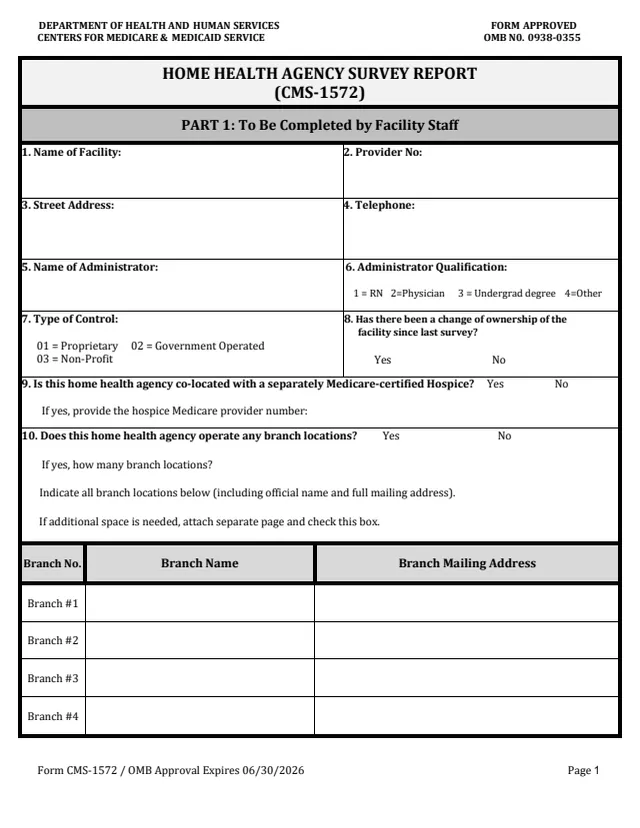
Form CMS-1572 is the Home Health Agency Survey Report from the Centers for Medicare & Medicaid Services (CMS), part of the U.S. Department of Health and Human Services. The CMS forms page lists it as the HHA Survey Report. It has two parts: Part 1 is to be completed by facility staff, and Part 2 is to be completed by the surveyor.
Part 1 asks for the home health agency's name, provider number, address and administrator, its type of control, any change of ownership since the last survey, any co-located hospice, its branch locations, how each type of service is provided and staffing in full-time equivalents. Part 2 records the type of survey and survey data such as the total number of home visits.
The form does not print a mailing address for the completed report. Its disclaimer points questions about where to submit documents to [email protected]. Each page shows OMB No. 0938-0355 with an approval expiration date of 06/30/2026. You can fill it out free in your browser on this page and download the result without an account.
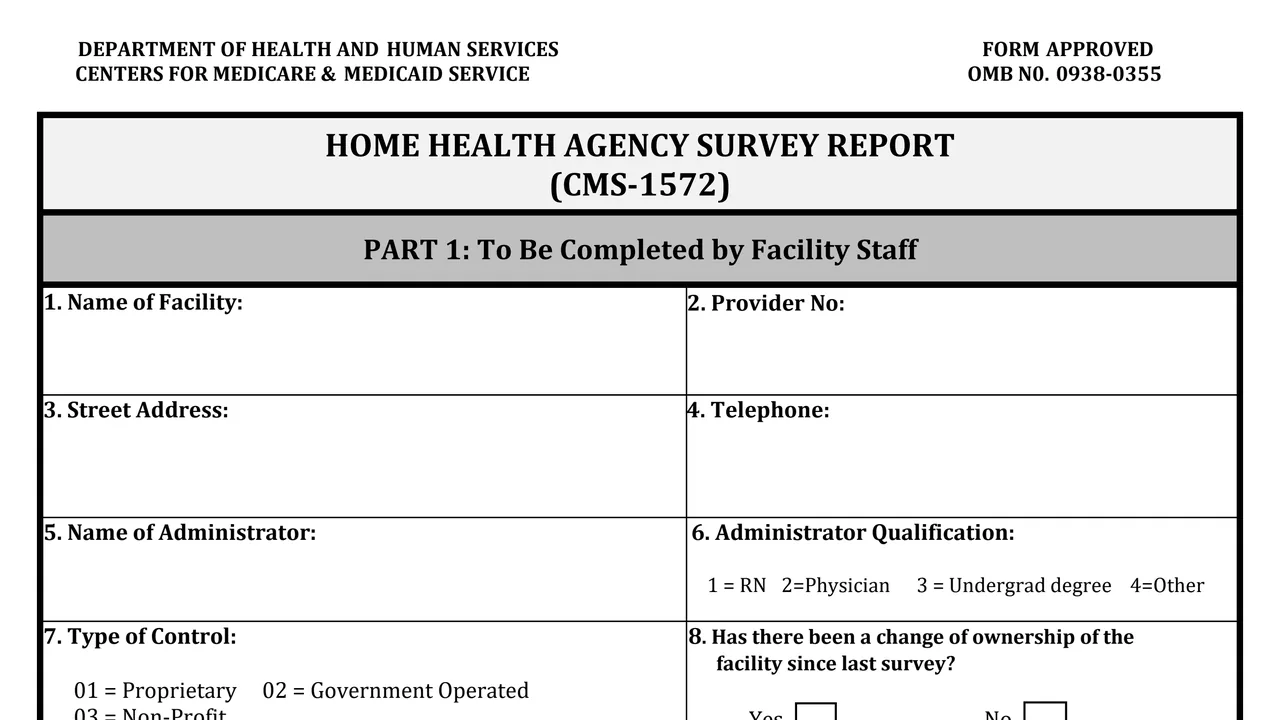
Name of facility, provider number, street address, telephone, name of administrator and the administrator's qualification: RN, physician, undergrad degree or other.
Type of control (proprietary, government operated or non-profit) and whether there has been a change of ownership of the facility since the last survey.
Whether the agency is co-located with a separately Medicare-certified hospice, and a table of branch locations with branch number, branch name and mailing address.
For ten services, from skilled nursing and therapy to home health aide, pharmaceutical, infusion, laboratory and outpatient therapy services, whether each is provided by HHA staff, under arrangement or a combination.
Full-time equivalents, not hours, for direct hire staff and staff under arrangement in ten job types from registered nurses to home health aides, plus the name and title of the person completing the form and the date.
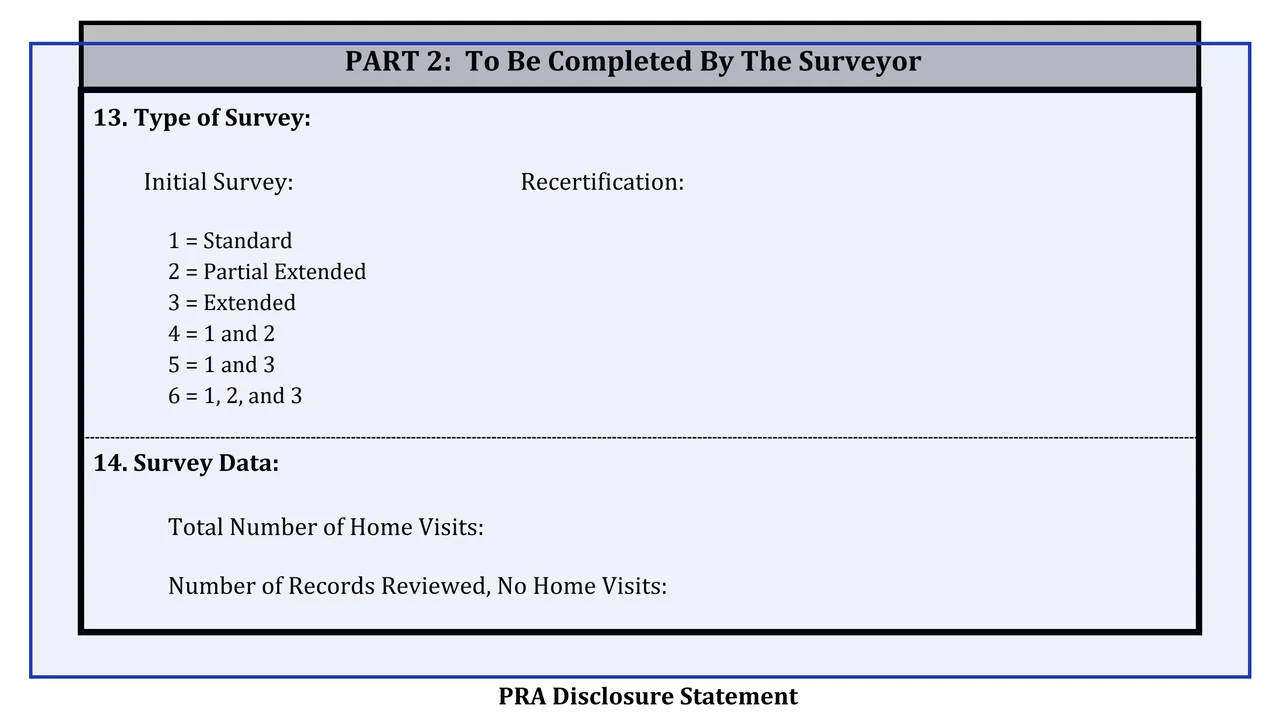
Item 13 records the type of survey, initial or recertification, coded 1 to 6 for standard, partial extended, extended and combinations. Item 14 records the total number of home visits and the number of records reviewed with no home visits.
Facility staff enter the facility name, provider number, street address, telephone, administrator and the administrator qualification code.
Enter the type of control code and answer yes or no on a change of ownership since the last survey and on co-location with a separately Medicare-certified hospice.
If the agency operates branches, give how many and each branch's official name and full mailing address. The form says to attach a separate page and check the box if more space is needed.
For each service in item 11, enter 1 for HHA staff, 2 for under arrangement or 3 for a combination.
List full-time equivalents, not hours, for direct hire staff and staff under arrangement, then add the name and title of the person completing the form and the date.
The surveyor records the type of survey and the survey data in items 13 and 14.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form does not print a mailing address. Its disclaimer says questions or concerns about where to submit documents go to [email protected].
The form says not to send applications, claims, payments, medical records or documents with sensitive information to the PRA Reports Clearance Office. That CMS address is for comments on the time estimate.
The form shows OMB No. 0938-0355 and an OMB approval expiration date of 06/30/2026. The CMS page lists the same expiration date.
The form estimates an average of 30 minutes per response, including reviewing instructions, searching data resources and gathering the data.

CMS-2802C
34 fields, 1 page
CMS-2567
22 fields, 5 pages
CMS-1539
51 fields, 2 pages

CMS-855A
1,236 fields, 72 pages

CMS-807
11 fields, 2 pages
The form splits the work between the home health agency and the surveyor.
No tool matches that search.
The form says Part 1 is to be completed by facility staff and Part 2 by the surveyor.
No. Item 12 asks for full-time equivalents, not hours, for direct hire staff and for staff under arrangement.
The branch table has four rows. The form says to attach a separate page and check the box if additional space is needed.
The form uses 1 for HHA staff, 2 for under arrangement and 3 for a combination.
The form does not print a mailing address. It says questions or concerns about where to submit documents go to [email protected].
Each page shows OMB No. 0938-0355 and an OMB approval expiration date of 06/30/2026.