Item I: Identifying information
Hospice name, street address, city and state, ZIP code, county, region, telephone number, the hospice's CCN, a related facility CCN, and whether this is a request to establish eligibility in Medicare.
CMS-417
HOSPICE REQUEST FOR CERTIFICATION IN MEDICARE
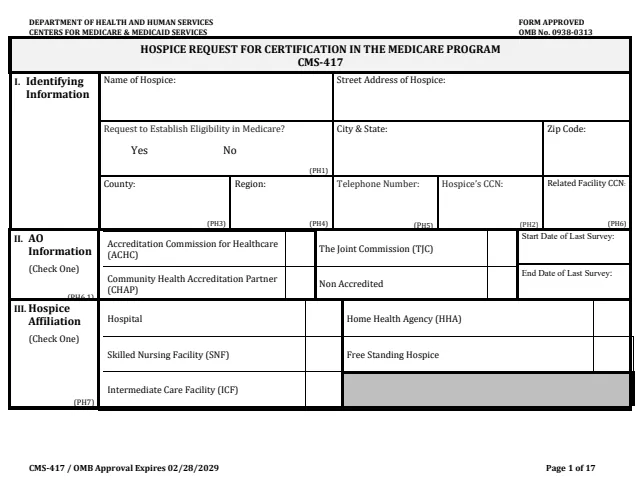
Form CMS-417 is the Hospice Request for Certification in the Medicare Program from the Centers for Medicare & Medicaid Services (CMS). Its instructions say the form serves two purposes: it gives basic information about the hospice that the State needs to schedule a survey, and it provides a database for answering questions from Congress, Federal agencies and the public. The instructions add that submitting it starts the process of obtaining a decision on whether the Conditions are met.
The form has six items: identifying information, accrediting organization (AO) information, hospice affiliation, type of control, how hospice services are provided, and full-time equivalents (FTEs) for employees and volunteers. An attestation statement signed by a hospice representative follows, and the last pages are instructions with worked FTE examples.
The instructions say to complete and return the form to your State Agency and keep a copy for your files. You can fill it out free in your browser on this page and download the result without an account.
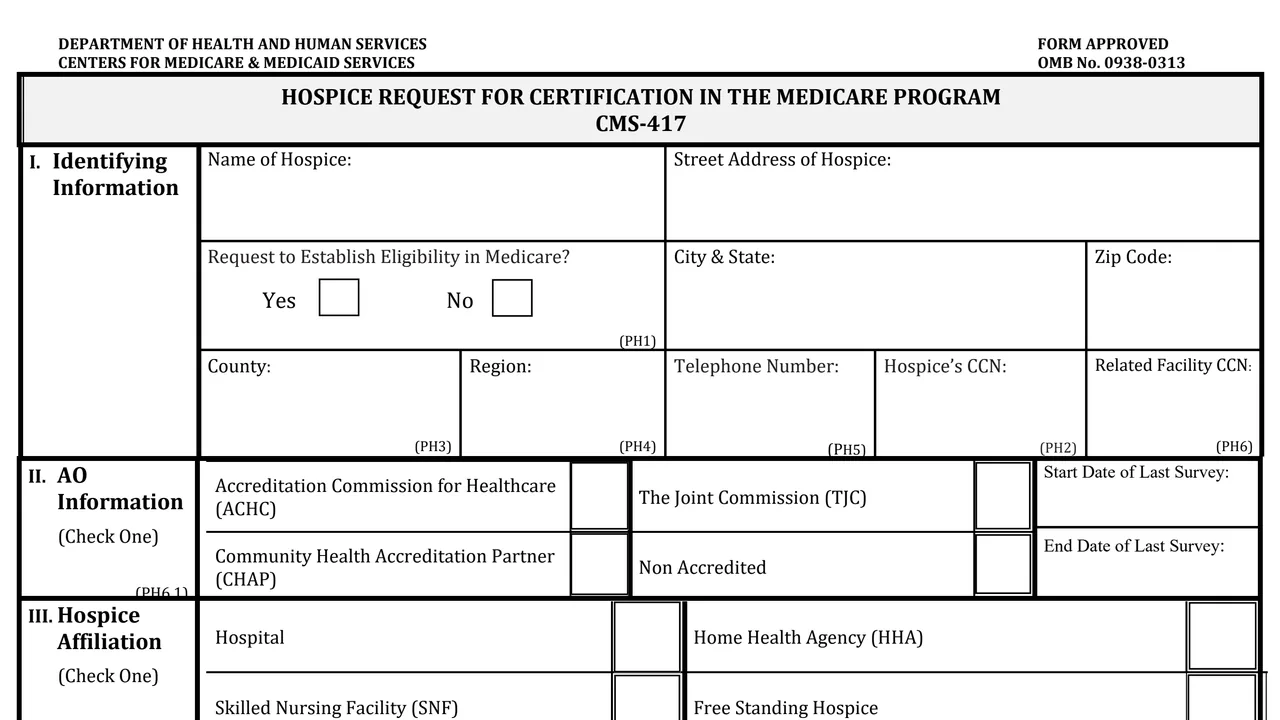
Hospice name, street address, city and state, ZIP code, county, region, telephone number, the hospice's CCN, a related facility CCN, and whether this is a request to establish eligibility in Medicare.
Accreditation Commission for Healthcare (ACHC), The Joint Commission (TJC), Community Health Accreditation Partner (CHAP) or non accredited, with the start and end dates of the last survey.
Hospice affiliation: hospital, HHA, SNF, ICF or free standing hospice. Type of control: one of 13 options under non-profit, for profit/privately owned or government owned/operated.
For core services (physician, nursing, medical social and counseling) and other services such as therapy, hospice aide, homemaker, medical supplies and short term inpatient care: by hospice staff, by contract, by arrangement with another certified hospice, or not applicable.
Employee and volunteer full-time equivalents for physicians, registered nurses, LPNs or LVNs, medical social workers, homemakers, hospice aides, counselors and others, entered with 3 decimal points. The form totals them.
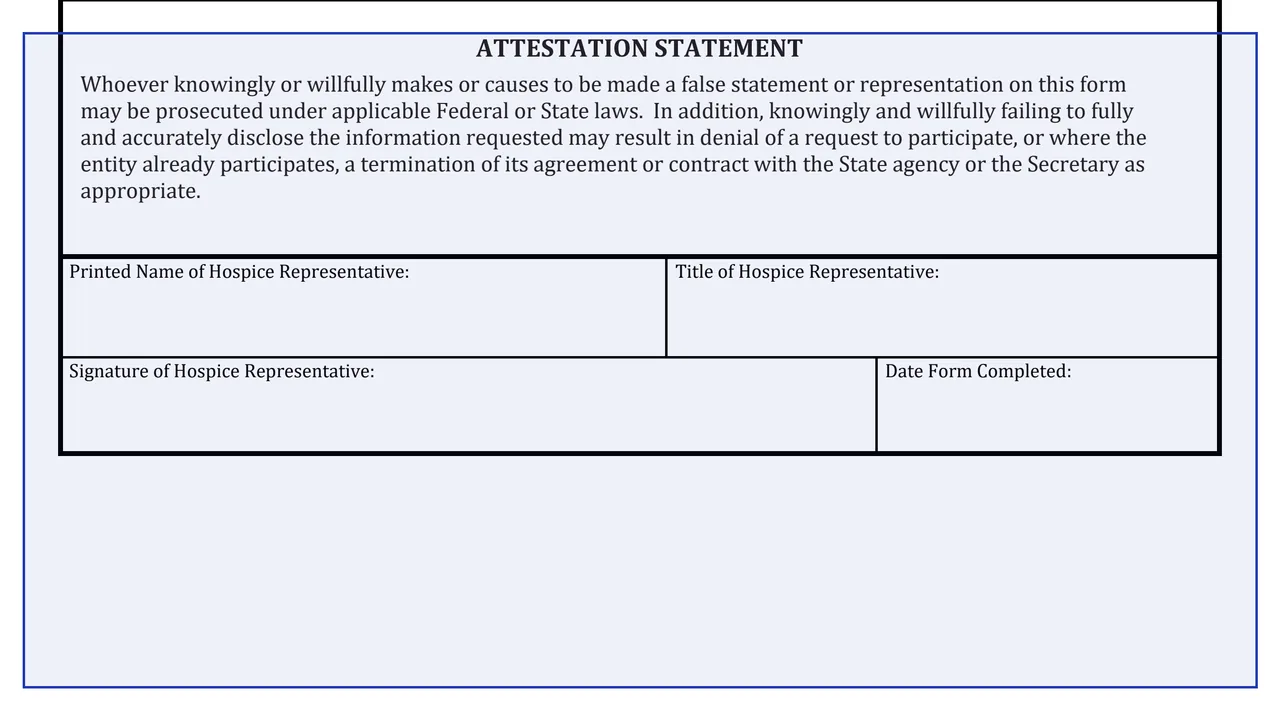
A warning that knowingly false statements may be prosecuted and that failing to disclose may lead to denial or termination, with the hospice representative's printed name, title, signature and date.
The instructions say to answer all questions as of the current date.
Identify the hospice, select Yes for initial certification or No for re-certification, leave Region blank, then check one AO option, one affiliation and one type of control.
In Item V, the instructions say to select all responses that apply for each service and to give the name, address and CCN or supplier number of any other certified hospice or outside contractor.
In Item VI, the instructions divide total yearly hours in each job category by 2,080. Their example: 4,500 hours divided by 2,080 hours equals 2.163 FTEs.
A hospice representative prints their name and title, signs and enters the date the form was completed.
The instructions say to return the completed form to your State Agency, found through the CMS state agency contacts list, and keep a copy for your files.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
To your State Agency. The instructions point to the CMS state agency contacts list at cms.gov for the address. The CMS address in the PRA statement is for comments on the time estimate.
The form says not to send applications or documents with sensitive information to the PRA Reports Clearance Office, and that questions about where to submit documents go to [email protected].
The form says FTE numbers have 3 decimal points, for example 3.000, 2.750 or 7.500. The instructions count a full-time employee as 2,080 hours a year (40 hours x 52 weeks).
The form says knowingly or willfully false statements may be prosecuted under Federal or State laws, and that failing to fully disclose may result in denial of a request to participate or termination of an existing agreement.
The PRA statement calls it a mandatory information collection under OMB No. 0938-0313. Each page shows an OMB approval expiration date of 02/28/2029.
The form estimates an average of 45 minutes per response, including reviewing instructions, searching data resources and gathering the data.
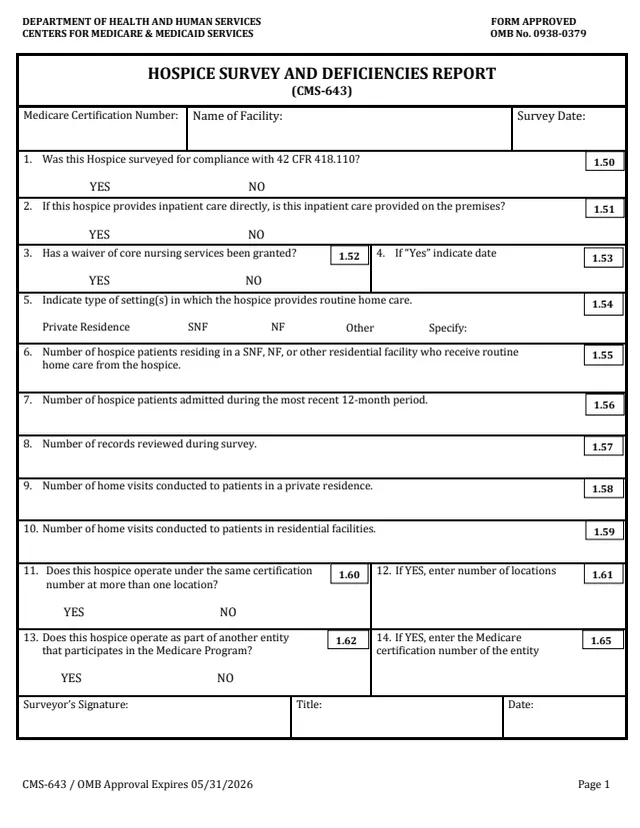
CMS-643
38 fields, 3 pages

CMS-2802B
42 fields, 1 page

CMS-855A
1,236 fields, 72 pages
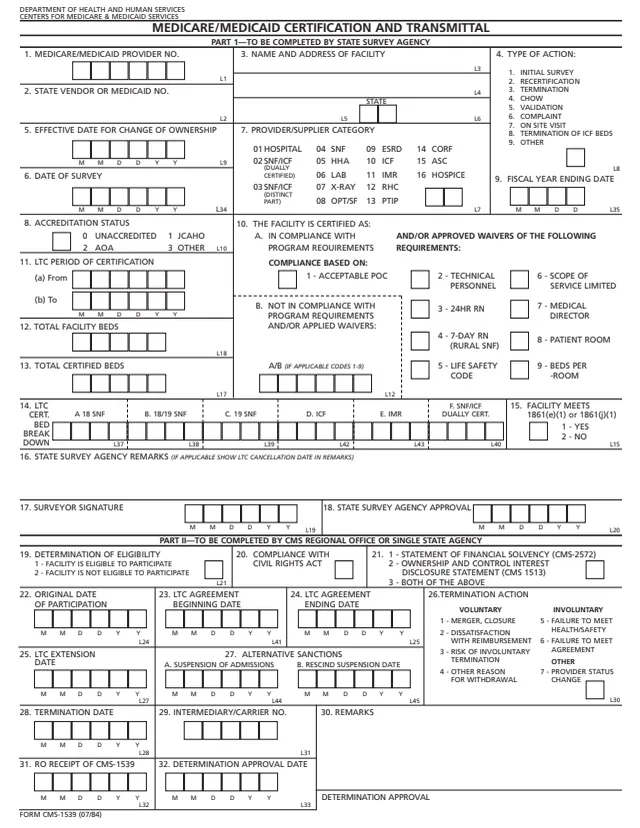
CMS-1539
51 fields, 2 pages
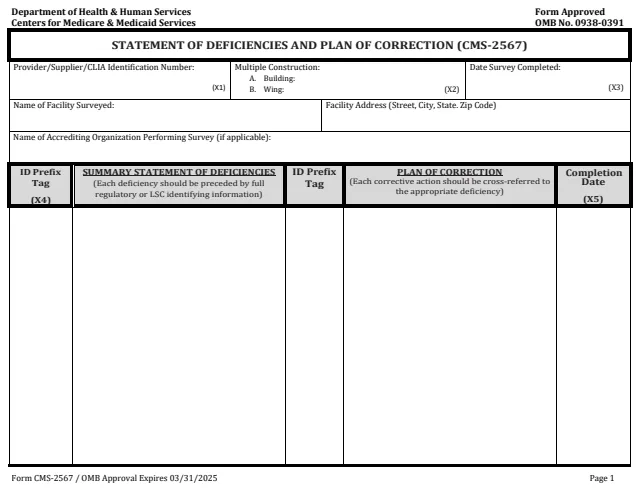
CMS-2567
22 fields, 5 pages
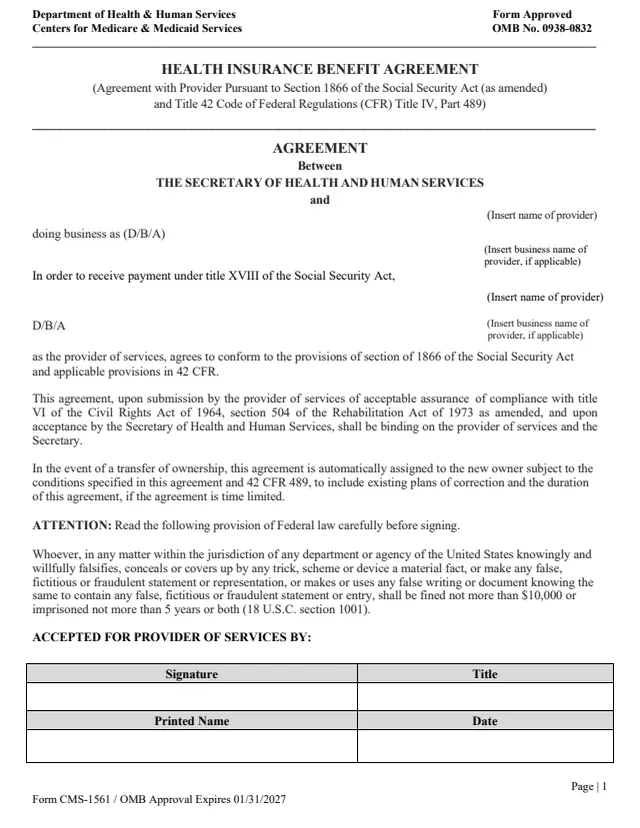
CMS-1561
14 fields, 2 pages
The form is completed by a hospice and returned to the State Agency.
No tool matches that search.
The instructions say it gives the State the basic information about the hospice needed to schedule a survey, and provides a database for questions from Congress, Federal agencies and the public. Submitting it starts the process of a decision on whether the Conditions are met.
No. The instructions say to select Yes when the hospice is requesting initial certification, and No when it already participates in Medicare and is seeking re-certification.
The instructions divide the total hours worked per year in a job category by 2,080. Part-year staff count their weekly hours times the weeks worked, for example 20 hours x 26 weeks = 520 hours.
The form marks physician, nursing, medical social and counseling services with (PH9) as core hospice services. Services marked (PH10) are non-core.
The instructions say to return it to your State Agency, listed in the CMS state agency contacts file, and keep a copy. Questions about where to submit go to [email protected].
The instructions say to leave it blank. The CMS Location, formerly named the CMS Regional Office, completes it.