I. Identifying information
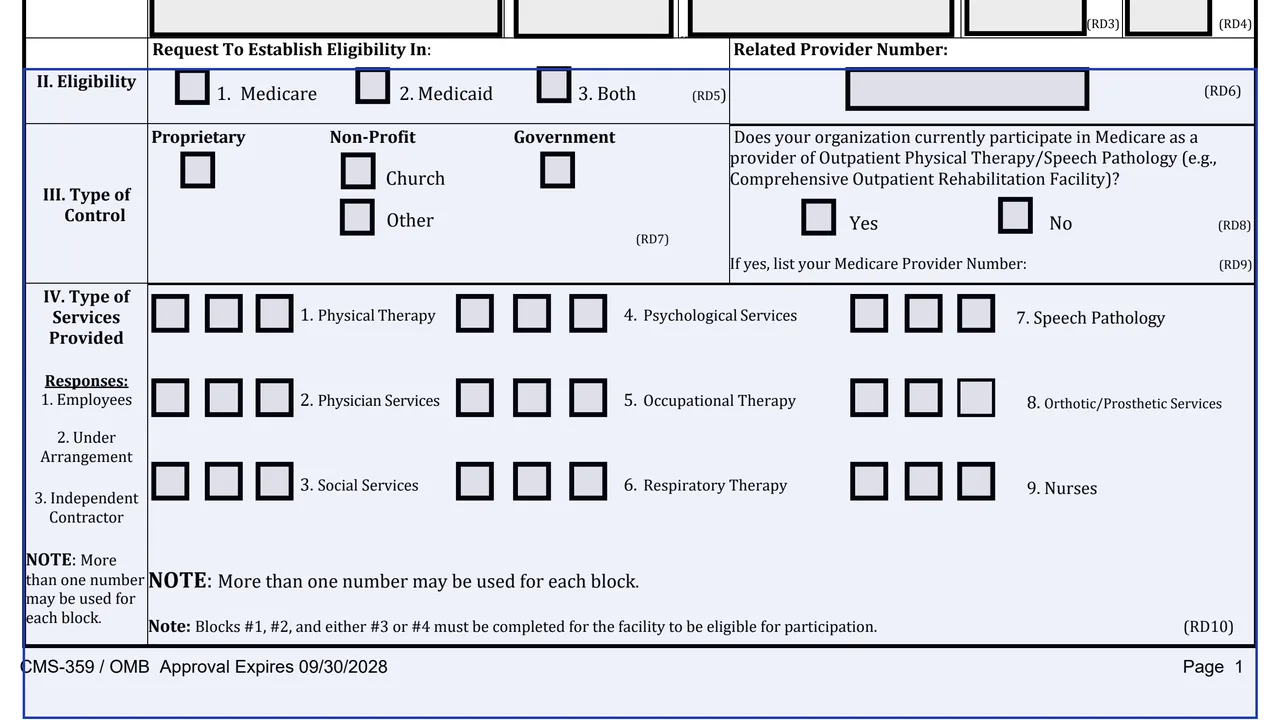
The full name under which the CORF operates, street address, city, county, state, ZIP code, telephone and Medicare/Medicaid provider number, with State/County and State/Region code boxes left blank.
CMS-359
CORF REPORT FOR CERTIFICATION TO PARTICIPATE IN MEDICARE
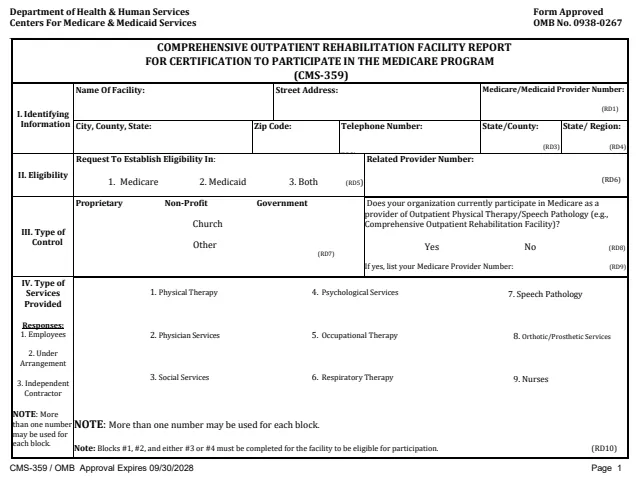
Form CMS-359 is the Comprehensive Outpatient Rehabilitation Facility Report for Certification to Participate in the Medicare Program, from the Centers for Medicare & Medicaid Services. It is completed by a comprehensive outpatient rehabilitation facility (CORF). The instructions say filing this request for certification starts the process of deciding whether the Conditions of Participation are (continue to be) met, and that all questions are answered as of the current date.
The report has four questions: identifying information, eligibility, type of control and the services the facility provides, followed by a signature page for an authorized official. For each service, the facility shows whether it is provided by employees, under arrangement or by an independent contractor.
The instructions say to return the form to the State Survey agency in the envelope provided and keep a copy. The form carries OMB number 0938-0267 with an approval expiration of 09/30/2028. You can fill it out free in your browser on this page and download the result without an account.
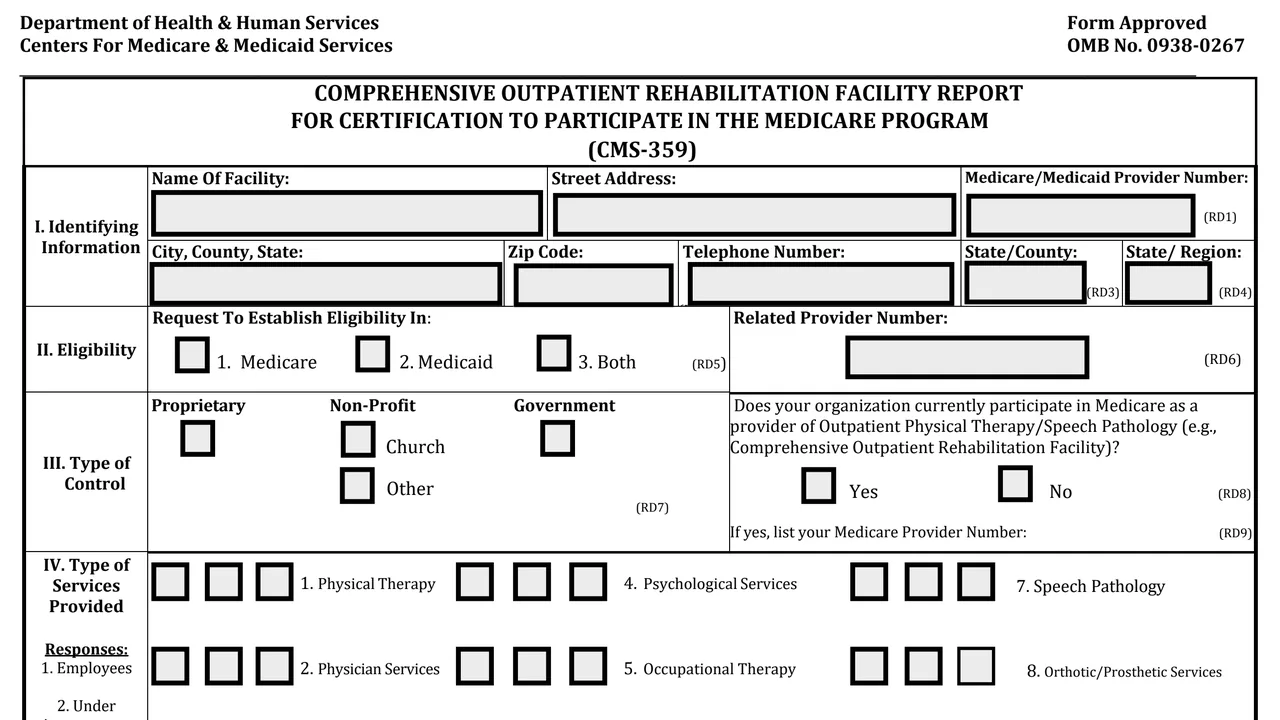
The full name under which the CORF operates, street address, city, county, state, ZIP code, telephone and Medicare/Medicaid provider number, with State/County and State/Region code boxes left blank.
Request to establish eligibility in 1. Medicare, 2. Medicaid or 3. Both, and a related provider number that the State Survey agency completes.
Proprietary, Non-Profit (Church or Other) or Government, and whether the organization currently participates in Medicare as a provider of Outpatient Physical Therapy/Speech Pathology, with its provider number if yes.
Nine blocks: Physical Therapy, Physician Services, Social Services, Psychological Services, Occupational Therapy, Respiratory Therapy, Speech Pathology, Orthotic/Prosthetic Services and Nurses.
A statement on false statements and failure to disclose, then the signature and title of the authorized official and the date signed.
Guidance for each question, definitions of the control types and of Employee, Under Arrangement and Independent Contractor, and the PRA disclosure statement.
Two pages of form are followed by three pages of instructions and the PRA statement.
Enter the facility's full operating name, address and phone. Leave the provider number blank on an initial certification, or enter it on a recertification.
The instructions say all applicants check block #1, because CORF services are covered only under the Medicare program, and that blocks #2 and #3 are for future use only.
Check only one category, the one most descriptive of the organization operating the facility, using the definitions in the instructions.
In each service block, enter 1 for Employees, 2 for Under Arrangement or 3 for Independent Contractor. More than one number may be used for each block.
The authorized official signs page 2 and enters their title and the date signed.
The instructions say to return the form in the envelope provided and keep a copy. Without an envelope, the agency's name and address can be obtained from the nearest Social Security District Office.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
To the State Survey agency in the envelope provided, keeping a copy. The CMS address in the PRA statement is for comments on the time estimate, not for the report.
The form says Blocks #1, #2 and either #3 or #4 must be completed for the facility to be eligible for participation, since these are mandatory services.
The form says knowingly and willfully making a false statement may be prosecuted, and failing to fully and accurately disclose the information may result in denial of participation or termination of an existing agreement.
The PRA statement estimates an average of 30 minutes per response.
The form lists Joy Webb at 410-786-1667 for questions or concerns about where to submit documents.
CMS-1539
51 fields, 2 pages

CMS-855A
1,236 fields, 72 pages
CMS-1561
14 fields, 2 pages
CMS-2567
22 fields, 5 pages
CMS-377
32 fields, 3 pages
CMS-417
117 fields, 17 pages
The form is for facilities, not for individual patients.
No tool matches that search.
CORF stands for comprehensive outpatient rehabilitation facility, as the form's full title shows. Form CMS-359 is the report such a facility files for certification to participate in Medicare.
The instructions say to return it to the State Survey agency in the envelope provided and keep a copy. If no envelope is provided, the agency's name and address can be obtained from the nearest Social Security District Office.
The instructions say all applicants check block #1, because CORF services are covered only under the Medicare program. Blocks #2 and #3 are for future use only.
The form says Blocks #1, #2 and either #3 or #4 must be completed for the facility to be eligible: Physical Therapy, Physician Services, and either Social Services or Psychological Services.
The instructions define an employee as salaried with benefits, under arrangement as the facility paying an organization for its personnel, and an independent contractor as paid for services or time without benefits through the facility.
No. The instructions say to leave it blank on all initial certifications and to insert the six digit provider number on re-certifications.