Items 1 and 2: State agency and hospital
Name and address of the State agency, and name and address of the hospital with its CMS certification number.
CMS-2802
REQUEST FOR VALIDATION OF ACCREDITATION

Form CMS-2802 is listed on the CMS forms page as the Request for Validation of Accreditation. The form itself is titled Authorization for State Agency Hospital Validation Survey, from the Centers for Medicare & Medicaid Services (CMS). It is a one-page form, signed by a CMS regional representative, that names a State agency and a hospital and asks for a validation survey of that hospital.
The form records which accrediting organization currently deems the hospital (TJC, DNV, AOA/HFAP or none), and whether the survey is based on a sample selection or on allegations of significant deficiencies which could affect the health and safety of patients. It then lists the hospital conditions to be surveyed, numbered 482.11 through 482.57, plus the 482.41(b) Life Safety Code standard.
The footer says the original goes to the State survey agency, with copies to CMCS/SCG/DACS. The CMS page lists the OMB number as exempt. You can fill it out free in your browser on this page and download the result without an account.
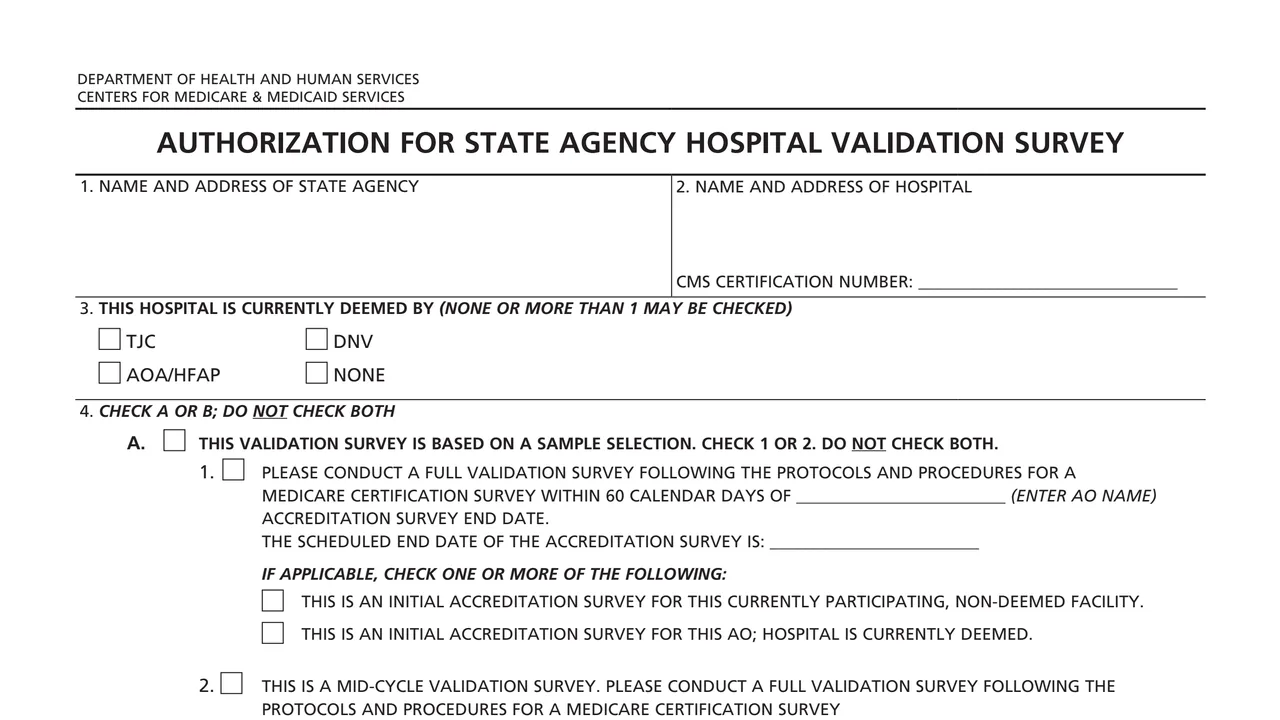
Name and address of the State agency, and name and address of the hospital with its CMS certification number.
Boxes for TJC, DNV, AOA/HFAP and NONE. None or more than one may be checked.
Box 1 asks for a full validation survey within 60 calendar days of the named AO's accreditation survey end date, with the scheduled end date and two initial accreditation survey boxes. Box 2 is a mid-cycle validation survey.
For allegations of significant deficiencies, a choice between a potential IJ, with the survey initiated within 2 working days, or a survey initiated within 45 calendar days.
Checkboxes for conditions from 482.11 federal, State and local laws to 482.57 respiratory care services, including governing body, nursing, infection control and discharge planning, plus 482.41(b) Life Safety Code.
Signature of the regional representative, the region and the date.
Enter the State agency's name and address, the hospital's name and address, and its CMS certification number.
Check TJC, DNV, AOA/HFAP or NONE in item 3. The form allows none or more than one.
The form says to check A or B, not both. Under A, check 1 or 2, not both, and for box 1 enter the AO name and the scheduled end date of the accreditation survey.
Under B, check one: potential IJ, initiate survey within 2 working days, or initiate survey within 45 calendar days.
The form says to check all areas for sample validation surveys, and for allegation surveys all applicable conditions and, if applicable, the Life Safety Code standard.
The regional representative signs and adds the region and date. The footer routes the original to the State survey agency and copies to CMCS/SCG/DACS.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The footer says original to the State survey agency, copies to CMCS/SCG/DACS. No mailing address is printed.
Under item 4A box 1, the form has boxes for an initial accreditation survey of a currently participating, non-deemed facility, and for an initial accreditation survey for this AO when the hospital is currently deemed.
Under item 4A, the form says the SA must complete all validation packet documents listed in Exhibit 63 for any full validation survey.
Under item 4B, the form says the SA must not notify the facility or AO in advance of the survey.
The CMS page lists the OMB number as EXEMPT. No OMB number or expiration date is printed on the form.

CMS-2802B
42 fields, 1 page

CMS-2802C
34 fields, 1 page

CMS-2802D
35 fields, 1 page

CMS-2802E
35 fields, 1 page

CMS-2802F
42 fields, 1 page

CMS-2786T
187 fields, 7 pages
The form is addressed to a State agency about one hospital and signed by a CMS regional representative.
No tool matches that search.
The form is titled Authorization for State Agency Hospital Validation Survey, and the CMS page lists it as the Request for Validation of Accreditation. It names a State agency and a hospital and asks for a validation survey of that hospital.
Item 4A is a survey based on a sample selection, either a full validation survey or a mid-cycle validation survey. Item 4B is a survey based on allegations of significant deficiencies which could affect the health and safety of patients.
No. The form says to check A or B and not both, and under A to check 1 or 2 and not both.
For a sample survey under 4A box 1, within 60 calendar days of the AO accreditation survey end date. For an allegation survey under 4B, within 2 working days for a potential IJ, or within 45 calendar days.
Under item 4B, the form says the SA must not notify the facility or AO in advance of the survey.
TJC, DNV and AOA/HFAP, plus a NONE box. The form says none or more than one may be checked.
Item 6 is the signature of the regional representative, with the region and date in items 7 and 8.