Section I, lines 1 to 8
Name of patient, Medicare Number, phone number, street address, city, state, ZIP code and the item or service.
CMS-20031
TRANSFER (ASSIGNMENT) OF APPEAL RIGHTS
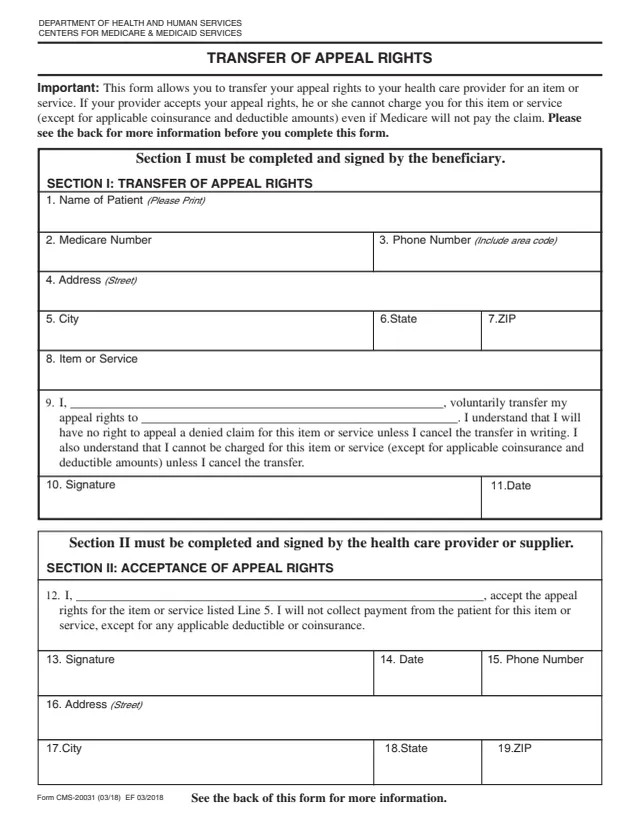
Form CMS-20031 is the Transfer of Appeal Rights form from the Centers for Medicare & Medicaid Services, listed on the CMS page as Transfer (Assignment) of Appeal Rights. The form says it allows a person with Medicare to transfer their appeal rights to their health care provider for an item or service. The CMS page marks the OMB number as exempt and points to the CMS Manual, IOM Pub 100-04, Chapter 29, section 270.2.3.
The form has two sections. Section I is completed and signed by the beneficiary, and Section II is completed and signed by the health care provider or supplier who accepts the appeal rights. The back of the form answers nine common questions, including the financial risks, how long the transfer lasts and how to cancel it.
The form says that if the provider accepts the appeal rights, they cannot charge the beneficiary for the item or service, except for applicable coinsurance and deductible amounts. You can fill it out free in your browser on this page and download the result without an account.
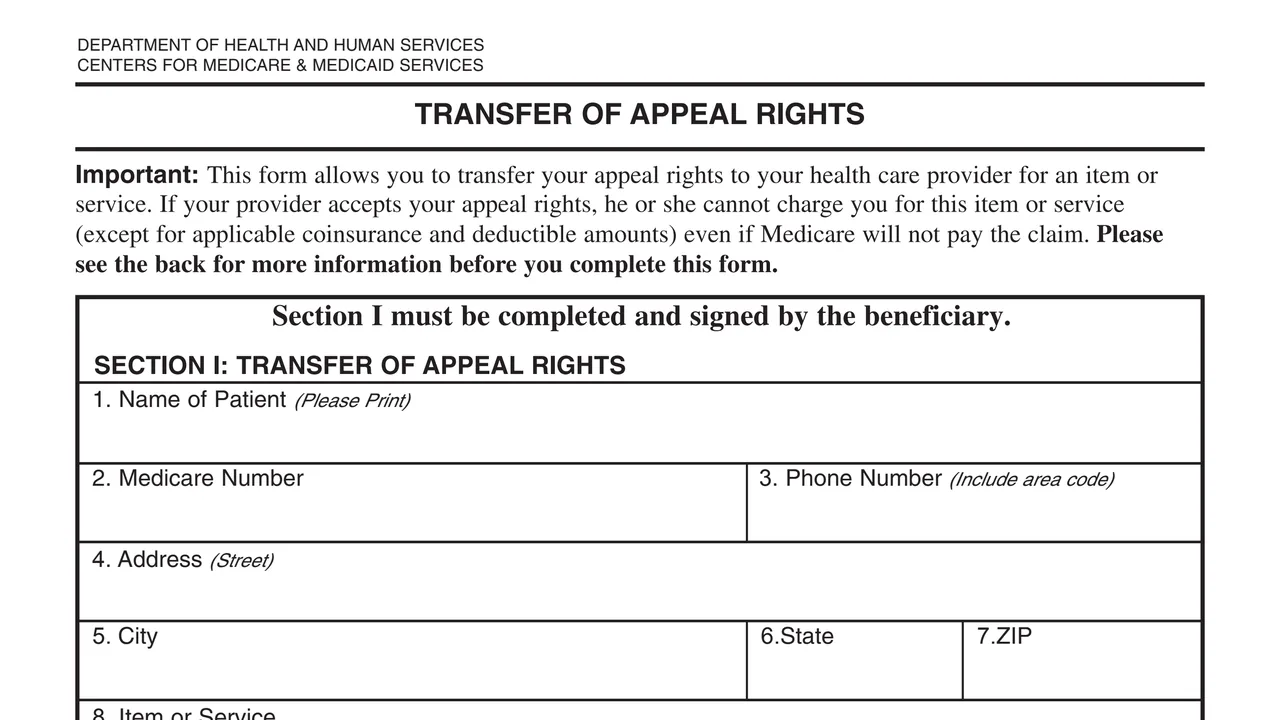
Name of patient, Medicare Number, phone number, street address, city, state, ZIP code and the item or service.
A statement that the beneficiary voluntarily transfers their appeal rights to a named provider, with no right to appeal a denied claim for that item or service unless they cancel the transfer in writing.
The beneficiary's signature and the date.
The provider or supplier accepts the appeal rights and states they will not collect payment from the patient for the item or service, except any applicable deductible or coinsurance.
The provider's signature, date, phone number, street address, city, state and ZIP code.
Page 2 answers nine questions, from why the form was given to who can help complete it.
The form is two pages: the form itself and a page of questions and answers.
The form says to see the back for more information before completing it.
Enter the patient's name, Medicare Number, phone number and address on lines 1 to 7.
Write the item or service on line 8. The transfer covers only that item or service.
Write the beneficiary's name and the provider's name in the line 9 statement, then sign and date on lines 10 and 11.
The provider or supplier writes their name in the acceptance statement, signs, dates and adds their phone number and address.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
If a provider or supplier accepts the appeal rights, the form says they cannot bill for the item or service unless the transfer is canceled or an Advance Beneficiary Notice was already signed. Deductible or coinsurance amounts still apply.
The form says the transfer is permanent unless the beneficiary cancels it. After canceling, the beneficiary may be responsible for payment if Medicare will not pay.
The form says the transfer can be canceled at any time by saying in writing that the beneficiary no longer wishes to transfer the appeal rights. For information it lists 1-800-MEDICARE (1-800-633-4227).
The form points to State Health Insurance Assistance Programs (SHIPs), which it says have volunteer counselors in every State, and to www.medicare.gov.
The form says Medicare information is available in large print, Braille or audio, and lists 1-800-MEDICARE (1-800-633-4227) for more information.
The form has one section for the person with Medicare and one for the provider or supplier.
No tool matches that search.
The form says that if Medicare decides not to pay for the item or service, the provider or supplier will be allowed to appeal the decision instead of the beneficiary.
The form says the beneficiary will have no right to appeal a denied claim for the item or service unless they cancel the transfer in writing.
No. The form says it covers only the item or service listed in Section I.
The form says a provider who accepts the appeal rights cannot bill for the item or service unless the transfer is canceled or an Advance Beneficiary Notice was already signed. Deductible or coinsurance amounts still apply.
The form says by stating in writing that the beneficiary no longer wishes to transfer the appeal rights for the item or service, at any time. It lists 1-800-MEDICARE (1-800-633-4227) for information.
The beneficiary signs Section I and the health care provider or supplier who accepts the appeal rights signs Section II.



