Section 1: Person appointing
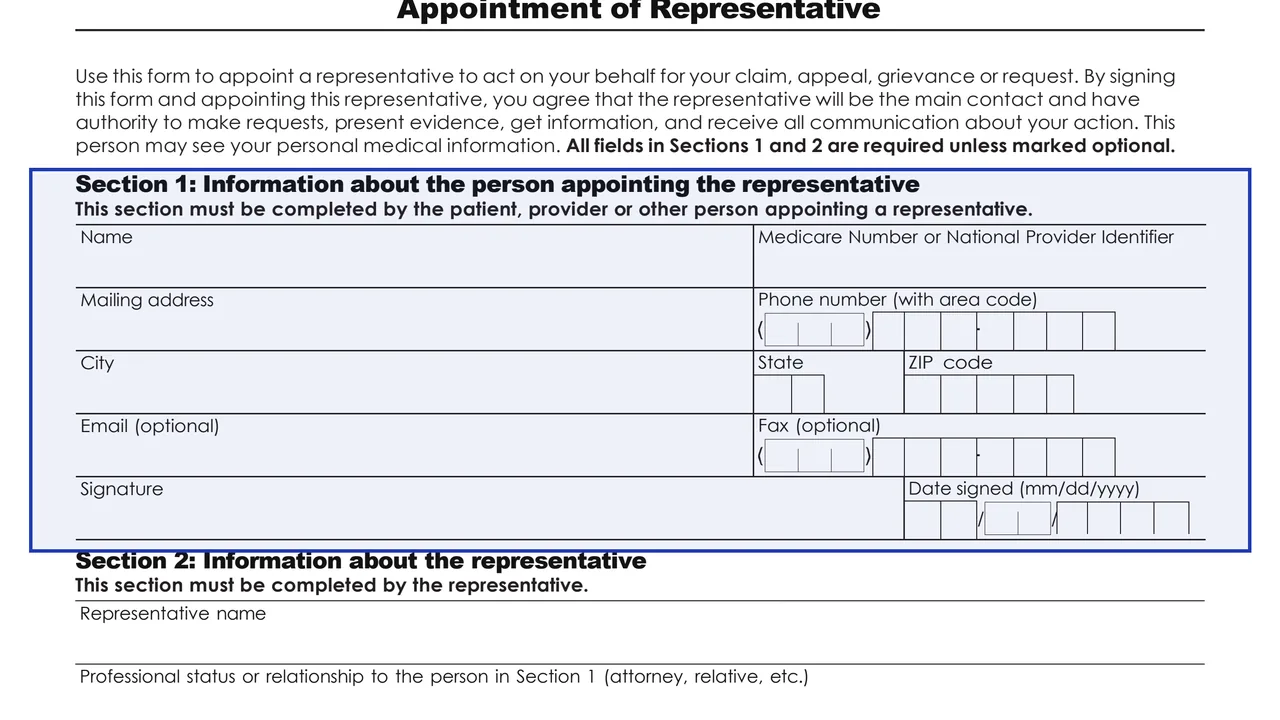
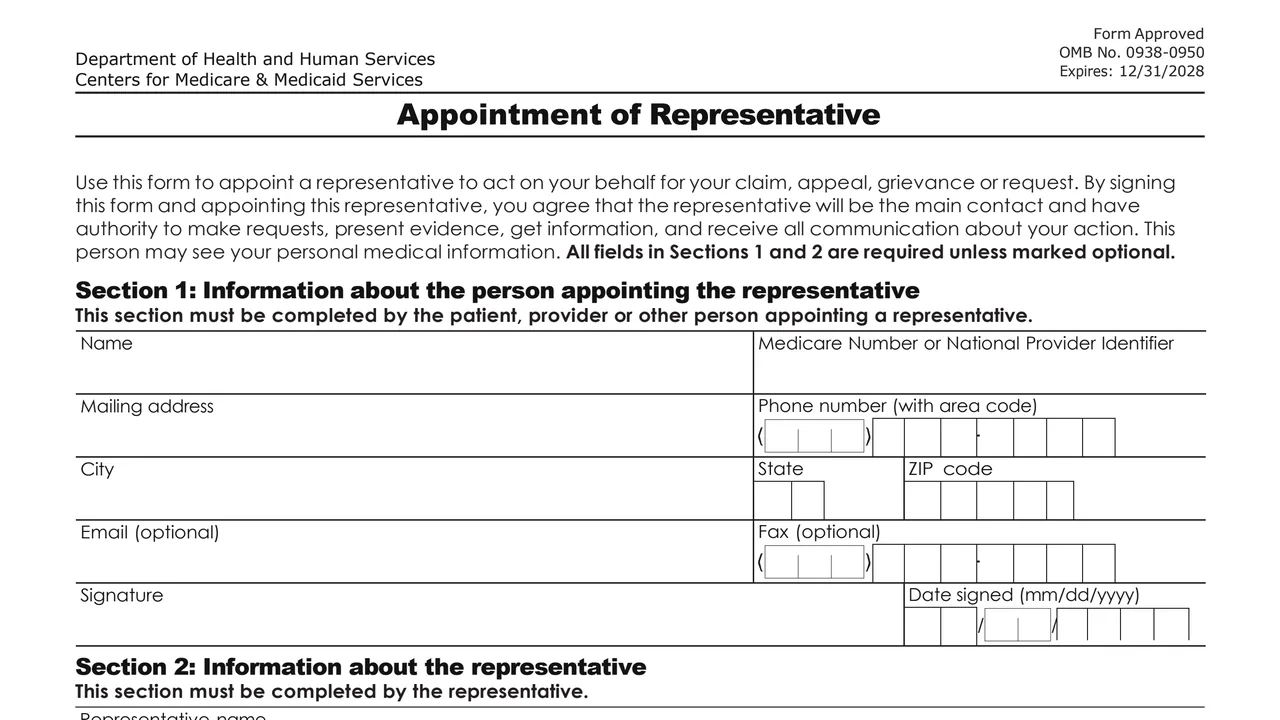
Name, Medicare Number or National Provider Identifier, mailing address, phone number, optional email and fax, signature and date signed.
CMS-1696
APPOINTMENT OF REPRESENTATIVE

Form CMS-1696 is the Appointment of Representative form from the Centers for Medicare & Medicaid Services. The form says it is used to appoint a representative to act on your behalf for a claim, appeal, grievance or request. By signing, the person appointing agrees that the representative will be the main contact, with authority to make requests, present evidence, get information and receive all communication about the action. The form notes the representative may see personal medical information.
Section 1 is completed by the patient, provider or other person appointing a representative, and Section 2 by the representative. Sections 3 and 4 are waivers the representative completes if they apply: a waiver of fee for representation and, for providers and suppliers, a waiver of payment for the items or services at issue. Page 2 covers how long the appointment lasts, where to send the form and the rules on charging fees.
The CMS page says the form was revised with minor non-substantive changes and approved by the Office of Management and Budget on 10/1/2026. You can fill it out free in your browser on this page and download the result without an account.
Name, Medicare Number or National Provider Identifier, mailing address, phone number, optional email and fax, signature and date signed.
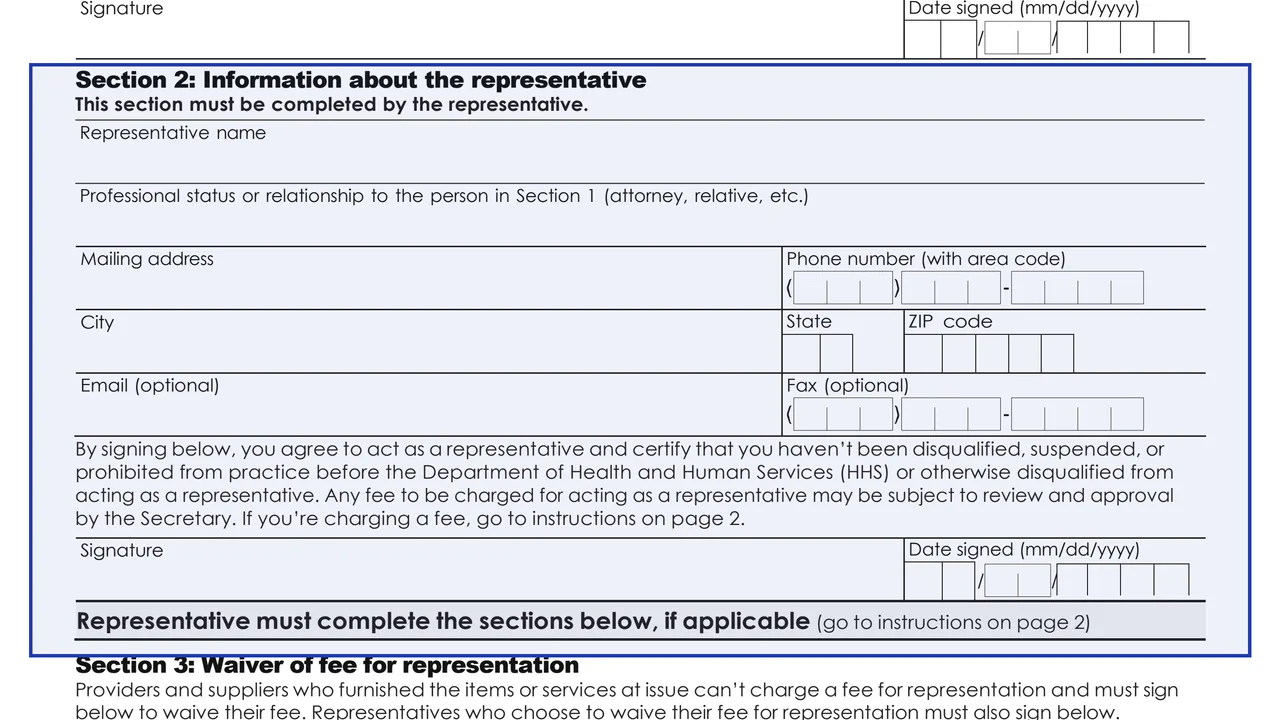
Representative name, professional status or relationship, mailing address, phone number, optional email and fax, and a signature and date under a certification about eligibility to act as a representative.
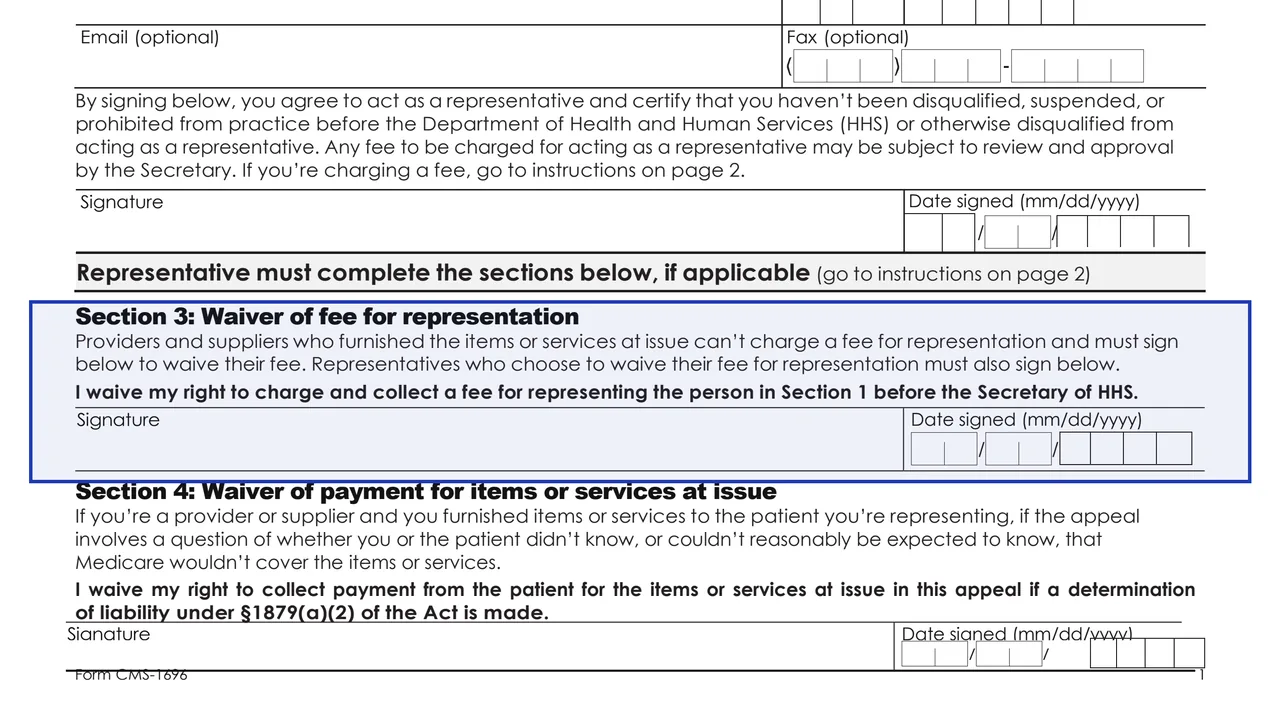
A signature waiving the right to charge and collect a fee for representing the person in Section 1 before the Secretary of HHS.
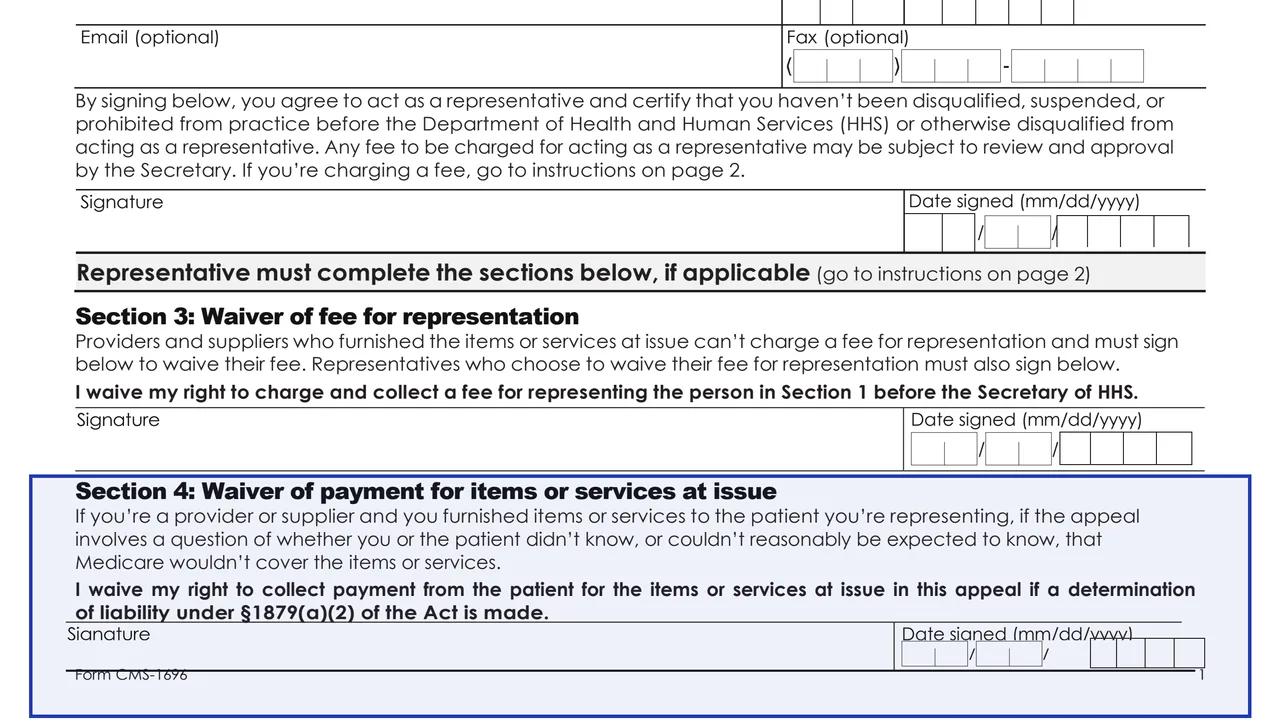
For a provider or supplier representing a patient they furnished items or services to, a signature waiving the right to collect payment from the patient if a liability determination under section 1879(a)(2) of the Act is made.
Page 2 explains how long the appointment is valid, where to send the form, when a representative's fee needs approval, and what OMHA or the Medicare Appeals Council considers when approving a fee.
The form says individuals with a conflict of interest are excluded from serving as representatives of patients before HHS, citing sections 203, 205 and 207 of Title XVIII of the United States Code.
The form says all fields in Sections 1 and 2 are required unless marked optional.
The person appointing the representative enters their name, Medicare Number or NPI (or not applicable), mailing address and phone, then signs and dates it.
The representative adds their details and relationship, then signs to agree to act as a representative and to the certification.
The instructions say Section 3 is required when a representative is required or has agreed to waive a fee, and Section 4 when a provider or supplier represents the patient and liability under section 1879(a)(2) is at issue.
A representative charging a fee for an appeal before the Secretary of HHS completes form OMHA-118 and files it with the request for ALJ hearing, OMHA review or Medicare Appeals Council review, according to the form.
Original Medicare: the address on your Medicare Summary Notice. Medicare Advantage or a drug plan: the form says to contact the plan's member services to find out where to send it.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
Send the form to the address on your Medicare Summary Notice (MSN). If you no longer have the MSN, the form says to call 1-800-MEDICARE (1-800-633-4227) to get the address.
The form says to contact member services at your plan to find out where to send it. The number is on your Evidence of Coverage or Member ID card.
The form says not to send it directly to CMS. The CMS address in the Paperwork Reduction Act notice is for comments on the form.
The form says an appointment is valid for one year from the date it is signed by both the person appointing and the representative, and can be used for other appeals or actions during that year. Unless revoked, it lasts for the duration of the claim, appeal, grievance or request it was filed for.
Contact your Medicare plan or call 1-800-MEDICARE (1-800-633-4227), TTY 1-877-486-2048. The form says Medicare information is available in large print, braille or audio. The CMS page also lists a Spanish version.
The form estimates 15 minutes per notice.

CMS-10106
44 fields, 3 pages

CMS-20027
20 fields, 1 page

CMS-20033
20 fields, 1 page
CMS-20031
20 fields, 2 pages

CMS-1490S
49 fields, 18 pages
The form is signed by two people: the one appointing a representative and the representative.
No tool matches that search.
The form says one year from the date it is signed by both the person appointing and the representative. Unless revoked, the representation lasts for the duration of the claim, appeal, grievance or request it was filed for.
With Original Medicare, the form says to send it to the address on your Medicare Summary Notice. With a Medicare Advantage or prescription drug plan, it says to contact the plan's member services. It says not to send it directly to CMS.
The form says a completed form can be used for other appeals or actions during the one-year period it is valid.
Yes. The form says a provider or supplier who furnished the items or services at issue may represent the patient but may not charge the beneficiary a fee for it, and signs Section 3 to waive the fee.
The form says a fee for an appeal before the Secretary of HHS is approved under 42 CFR 405.910(f) using form OMHA-118. It lists exceptions, including a provider or supplier appellant and a fee for a redetermination or reconsideration.
The instructions say that if the person or entity appointing a representative doesn't have a Medicare number or National Provider Identifier, fill in not applicable.
Yes. The CMS page lists a Spanish version of the form, plus HTML versions in English and Spanish.