Items 1 to 5: facility and address
Name of facility, street address, city and/or county, state and ZIP code.
CMS-1541B
RESPONSIBILITIES OF MEDICARE PARTICIPATING HOSPITALS IN EMERGENCY CASES INVESTIGATION REPORT
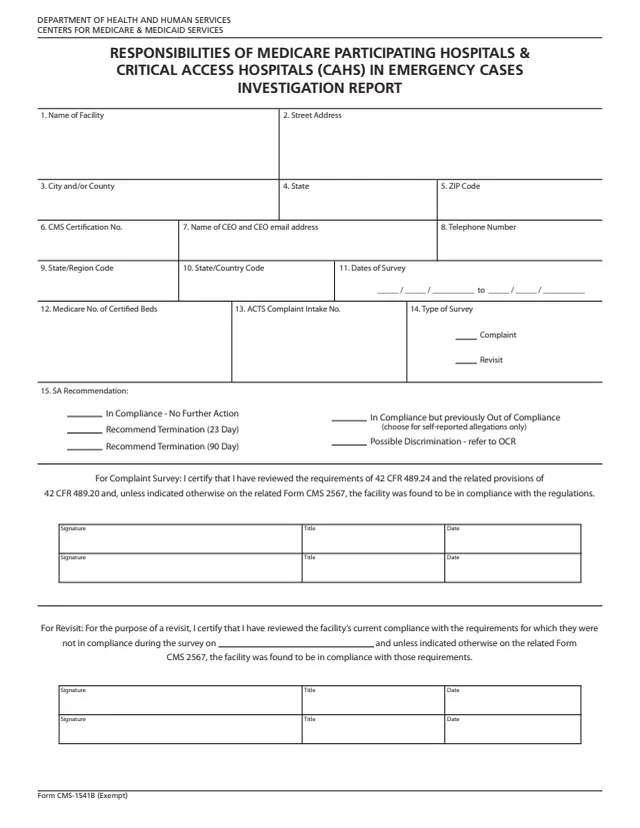
Form CMS-1541B is the Responsibilities of Medicare Participating Hospitals & Critical Access Hospitals (CAHs) in Emergency Cases Investigation Report, from the Centers for Medicare & Medicaid Services (CMS), part of the U.S. Department of Health and Human Services. The CMS forms page lists it as Responsibilities of Medicare Participating Hospitals in Emergency Cases Investigation Report, with a revision date of 2014-09-01 and an OMB number of exempt. The form itself is marked Form CMS-1541B (Exempt).
It is a one-page report. Items 1 to 14 identify the facility, its CMS Certification Number, CEO, number of Medicare certified beds, ACTS complaint intake number, the dates of survey and the type of survey, complaint or revisit. Item 15 is the SA Recommendation, with five boxes.
Two certification blocks follow, one for a complaint survey and one for a revisit, each with two signature lines. Both refer to the related Form CMS-2567. You can fill it out free in your browser on this page and download the result without an account.

Name of facility, street address, city and/or county, state and ZIP code.
CMS Certification No., name of the CEO and CEO email address, telephone number, State/Region Code and State/Country Code.
Dates of survey from and to, Medicare No. of Certified Beds, ACTS Complaint Intake No., and type of survey: Complaint or Revisit.
In Compliance - No Further Action; In Compliance but previously Out of Compliance, which the form says to choose for self-reported allegations only; Recommend Termination (23 Day); Recommend Termination (90 Day); and Possible Discrimination - refer to OCR.
A statement that the requirements of 42 CFR 489.24 and related provisions of 42 CFR 489.20 were reviewed and, unless indicated otherwise on the related Form CMS-2567, the facility was found in compliance. Two signature, title and date lines.
A statement for a revisit with a blank for the date of the earlier survey, again referring to the related Form CMS-2567. Two signature, title and date lines.
The form is numbered items 1 to 15 plus two certification blocks.
Fill in items 1 to 5: the facility name, street address, city and/or county, state and ZIP code.
Fill in items 6 to 10: CMS Certification No., the CEO's name and email address, telephone number and the two codes.
Enter the dates of survey, the number of Medicare certified beds and the ACTS complaint intake number, then check Complaint or Revisit in item 14.
Check a box in item 15. The form says the In Compliance but previously Out of Compliance box is for self-reported allegations only.
Use the complaint survey block or the revisit block. Each has two lines for a signature, title and date. The revisit block also asks for the date of the earlier survey.
The form prints no instructions. These steps follow its items in order.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form does not print a mailing address or say where it is sent.
Both certification blocks say the facility was found in compliance unless indicated otherwise on the related Form CMS-2567.
The complaint survey certification names 42 CFR 489.24 and the related provisions of 42 CFR 489.20.
The form is marked Form CMS-1541B (Exempt). The CMS page lists the O.M.B. number as EXEMPT and the revision date as 2014-09-01.
CMS-2567
22 fields, 5 pages

CMS-807
11 fields, 2 pages

CMS-801
13 fields, 1 page
CMS-1539
51 fields, 2 pages

CMS-2802E
35 fields, 1 page

CMS-10455
38 fields, 1 page
The form does not spell out who fills it in. Its items point to the parties below.
No tool matches that search.
It is the Responsibilities of Medicare Participating Hospitals & Critical Access Hospitals (CAHs) in Emergency Cases Investigation Report from CMS, a one-page report on a complaint survey or revisit.
The form's title names Medicare participating hospitals and critical access hospitals (CAHs). The CMS forms page title names Medicare participating hospitals.
In Compliance - No Further Action, In Compliance but previously Out of Compliance (self-reported allegations only), Recommend Termination (23 Day), Recommend Termination (90 Day), and Possible Discrimination - refer to OCR.
Both certification blocks say the facility was found in compliance unless indicated otherwise on the related Form CMS-2567.
The complaint survey certification says the signer reviewed the requirements of 42 CFR 489.24 and the related provisions of 42 CFR 489.20.
No. The form is marked Exempt, and the CMS page lists its O.M.B. number as EXEMPT.