A. Hospital information
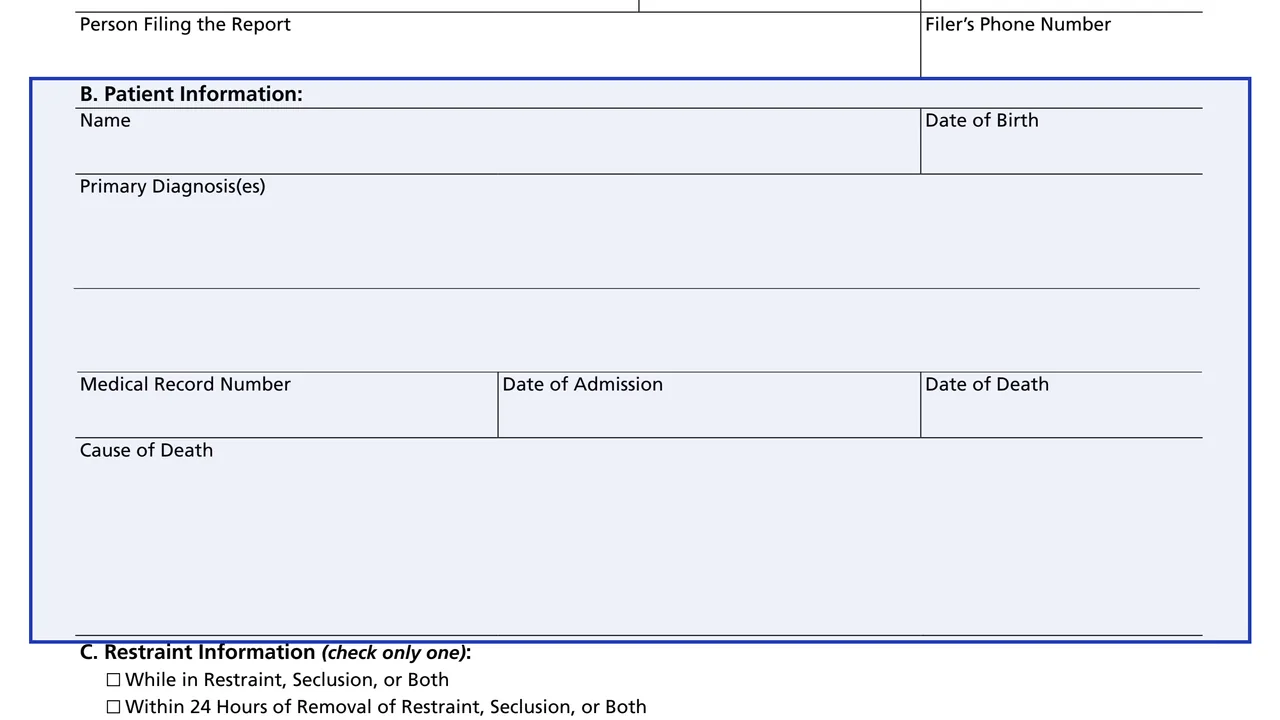
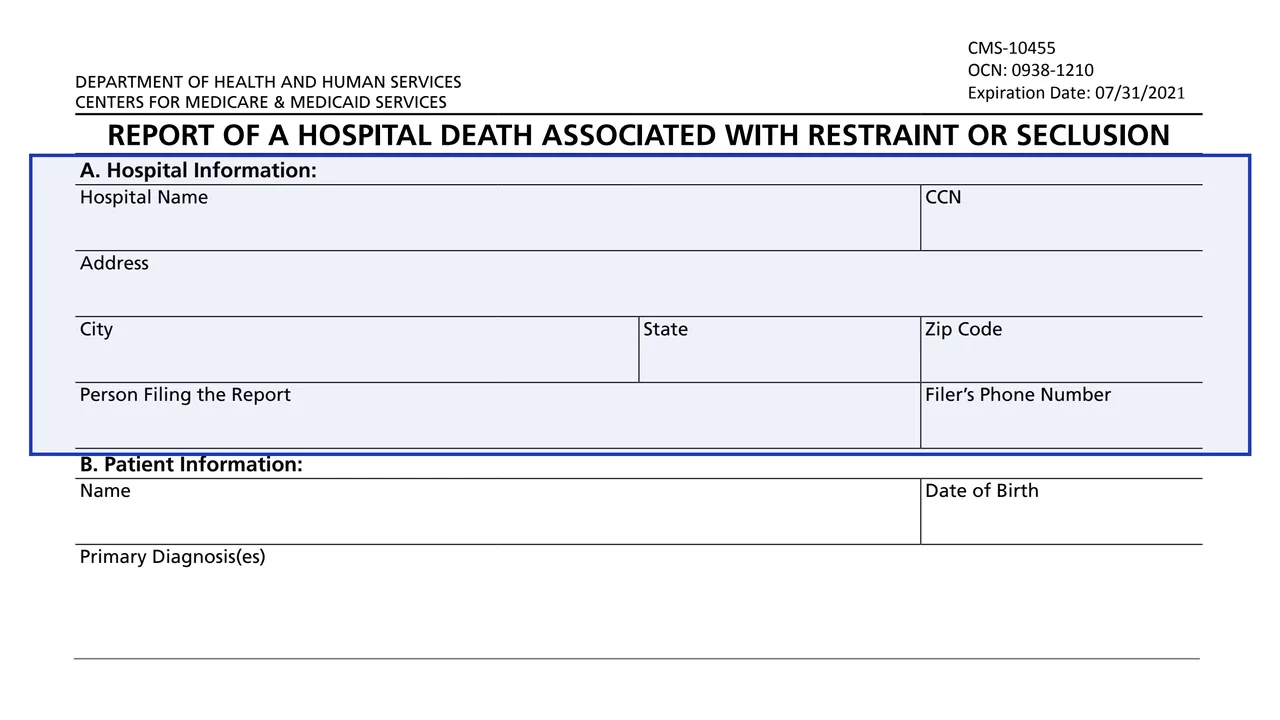
Hospital name, CCN, address, city, state and ZIP code, plus the person filing the report and the filer's phone number.
CMS-10455
Report of a Hospital Death Associated with Restraint or Seclusion

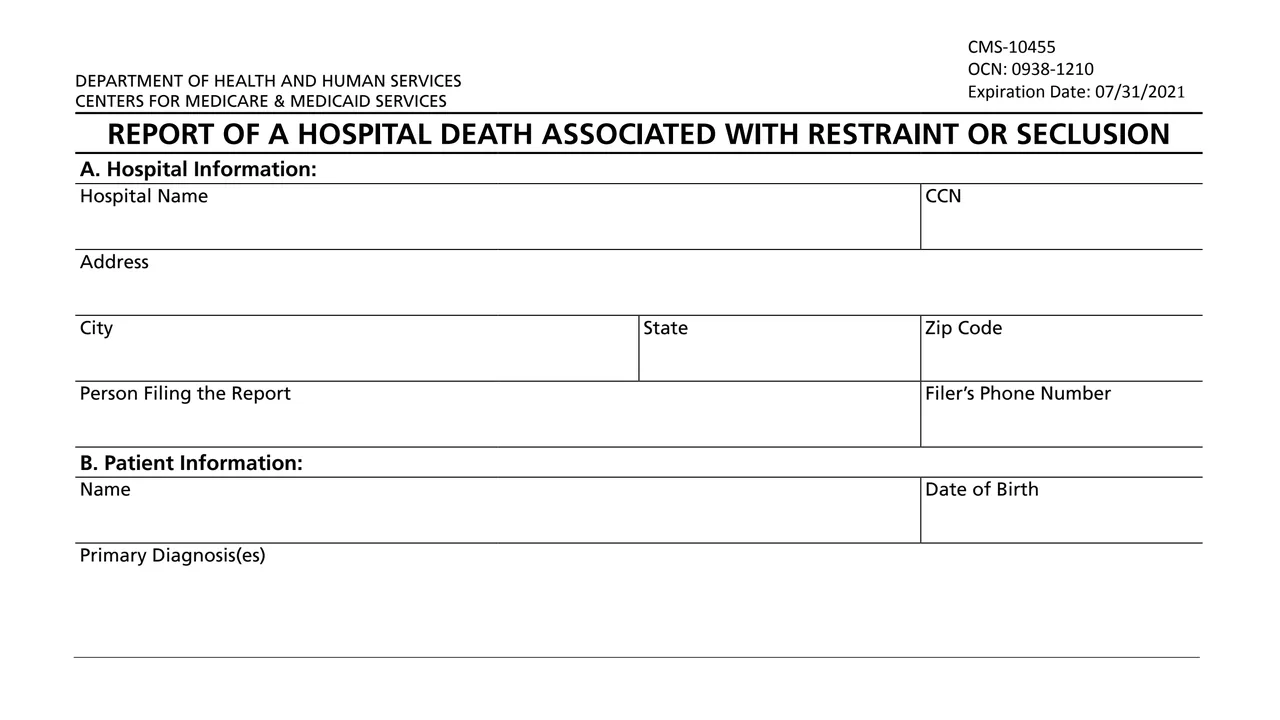
Form CMS-10455 is the Report of a Hospital Death Associated with Restraint or Seclusion from the Centers for Medicare & Medicaid Services, part of the U.S. Department of Health and Human Services. A hospital uses it to report a patient death tied to physical restraint, seclusion or a drug used as a restraint.
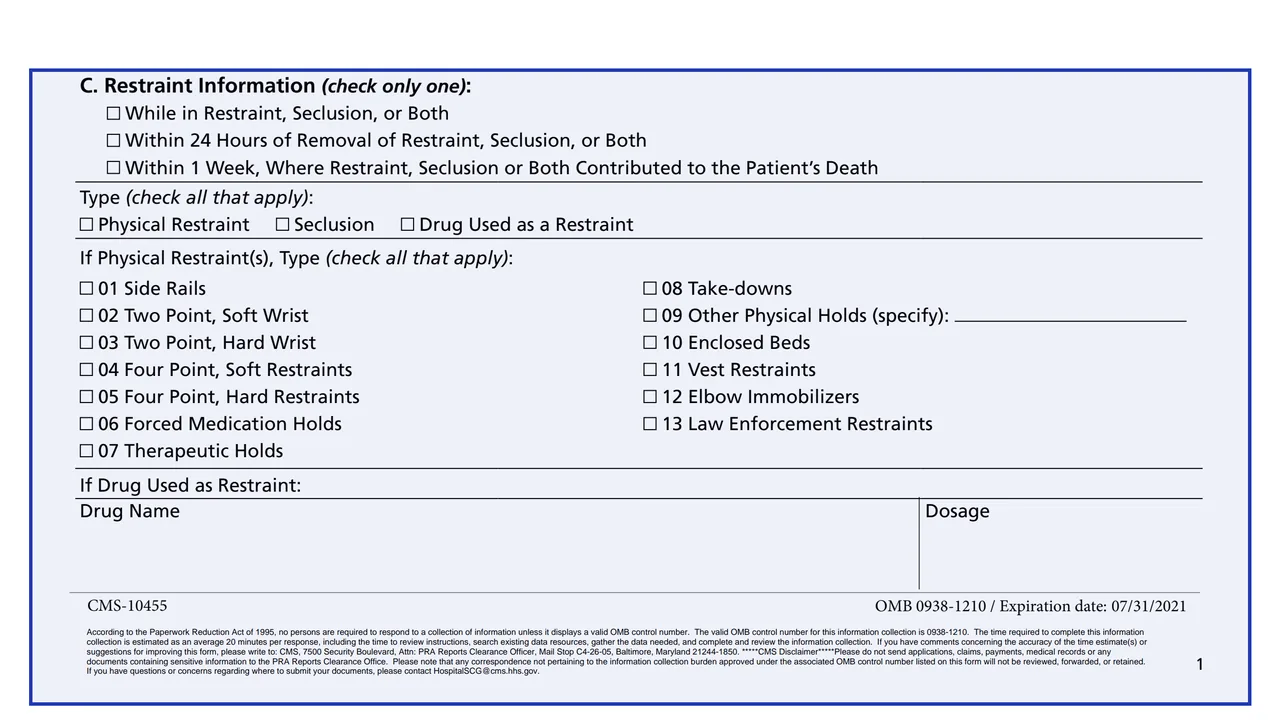
The form has three parts: hospital information with the hospital's CCN and the person filing the report, patient information including diagnoses and cause of death, and restraint information. In the restraint part, the form asks when the death happened in relation to the restraint or seclusion, which types were used, and the kind of physical restraint or the drug name and dosage.
The form carries OMB number 0938-1210 and estimates an average of 20 minutes per response. You can fill it out free in your browser on this page and download the result without an account.
Hospital name, CCN, address, city, state and ZIP code, plus the person filing the report and the filer's phone number.
The patient's name, date of birth, primary diagnosis or diagnoses, medical record number, date of admission, date of death and cause of death.
Three timing choices, with the instruction to check only one: while in restraint or seclusion, within 24 hours of removal, or within 1 week where it contributed to the death.
Check all that apply: Physical Restraint, Seclusion, or Drug Used as a Restraint.
A numbered list from 01 to 13, check all that apply, including side rails, two point and four point restraints, therapeutic holds, take-downs, enclosed beds, vest restraints and law enforcement restraints, with space to specify other physical holds.
If a drug was used as a restraint, the drug name and the dosage.
The form is one page with three lettered sections.
Fill in the hospital name, CCN and full address, then the name and phone number of the person filing the report.
Add the patient's name, date of birth, primary diagnoses, medical record number, admission date, date of death and cause of death.
In Section C, the form says to check only one of the three choices about when the death happened.
Check every type that applies. For physical restraint, check each numbered type that applies and specify any other physical hold.
If a drug was used as a restraint, write the drug name and the dosage.
The form does not print a submission address. For questions about where to submit documents, it gives the email [email protected].
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form does not list a mailing address for the report. It says to contact [email protected] with questions or concerns about where to submit documents.
The CMS address in Baltimore printed at the bottom is for comments on the time estimate or the form. The form says not to send applications, claims, payments, medical records or other sensitive documents there.
The form shows OMB number 0938-1210 with an expiration date of 07/31/2021. The CMS page lists an OMB expiration date of 2026-01-31 and a revision date of 2018-07-19.
The form estimates an average of 20 minutes per response, including reviewing instructions, gathering the data and completing the form.
The form is a hospital report. Section C names three situations it covers, and the form says to check only one.
No tool matches that search.
It is the Report of a Hospital Death Associated with Restraint or Seclusion. It records the hospital, the patient, when the death happened in relation to restraint or seclusion, and the type of restraint used.
Section C lists three: a death while in restraint, seclusion or both; within 24 hours of removal of restraint, seclusion or both; or within 1 week, where restraint, seclusion or both contributed to the death. The form says to check only one.
Yes. Drug Used as a Restraint is one of the types to check, and the form asks for the drug name and dosage.
The form does not print a submission address. It says to contact [email protected] with questions or concerns about where to submit documents.
The Baltimore address is for the PRA Reports Clearance Officer. The form says not to send applications, claims, payments, medical records or documents with sensitive information there.
The form estimates an average of 20 minutes per response.