Header and plan information (items 1 to 3a)
The type of transaction, the predetermination/preauthorization number, the company or plan name and address, and the payer ID.
CMS-10883
ADA Dental Claim Form
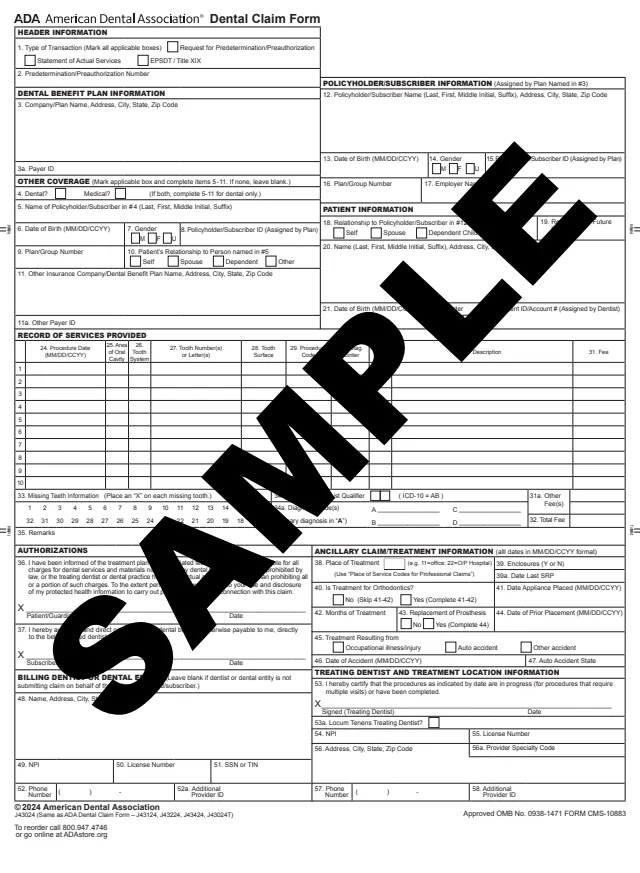
Form CMS-10883 is the American Dental Association (ADA) Dental Claim Form. The CMS forms page lists it as the ADA Dental Claim Form with OMB No. 0938-1471, a revision date of 2024-08-01 and an OMB expiration date of 2027-05-31. The form itself carries a 2024 American Dental Association copyright and the code J43024.
The form is a claim sent to a third-party payer, which its instructions describe as an insurance company or dental benefit plan. Item 1 offers three transaction types: Statement of Actual Services, Request for Predetermination/Preauthorization, and EPSDT / Title XIX. The rest of page 1 covers the dental benefit plan, other coverage, the policyholder or subscriber, the patient, a record of up to 10 services with diagnosis codes, authorizations, ancillary claim and treatment information, the billing dentist or dental entity, and the treating dentist.
Page 2 highlights certain completion instructions and says the comprehensive instructions are posted on the ADA's website. You can fill it out free in your browser on this page and download the result without an account.
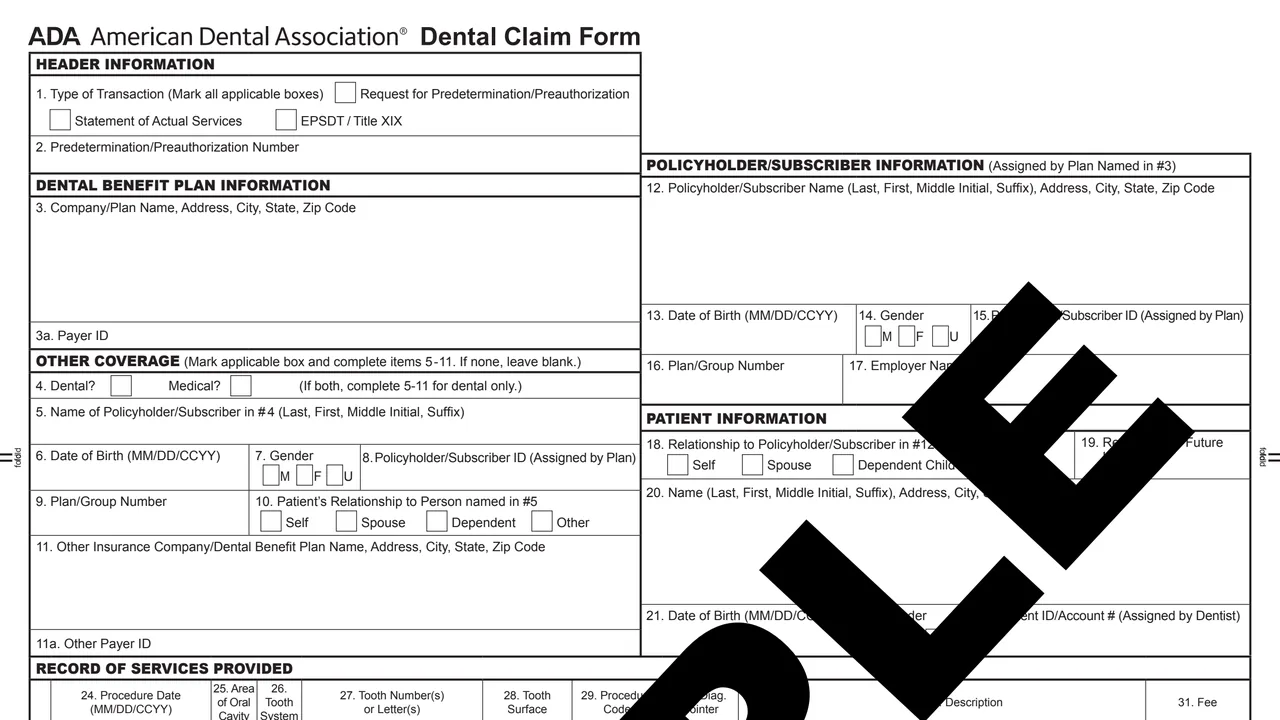
The type of transaction, the predetermination/preauthorization number, the company or plan name and address, and the payer ID.
Whether there is other dental or medical coverage, with the other policyholder's name, date of birth, gender, ID, plan/group number, the patient's relationship to them, and the other plan's name, address and payer ID. The form says to leave these blank if there is none.
The policyholder or subscriber's name, address, date of birth, gender, ID, plan/group number and employer, then the patient's relationship to them, name, address, date of birth, gender and patient ID/account number assigned by the dentist.
Ten lines for procedure date, area of oral cavity, tooth system, tooth numbers or letters, surface, procedure code, diagnosis pointer, quantity, description and fee, plus other fees, total fee, a missing teeth chart, diagnosis codes and remarks.
Patient or guardian and subscriber signatures, place of treatment, enclosures, date of last SRP, orthodontic treatment details, replacement of a prosthesis, and whether treatment resulted from an occupational illness or injury, auto accident or other accident.
Name, address, NPI, license number, SSN or TIN, phone and additional provider ID for the billing dentist or dental entity, and the treating dentist's signature, locum tenens box, NPI, license number, address, specialty code and phone.
The form has 58 numbered items on page 1 and highlighted instructions on page 2.
Mark all applicable boxes in item 1 and add a predetermination/preauthorization number in item 2 if there is one.
The instructions say all dates include the four-digit year (MM/DD/CCYY) and give the gender codes as M for male, F for female and U for unknown. Full names and addresses with ZIP codes go in each name and address field.
Fill one line per procedure in the Record of Services Provided. If there are more procedures than lines, the instructions say to list the rest on a separate, fully completed claim form.
Item 34 takes the qualifier AB for ICD-10-CM and item 34a takes up to four diagnosis codes, with the primary next to the letter A. Item 29a points each procedure to codes A to D.
Enter the 2-digit Place of Service Code in item 38, for example 11 for office or 22 for outpatient hospital, and the provider specialty code in item 56a. The instructions say the general Dentist code 122300000X may be used instead of the other codes.
Collect the signatures in items 36, 37 and 53 that apply, then send the claim to the payer named in item 3. The form is laid out so that address shows in a standard #9 window envelope.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
To the third-party payer named in item 3, which the instructions describe as the insurance company or dental benefit plan. The instructions say to fold the form using the tick marks in the margin so the address fits a standard #9 window envelope.
The instructions say to complete the entire form and attach the primary payer's Explanation of Benefits. The amount the primary carrier paid may also be noted in Remarks, item 35.
Page 2 says the comprehensive ADA Dental Claim Form completion instructions are posted on the ADA's website at ADA.org/en/publications/cdt/ada-dental-claim-form.
Page 2 lists common Place of Service Codes: 11 Office, 12 Home, 21 Inpatient Hospital, 22 Outpatient Hospital, 31 Skilled Nursing Facility and 32 Nursing Facility. It points to cms.gov for the full list and to nucc.org for the full provider taxonomy code set.
The form shows Approved OMB No. 0938-1471. The CMS page lists an OMB expiration date of 2027-05-31.
The PDF on the CMS page carries a large SAMPLE watermark across page 1. The form prints ADA reorder details: 800.947.4746 or ADAstore.org.

CMS-1490S
49 fields, 18 pages

CMS-855I
513 fields, 26 pages

CMS-588
39 fields, 4 pages

CMS-20027
20 fields, 1 page

CMS-20033
20 fields, 1 page
The form has separate parts for the patient, the subscriber, the billing dentist or dental entity and the treating dentist.
No tool matches that search.
It is the American Dental Association (ADA) Dental Claim Form, listed on the CMS forms page under OMB No. 0938-1471. It is a claim sent to an insurance company or dental benefit plan.
Item 1 offers Request for Predetermination/Preauthorization as one type of transaction, next to Statement of Actual Services and EPSDT / Title XIX.
The instructions say to list the remaining procedures on a separate, fully completed claim form.
The instructions say the form supports up to four diagnosis codes per dental procedure. They go in item 34a with the primary next to A, item 34 takes the qualifier AB for ICD-10-CM, and item 29a links each procedure to them.
The form says to leave items 48 to 52a blank if the dentist or dental entity is not submitting the claim on behalf of the patient or insured/subscriber.
The instructions say to enter the 2-digit Place of Service Code for Professional Claims, for example 11 for office, 12 for home or 22 for outpatient hospital.
Page 2 says the comprehensive completion instructions are posted on the ADA's website at ADA.org/en/publications/cdt/ada-dental-claim-form.