Section A: certification type and date
The initial date, plus a revised or recertification date where one applies. The instructions say a revised or recertified CMN always gives the initial date as well.
CMS-10269
CMN Positive Airway Pressure (PAP)Devices for Obstructive Sleep Apnea
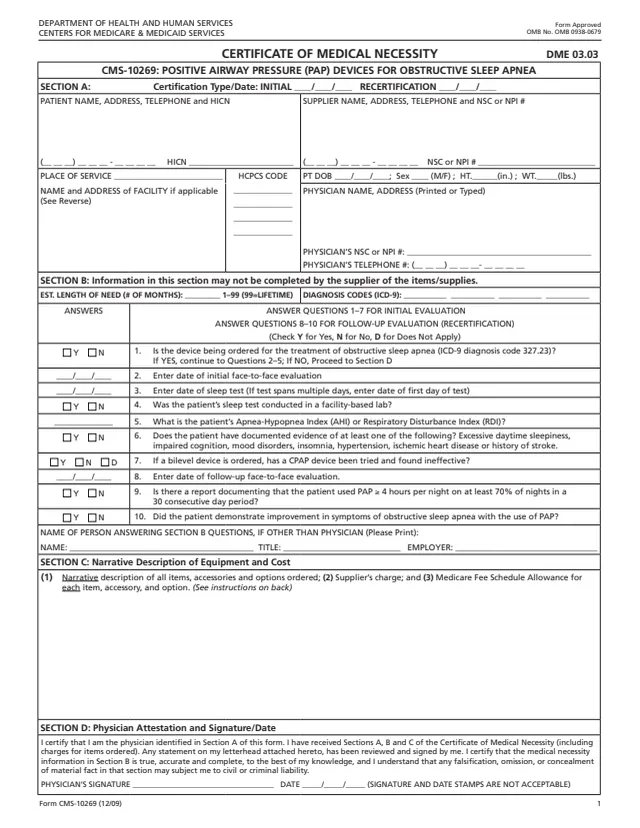
Form CMS-10269 is the Certificate of Medical Necessity (CMN) for Positive Airway Pressure (PAP) Devices for Obstructive Sleep Apnea from the Centers for Medicare & Medicaid Services (CMS), part of the U.S. Department of Health and Human Services. It is marked DME 03.03. The form is completed by the supplier of the device and the ordering physician for a Medicare patient, and its instructions say the questions in Section B gather clinical information to determine medical necessity.
The form has four sections. Section A identifies the patient, supplier, place of service, HCPCS codes and physician, and may be completed by the supplier. Section B asks for the estimated length of need, diagnosis codes and 10 questions, and may not be completed by the supplier. Section C describes the equipment and its cost, and Section D is the physician's attestation and signature.
The form says signature and date stamps are not acceptable. You can fill it out free in your browser on this page and download the result without an account.

The initial date, plus a revised or recertification date where one applies. The instructions say a revised or recertified CMN always gives the initial date as well.
Patient and supplier details, place of service, facility name and address if applicable, HCPCS codes, the patient's date of birth, sex, height and weight, and the physician's name, address, NSC or NPI number and phone.
Estimated length of need in months from 1 to 99, where 99 means lifetime, and ICD-9 diagnosis codes. The instructions ask for the primary code first and up to 3 more.
Whether the device is ordered for obstructive sleep apnea (ICD-9 code 327.23), the dates of the initial face-to-face evaluation and sleep test, whether the test was in a facility-based lab, the AHI or RDI, documented symptoms, and for a bilevel device whether CPAP was tried.
The date of the follow-up face-to-face evaluation, whether a report documents PAP use of 4 hours or more per night on at least 70% of nights in a 30 consecutive day period, and whether symptoms improved with PAP.
Section C: a narrative description of all items, accessories and options ordered, the supplier's charge and the Medicare fee schedule allowance for each. Section D: the physician attestation, signature and date.
Enter the certification type and date, patient and supplier details, place of service, HCPCS codes and physician information. The instructions say procedure codes that do not require certification are not listed on the CMN.
Describe every item, option, accessory, supply and drug ordered, with the supplier's charge and the Medicare fee schedule allowance for each, where applicable.
Enter the length of need and diagnosis codes, then answer questions 1 to 7 for an initial evaluation or 8 to 10 for a recertification. The form says that if the answer to question 1 is no, proceed to Section D.
The physician reviews Sections A, B and C, then signs and dates Section D. The form says signature and date stamps are not acceptable.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form does not print a submission address. The CMS address on page 2 is for comments on the time estimate or suggestions for improving the form.
The instructions say a revised certification is completed when the physician changes the order based on the patient's changing clinical needs, and that the initial date is always given along with the revised or recertification date.
Only the physician signs, in Section D. The form says signature and date stamps are not acceptable.
Section D says any falsification, omission or concealment of material fact in Section B may subject the physician to civil or criminal liability.
The instructions give examples: patient's home is 12, skilled nursing facility is 31 and ESRD facility is 65, and point to the DME MAC supplier manual for the full list.
The form estimates an average of 15 minutes per response, including reviewing the instructions and gathering the data. It shows OMB No. 0938-0679.
CMS-484
95 fields, 2 pages
CMS-847
53 fields, 2 pages
CMS-849
32 fields, 2 pages
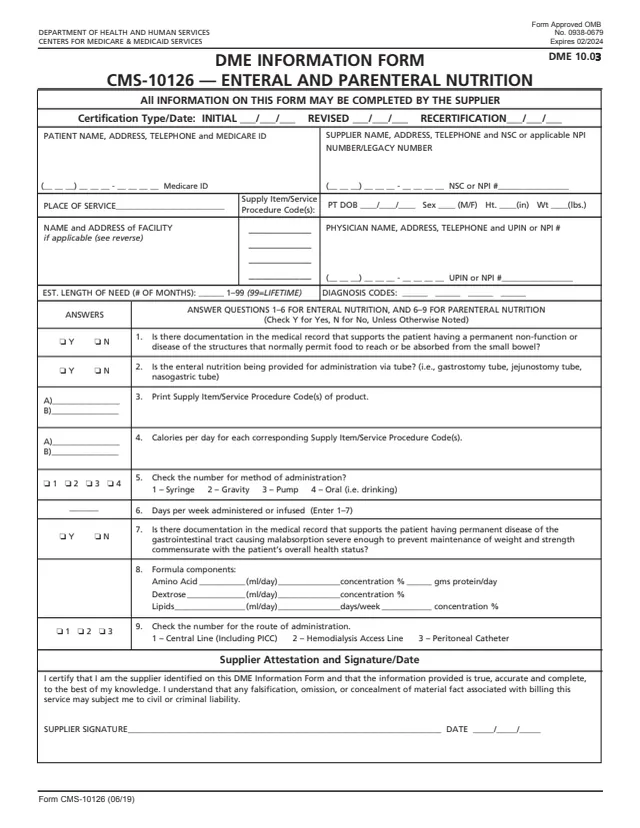
CMS-10126
96 fields, 2 pages

CMS-855S
1,031 fields, 39 pages
The form splits the work between the supplier and the physician, section by section.
No tool matches that search.
The form splits it: the supplier may complete Section A and completes Section C, Section B may not be completed by the supplier, and the physician completes and signs Section D.
No. The form says information in Section B may not be completed by the supplier. A non-physician clinician or physician employee may complete it, but the ordering physician reviews it and signs the CMN.
The form says to answer questions 1 to 7 for an initial evaluation and questions 8 to 10 for a follow-up evaluation (recertification).
The form says 99 means lifetime. The instructions say to enter 99 if the physician expects the patient to need the item for the rest of their life.
No. The form says signature and date stamps are not acceptable.
It asks for ICD-9 diagnosis codes, and question 1 names ICD-9 code 327.23 for obstructive sleep apnea.
The form estimates an average of 15 minutes per response, including reviewing the instructions, gathering the data and reviewing the information.