Section I: Patient information
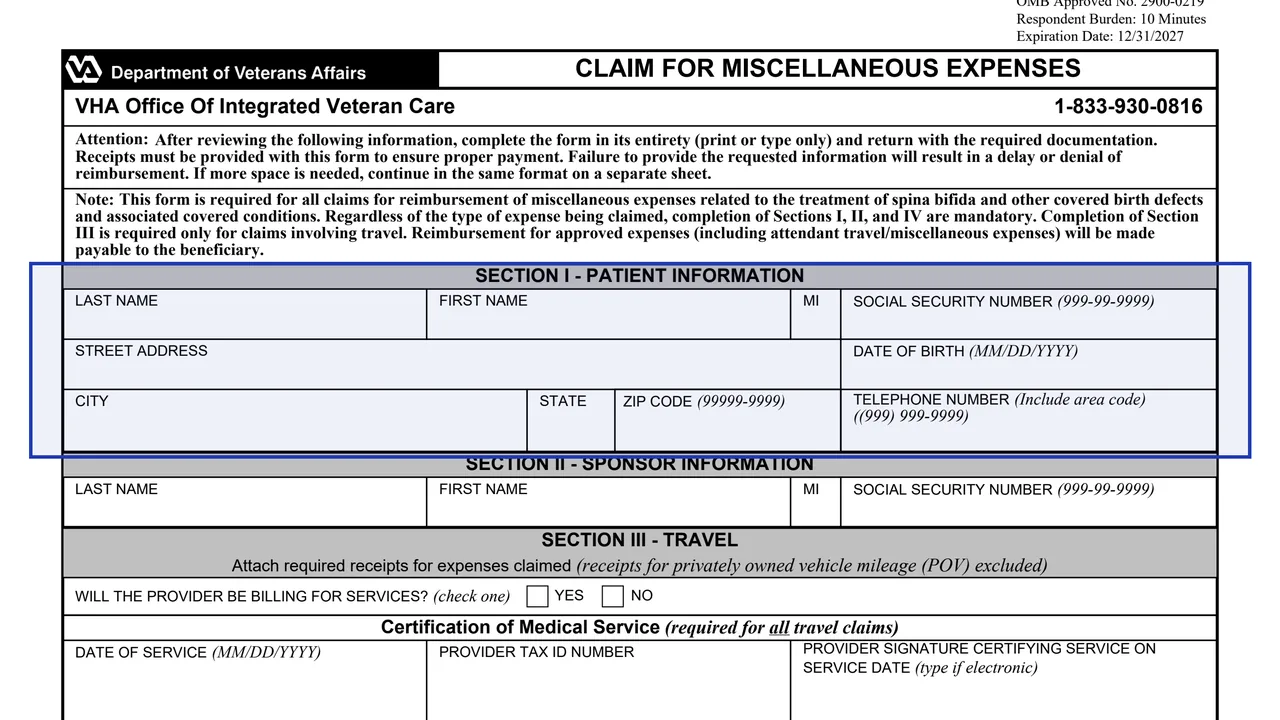
Last name, first name, middle initial, Social Security number, street address, date of birth, city, state, ZIP code and telephone number.
10-7959e
Claim for Miscellaneous Expenses
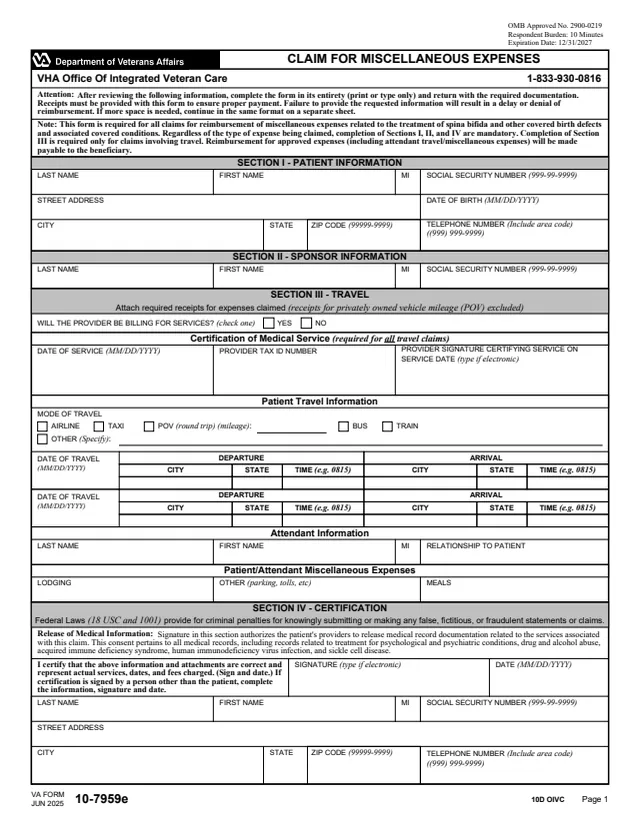
VA Form 10-7959e is the U.S. Department of Veterans Affairs Claim for Miscellaneous Expenses, issued by the VHA Office of Integrated Veteran Care. The form says it is required for all claims for reimbursement of miscellaneous expenses related to the treatment of spina bifida and other covered birth defects and associated covered conditions. Page 2 lists two programs: the Spina Bifida Health Care Program and Children of Women Vietnam Veterans.
The form has four sections. It says Sections I, II and IV are mandatory regardless of the type of expense being claimed, and Section III is required only for claims involving travel. Receipts go with the form, and the form says reimbursement for approved expenses, including attendant travel and miscellaneous expenses, is made payable to the beneficiary.
You can fill out the PDF free in your browser on this page and download the result without an account.
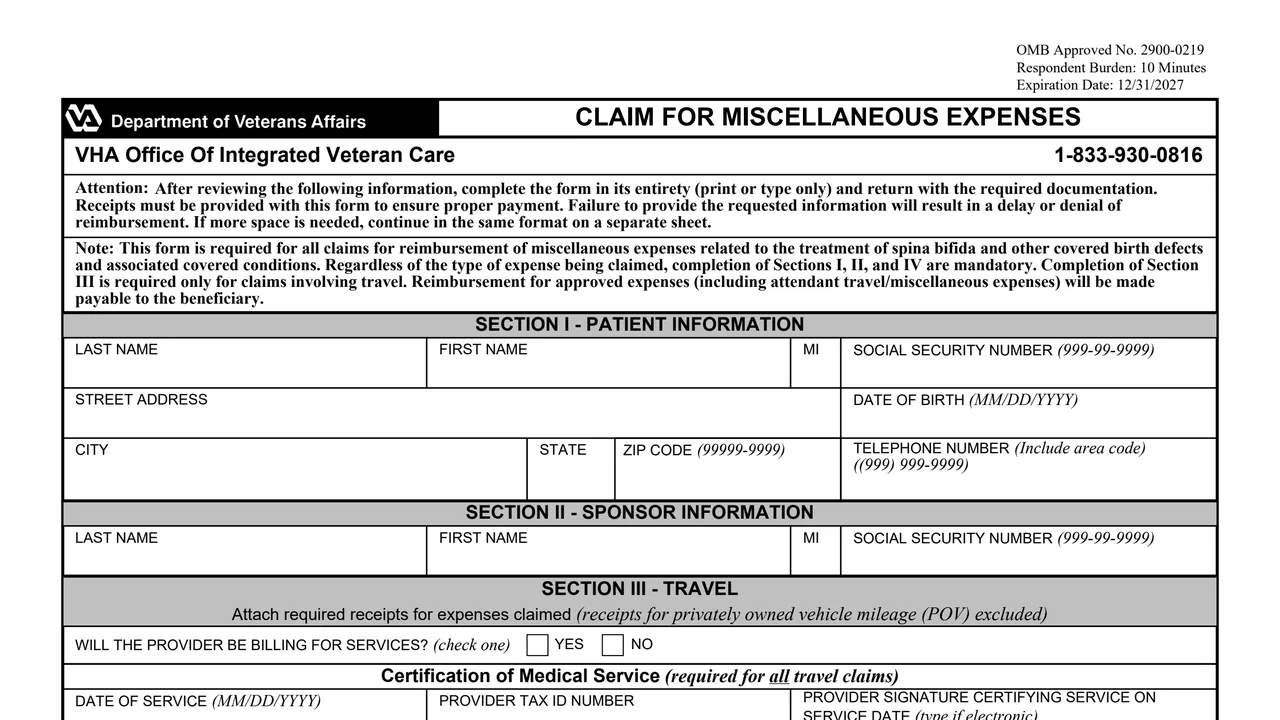
Last name, first name, middle initial, Social Security number, street address, date of birth, city, state, ZIP code and telephone number.
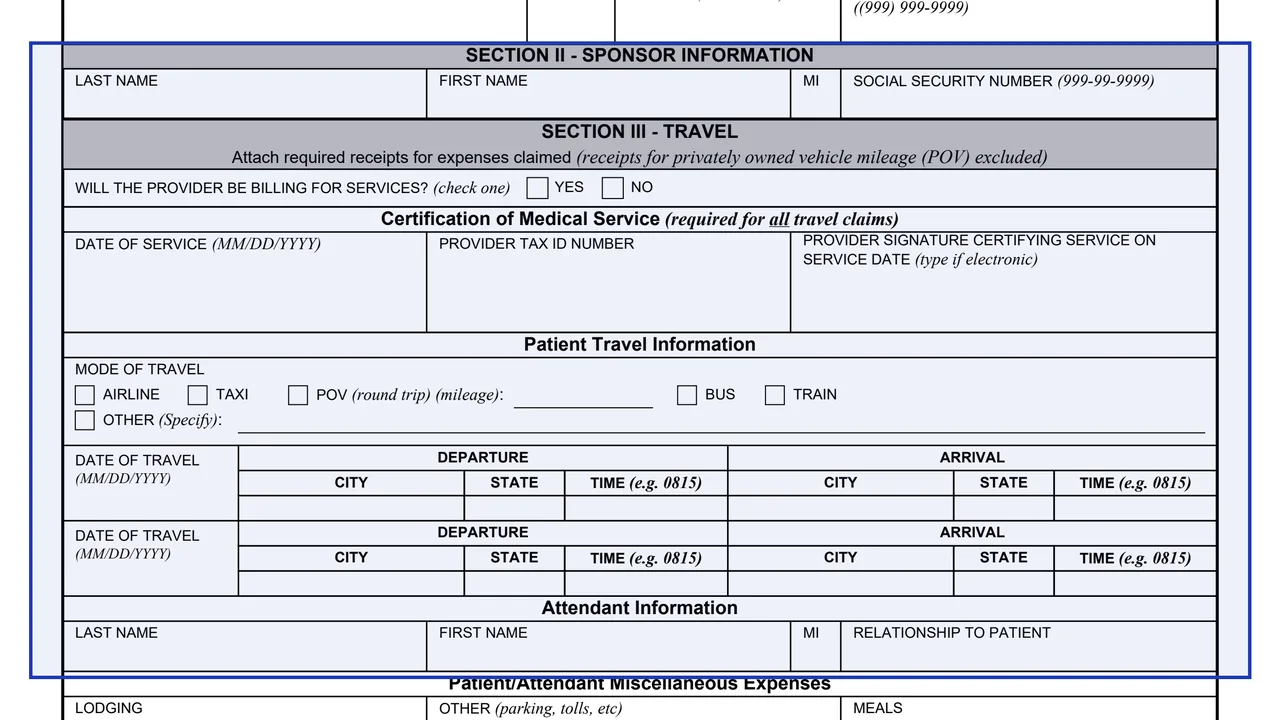
The sponsor's last name, first name, middle initial and Social Security number.
Whether the provider will be billing for services, then the Certification of Medical Service with date of service, provider tax ID number and provider signature.
Mode of travel (airline, taxi, POV round trip mileage, bus, train or other), two travel dates with departure and arrival city, state and time, attendant details, lodging, other costs such as parking and tolls, and meals.
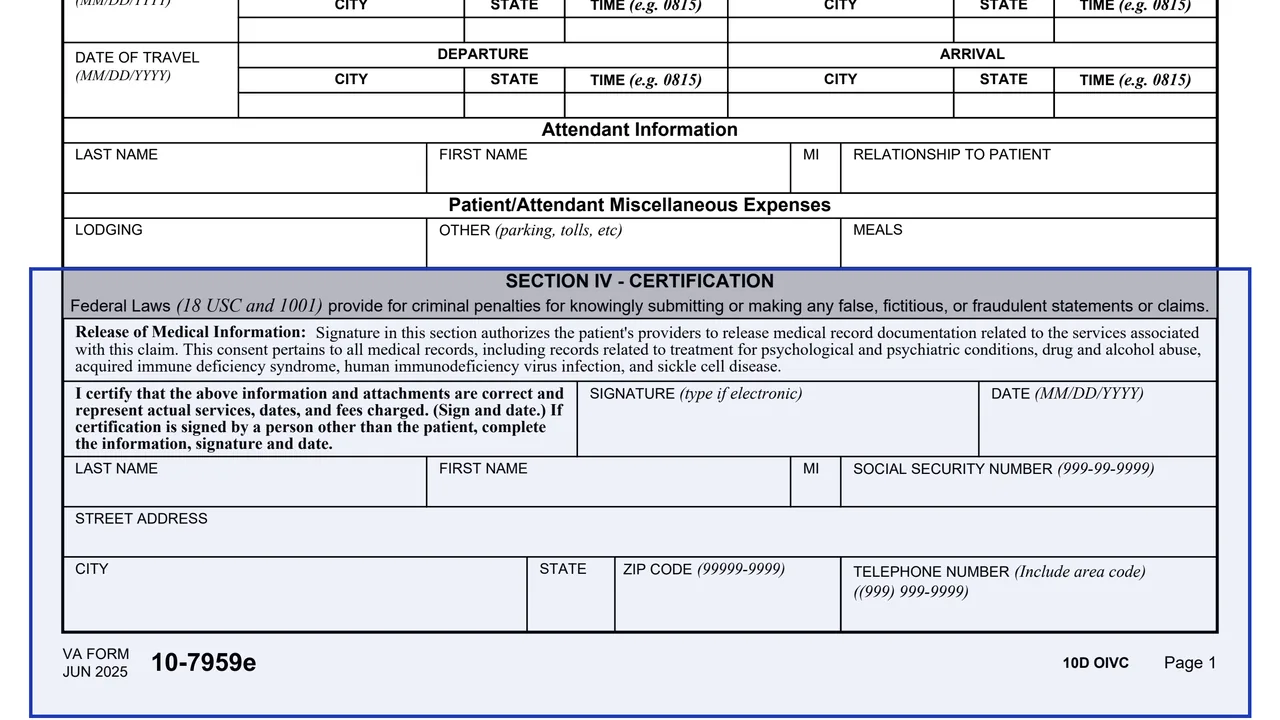
A release of medical information that authorizes the patient's providers to release medical record documentation for the claim, and a certification that the information and attachments represent actual services, dates and fees charged.
The Privacy Act notice, the burden statement with an average of 10 minutes per respondent, and the addresses of the two programs.
The form says receipts must be provided with it to ensure proper payment. Section III says receipts for privately owned vehicle (POV) mileage are excluded.
The form says to print or type only and, if more space is needed, to continue in the same format on a separate sheet.
For a travel claim, list the trip and expenses, and have the provider complete the Certification of Medical Service.
Sign and date the certification. The form says the signature may be typed if electronic.
Page 2 lists the mailing address, phone and fax number for the Spina Bifida Health Care Program and for Children of Women Vietnam Veterans.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
VHA Office of Integrated Veteran Care, Spina Bifida Health Care Benefits Program, P.O. Box 400, Spring City, PA 19475.
VHA Office of Integrated Veteran Care, Children of Women Vietnam Veterans, P.O. Box 400, Spring City, PA 19475.
Both programs list Phone: 1-833-930-0816 and Fax: 1-303-331-7807.
The current edition is dated JUN 2025. Its OMB control number is 2900-0219, which expires 12/31/2027.
10-7959A
42 fields, 2 pages
10-7959C
51 fields, 2 pages
10-7959D
57 fields, 2 pages

10-7959f-2
15 fields, 2 pages
The form names the people who fill in or sign each part.
No tool matches that search.
The form says it is required for all claims for reimbursement of miscellaneous expenses related to the treatment of spina bifida and other covered birth defects and associated covered conditions.
The form says Sections I, II and IV are mandatory regardless of the type of expense being claimed. Section III is required only for claims involving travel.
The form says receipts must be provided with it to ensure proper payment, and that failure to provide the requested information will result in a delay or denial of reimbursement. Receipts for POV mileage are excluded.
The form says reimbursement for approved expenses, including attendant travel and miscellaneous expenses, will be made payable to the beneficiary.
For travel claims, yes. The form says the Certification of Medical Service, with the provider's signature certifying service on the service date, is required for all travel claims.
The form says the signature authorizes the patient's providers to release medical record documentation related to the services associated with the claim.
Page 2 lists P.O. Box 400, Spring City, PA 19475 for both the Spina Bifida Health Care Benefits Program and Children of Women Vietnam Veterans, with fax 1-303-331-7807.