Section I: Patient information
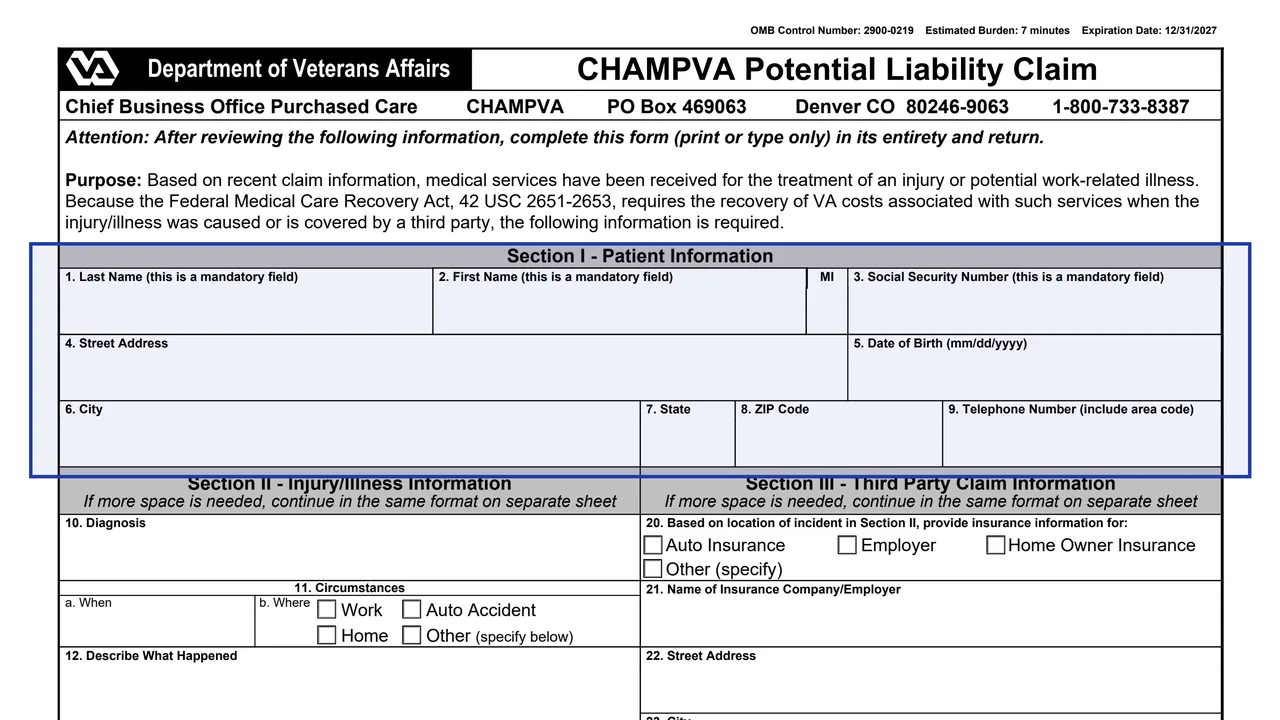
Items 1 to 9: last name, first name and Social Security number, which the form marks as mandatory fields, then street address, date of birth, city, state, ZIP code and telephone number.
10-7959D
CHAMPVA Potential Liability Claim
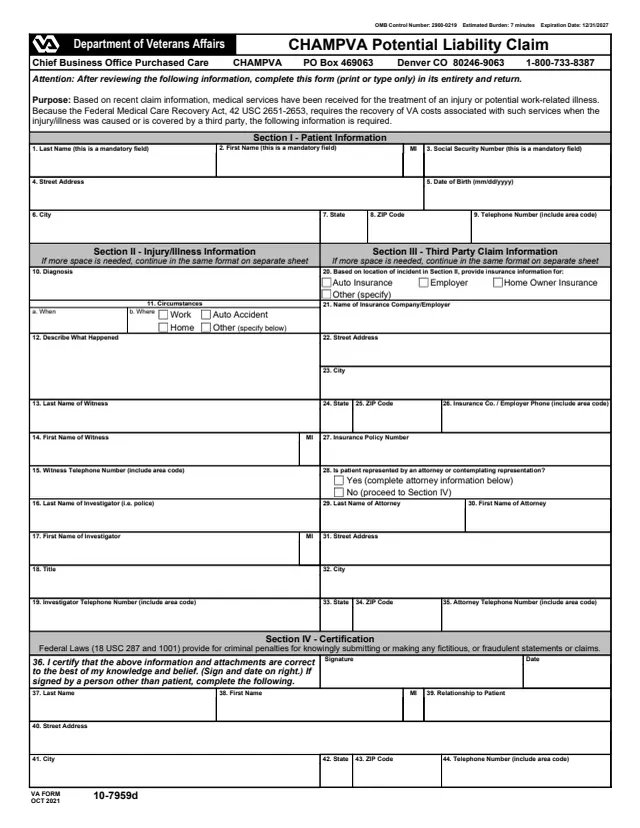
VA Form 10-7959D is the U.S. Department of Veterans Affairs CHAMPVA Potential Liability Claim. The form says it is based on recent claim information showing that medical services were received for the treatment of an injury or potential work-related illness. It explains that the Federal Medical Care Recovery Act, 42 USC 2651-2653, requires the recovery of VA costs associated with such services when the injury or illness was caused or is covered by a third party, so the information on the form is required.
The form asks for it to be completed in its entirety, print or type only, and returned. Page 1 has four sections: patient information, injury or illness information, third party claim information and a certification. Page 2 holds the Privacy Act and Paperwork Reduction Act notices, with an estimated burden of 7 minutes.
You can fill out the PDF free in your browser on this page and download the result without an account.
Items 1 to 9: last name, first name and Social Security number, which the form marks as mandatory fields, then street address, date of birth, city, state, ZIP code and telephone number.
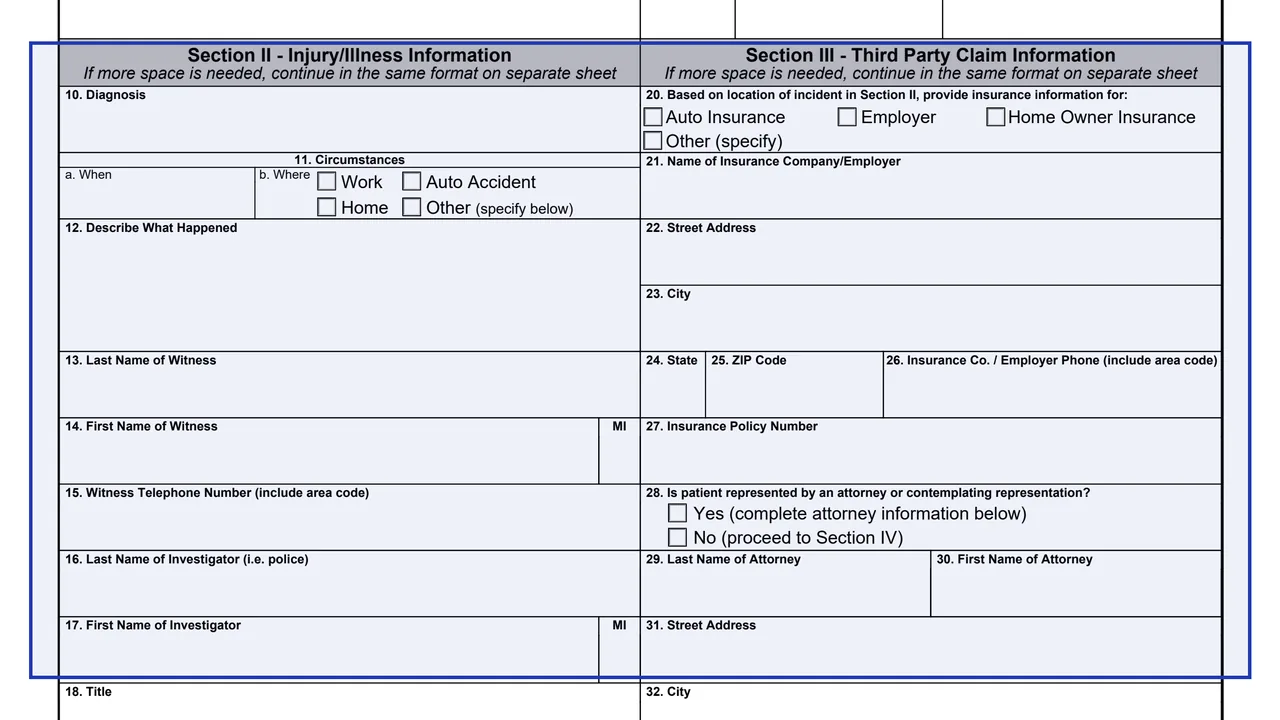
Items 10 to 19: the diagnosis, when and where it happened (Work, Home, Auto Accident or Other), a description of what happened, and witness and investigator details.
Items 20 to 27: based on the location of the incident, insurance information for auto insurance, an employer, home owner insurance or other, with name, address, phone and policy number.
Item 28 asks whether the patient is represented by an attorney or contemplating representation. A yes leads to the attorney's name, address and phone in Items 29 to 35.
Item 36 certifies that the information and attachments are correct to the best of the signer's knowledge and belief, with signature and date. Items 37 to 44 are for a signer other than the patient.
The Privacy Act information, the Paperwork Reduction Act statement with an estimated 7 minutes per response, and the purpose statement repeated.
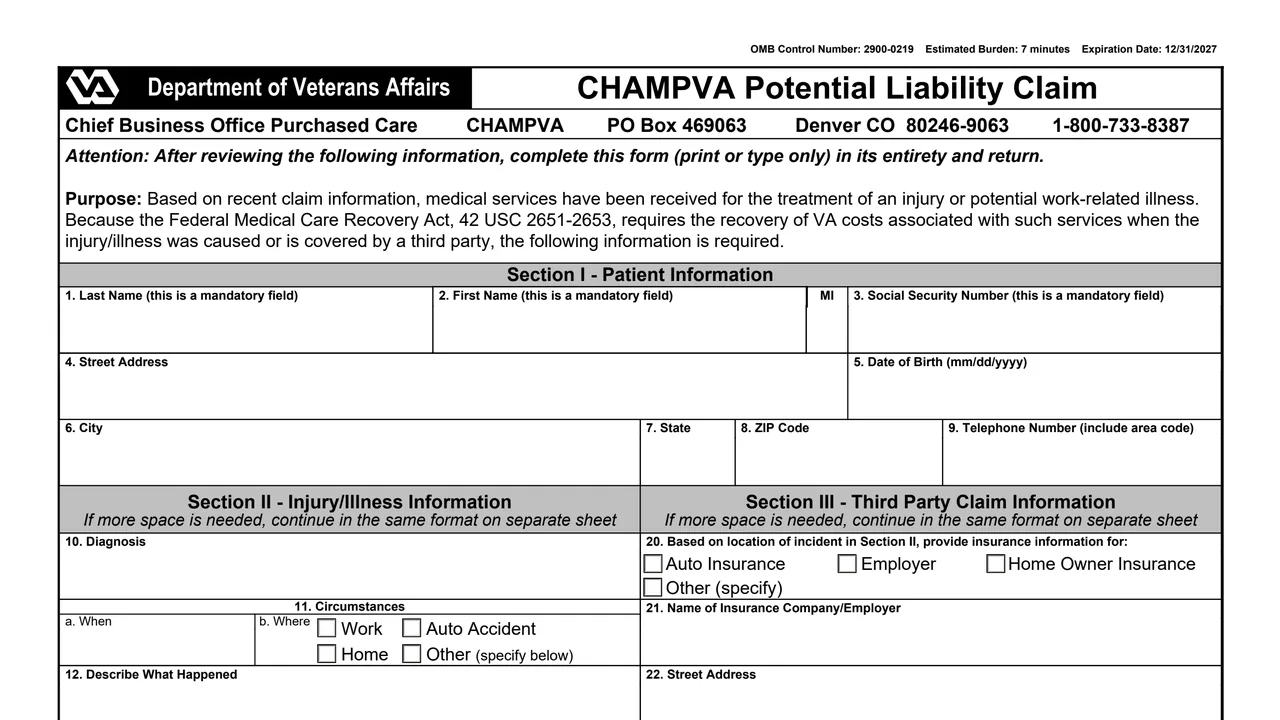
The top of page 1 explains that the form follows recent claim information and cites the Federal Medical Care Recovery Act.
The form says to print or type only. Sections II and III say that if more space is needed, continue in the same format on a separate sheet.
Give the insurer or employer details in Section III and answer Item 28. The form says a No answer proceeds to Section IV.
Sign and date the certification in Item 36. If someone other than the patient signs, that person completes Items 37 to 44.
The form asks for it to be returned. Its header lists the CHAMPVA address in Denver and the phone number 1-800-733-8387.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
Department of Veterans Affairs, Chief Business Office Purchased Care, CHAMPVA, PO Box 469063, Denver CO 80246-9063.
The header lists 1-800-733-8387, which the Paperwork Reduction Act statement calls the CHAMPVA Help Line.
The current edition is dated OCT 2021. It carries OMB Control Number 2900-0219, with an expiration date of 12/31/2027.
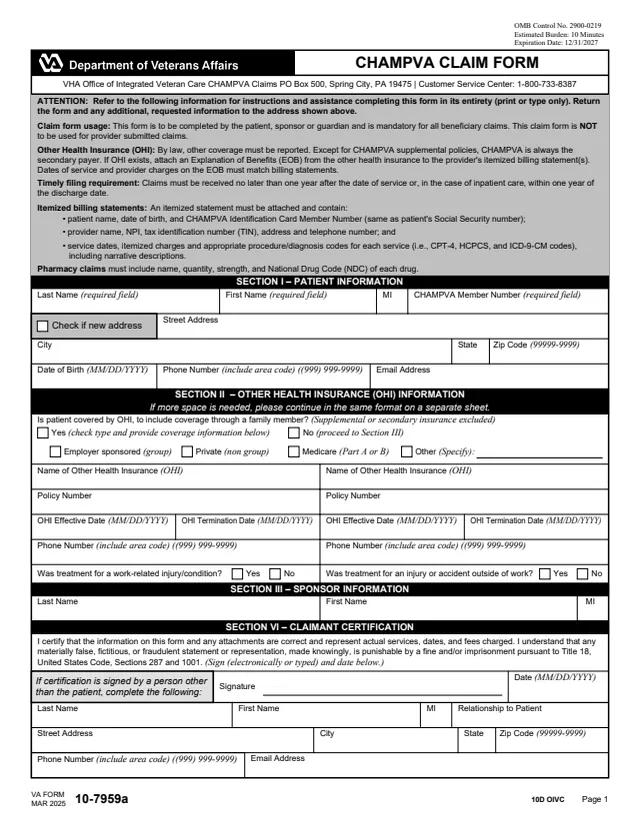
10-7959A
42 fields, 2 pages
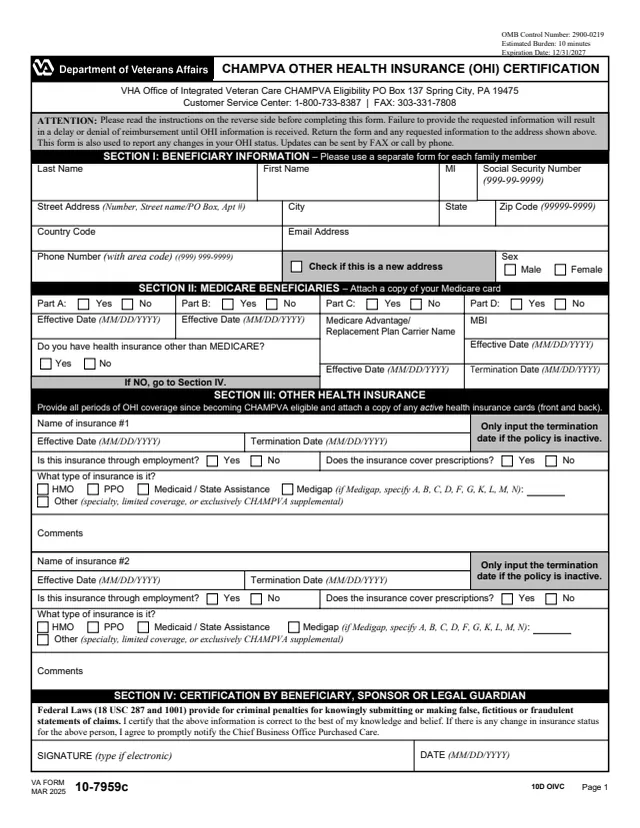
10-7959C
51 fields, 2 pages
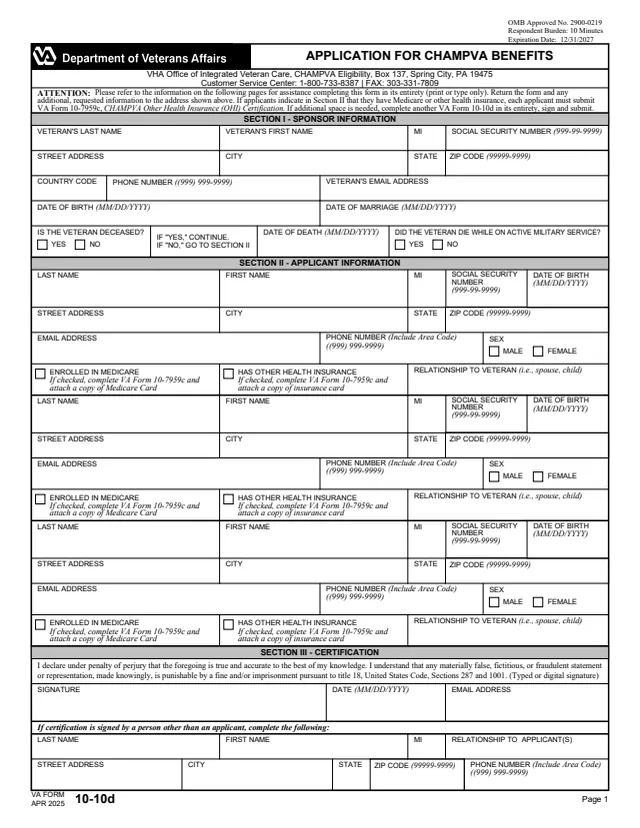
10-10d
73 fields, 3 pages
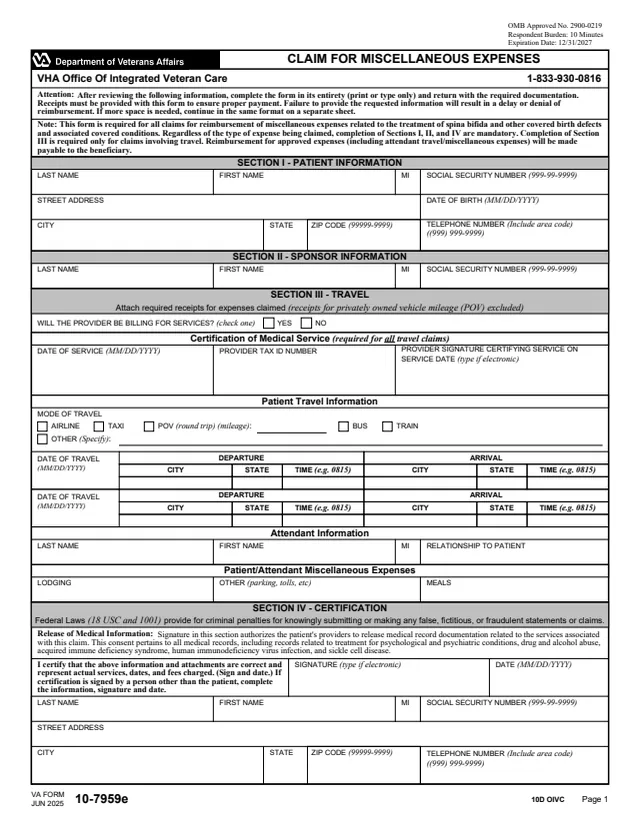
10-7959e
58 fields, 2 pages

10-7959f-2
15 fields, 2 pages
The form is about the patient named in Section I and lists the other people and companies tied to the injury or illness.
No tool matches that search.
The form says it collects information when recent claim information shows medical services for an injury or potential work-related illness, because the Federal Medical Care Recovery Act requires recovery of VA costs when a third party caused or covers the injury or illness.
The Privacy Act notice says disclosure is voluntary, but that leaving out any or all of the information may delay or result in denial of your request for CHAMPVA benefits. The form also asks for it to be completed in its entirety.
Item 28 asks whether the patient is represented by an attorney or contemplating representation. With a yes, Items 29 to 35 ask for the attorney's name, address and phone number.
Yes. Item 36 says that if the form is signed by a person other than the patient, that person completes Items 37 to 44, including their relationship to the patient.
Sections II and III say that if more space is needed, continue in the same format on a separate sheet.
The form's header lists Department of Veterans Affairs, Chief Business Office Purchased Care, CHAMPVA, PO Box 469063, Denver CO 80246-9063.