Privacy Act information
The purpose of the form, its basis in 38 CFR 1.577 and Title 38 U.S.C., and a statement that disclosure is voluntary and that not furnishing the information will not affect any other benefits.
10-5345a
Individuals' Request for a Copy of Their Own Health Information

VA Form 10-5345a is the U.S. Department of Veterans Affairs Individuals' Request for a Copy of Their Own Health Information. The form says its purpose is to give an individual the means to make a written request for a copy of their information maintained by VA, in accordance with 38 CFR 1.577. It is addressed to the Department of Veterans Affairs, with a box for the name and location of the VA health care facility.
The form is one page. It asks for the patient's name, date of birth and mailing address, a checklist of the records wanted, such as a health summary for the prior 2 years, progress notes, lab results, radiology reports or a list of active medications, and how the copy is to be delivered. The patient signs in ink. The form says giving the information is voluntary, but VA will be unable to comply with the request if the information needed to locate the records is not furnished completely and accurately.
You can fill out the PDF free in your browser on this page and download the result without an account.

The purpose of the form, its basis in 38 CFR 1.577 and Title 38 U.S.C., and a statement that disclosure is voluntary and that not furnishing the information will not affect any other benefits.
The name and location of the VA health care facility, the patient's last, first and middle name, date of birth in mm/dd/yyyy and mailing address with city, state and ZIP Code.
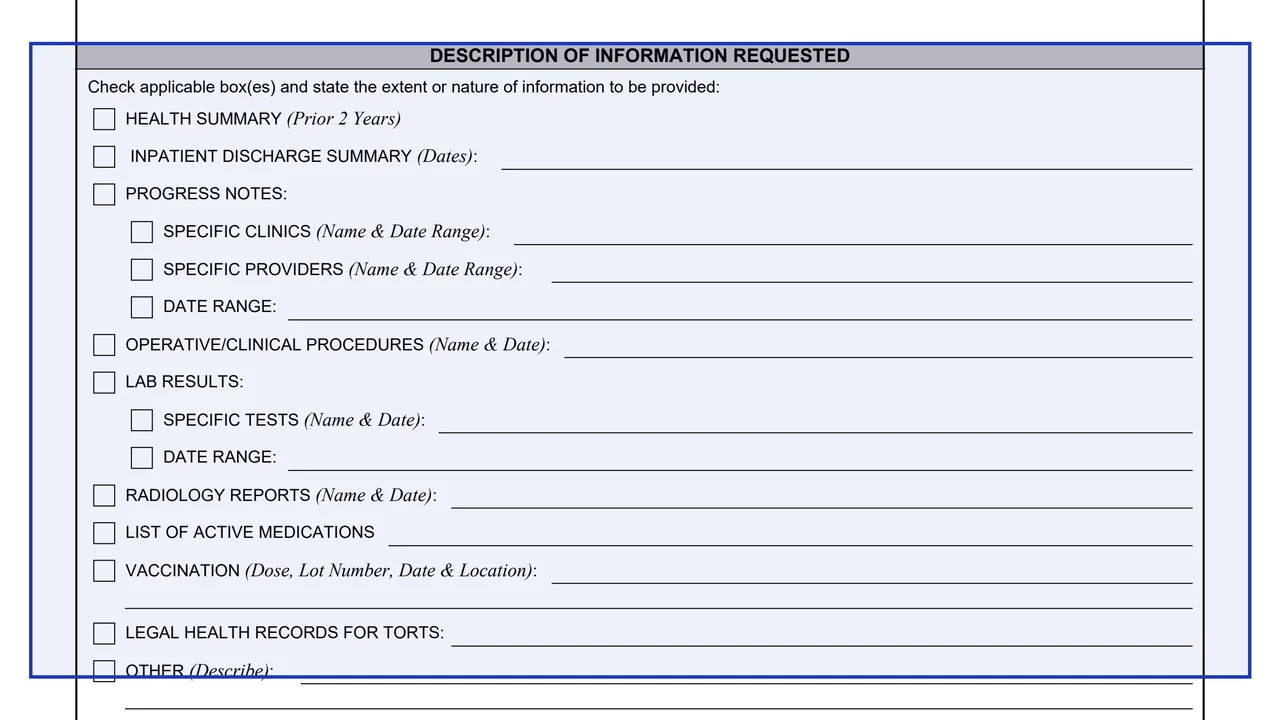
Boxes for a health summary (prior 2 years), inpatient discharge summary, progress notes by clinic, provider or date range, operative or clinical procedures, lab results by test or date range and radiology reports.
A list of active medications, vaccination details (dose, lot number, date and location), legal health records for torts and an Other box to describe anything else.
Paper, CD-ROM or other, in-person pick-up with a contact phone number, or mail to the same address as above or a new address.
The patient signature, which the form says to sign in ink, the date and a note on signing for someone else.
Enter the name and location of the VA health care facility in the TO box.
Give the name, date of birth and mailing address. The form says VA will be unable to comply if the information needed to locate records is not furnished completely and accurately.
The form says to check the applicable boxes and state the extent or nature of the information, such as clinic or provider names, test names and date ranges.
Pick paper, CD-ROM or other, then in-person pick-up with a contact phone number, or mail to the same address or a new one.
Sign and date the form. If someone other than the individual signs, the note asks for the authority, such as guardianship or power of attorney.
These steps follow the form's own labels.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form is addressed to the Department of Veterans Affairs at the VA health care facility named in the TO box. The PDF and VA's form page print no mailing address, fax number or email.
The form cites 38 CFR 1.577 and says the information is requested under Title 38 U.S.C.
The form says disclosure is voluntary and that failure to furnish the information will not have any effect on any other benefits.
The PDF is dated JUL 2021, matching the July 2021 revision date on VA's form page. It prints no OMB number.

10-5345
61 fields, 2 pages

VA3288
11 fields, 2 pages

10-259
15 fields, 1 page

10-0525a
25 fields, 2 pages
10-10163
9 fields, 1 page
The form describes who makes the request and where it goes.
No tool matches that search.
It is the Individuals' Request for a Copy of Their Own Health Information. The form says it gives an individual the means to make a written request for a copy of their information maintained by VA, in accordance with 38 CFR 1.577.
The checklist includes a health summary (prior 2 years), inpatient discharge summary, progress notes, operative or clinical procedures, lab results, radiology reports, a list of active medications, vaccinations, legal health records for torts and an Other box.
The form offers paper, CD-ROM or other, and either in-person pick-up with a contact phone number or mail to the same address as above or a new address.
The form's note says that if it is signed by someone other than the individual, the request indicates the authority under which it is made, for example guardianship or power of attorney.
The form says disclosure is voluntary, but if the information needed to locate records is not furnished completely and accurately, VA will be unable to comply with the request.
It is addressed to the VA health care facility named in the TO box. The PDF and VA's form page print no mailing address.