Items 1 and 2: type and concentration
Boxes for new, revision or refill and for alum precipitate or aqueous, then the final concentration in PNU/ml, WT/VOL or AU/ml. The form says the total vial volume is 10 ml.
SF559
Medical Record - Allergen Extract Prescription - New and Refill
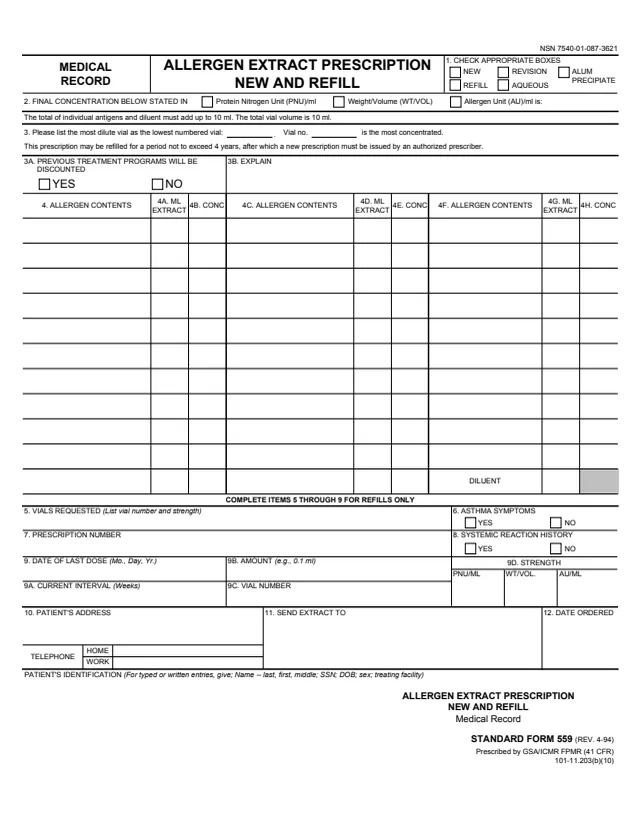
Standard Form 559 (SF 559), Allergen Extract Prescription, New and Refill, is a two-page medical record printed as STANDARD FORM 559 (REV. 4-94). Its footer says Prescribed by GSA/ICMR FPMR (41 CFR) 101-11.203(b)(10), and GSA hosts a copy in its forms library, where it is listed as Medical Record - Allergen Extract Prescription - New and Refill.
The front is the prescription: new, revision or refill, the final concentration, vial numbering, the allergen contents with diluent, refill details in items 5 to 9, the patient's address and where to send the extract. The back prints specific instructions for the clinic giving the injections, the vial schedule in item 13, Schedules A to F, and the ordering physician's signature in item 14.
The form says the prescription may be refilled for a period not to exceed 4 years. You can fill it out free in your browser on this page and download the result without an account.
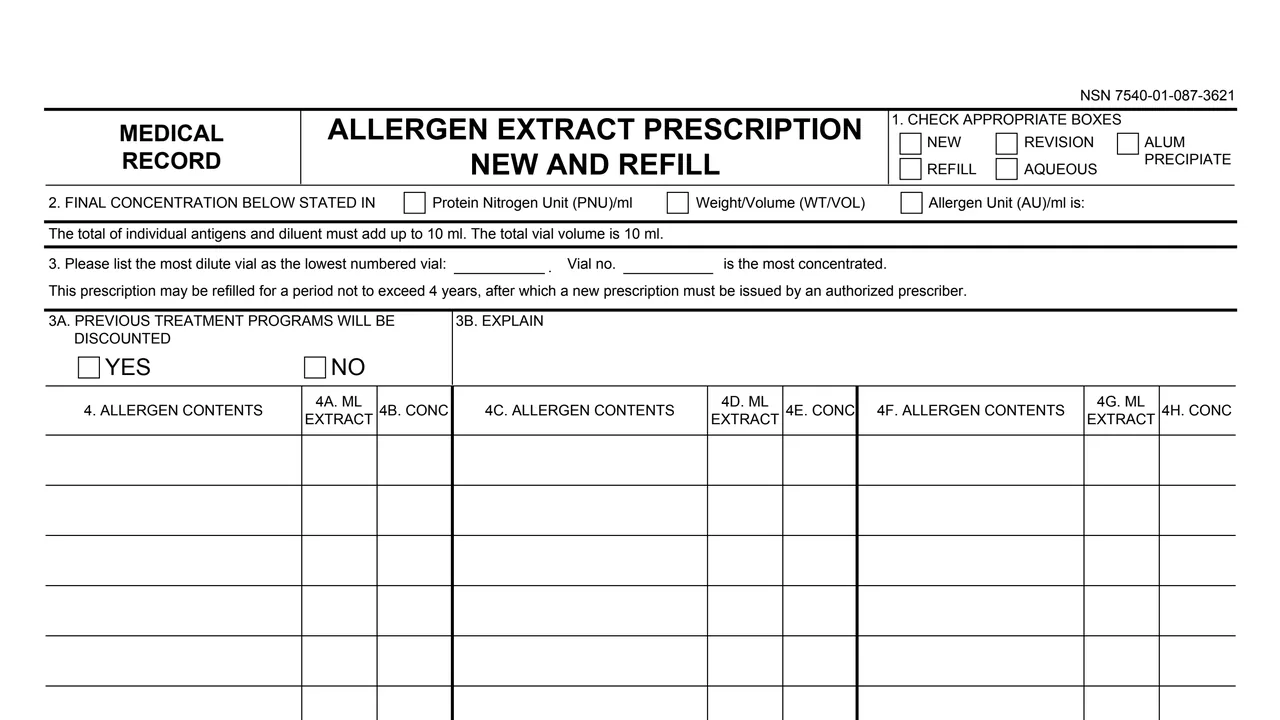
Boxes for new, revision or refill and for alum precipitate or aqueous, then the final concentration in PNU/ml, WT/VOL or AU/ml. The form says the total vial volume is 10 ml.
Which vial is the most dilute and which the most concentrated, item 3A previous treatment programs will be discounted (yes or no) with 3B explain, and three columns of allergen contents with ml extract and concentration, plus diluent.
Vials requested, asthma symptoms, prescription number, systemic reaction history, and the date, current interval, amount, vial number and strength of the last dose.
The patient's address with home and work telephone, where to send the extract, and the date ordered.
Vial number, content in PNU/ml, WT/VOL or AU/ml, days between shots and schedule, and a maintenance interval in 13D. The back prints Schedules A to E and Schedule F (Custom Schedule).
Signature, rank and degree of the ordering physician, the name of the medical facility and its telephone number, with an area for a custom extract label or remarks.
The front holds items 1 to 12 and the back holds the instructions and items 13 and 14.
For typed or written entries, the form asks for the name (last, first, middle), SSN, DOB, sex and treating facility.
In item 1, check new, revision or refill, and alum precipitate or aqueous.
Complete items 2 to 4. The form says the total of individual antigens and diluent must add up to 10 ml, and asks to list the most dilute vial as the lowest numbered vial.
For a refill, fill in items 5 to 9: vials requested, asthma symptoms, prescription number, systemic reaction history and details of the last dose.
Enter the patient's address and telephones in item 10, where to send the extract in item 11 and the date ordered in item 12.
On the back, complete the item 13 schedule for each vial, then item 14 with the physician's signature, rank and degree, the medical facility and its telephone number.
The form numbers its items in order. It says items 5 through 9 are for refills only.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The PDF prints no filing address. It is labeled Medical Record. Item 11 names where to send the extract and item 14A names the medical facility.
The form says the prescription may be refilled for a period not to exceed 4 years, after which a new prescription must be issued by an authorized prescriber.
The SPECIFIC INSTRUCTIONS say a physician must always be immediately available in the clinic area, all patients must remain in the clinic at least 30 minutes after an injection, and the date, dosage and any reaction are recorded on a separate immunotherapy form.
The footer says Prescribed by GSA/ICMR FPMR (41 CFR) 101-11.203(b)(10). The form also prints NSN 7540-01-087-3621.
The form names the ordering physician as the signer and addresses its specific instructions to the clinic giving the injections.
No tool matches that search.
The footer says Prescribed by GSA/ICMR FPMR (41 CFR) 101-11.203(b)(10). GSA hosts a copy in its forms library, printed as STANDARD FORM 559 (REV. 4-94).
The form says the prescription must be signed by the ordering physician. Item 14 asks for the signature, rank and degree, with the medical facility and its telephone number in 14A and 14B.
The form says to complete items 5 through 9 for refills only. They cover vials requested, asthma symptoms, prescription number, systemic reaction history and the last dose.
The form says it may be refilled for a period not to exceed 4 years, after which a new prescription must be issued by an authorized prescriber.
The back prints dose columns for Schedules A to E and a Schedule F (Custom Schedule). The item 13 table has a schedule column for each vial.
Yes. The back prints SPECIFIC INSTRUCTIONS on reactions, missed injections and refill vials, and in several cases says to contact the medical facility named on the form.




