Blocks 1 to 11: Facility and survey
Facility name, street address, city or county, state, ZIP code, Medicaid provider number, CEO, phone, State/Region and State/County codes, and survey begin and end dates (mm/dd/yyyy).
CMS-3070G
ICF/IID Survey Report
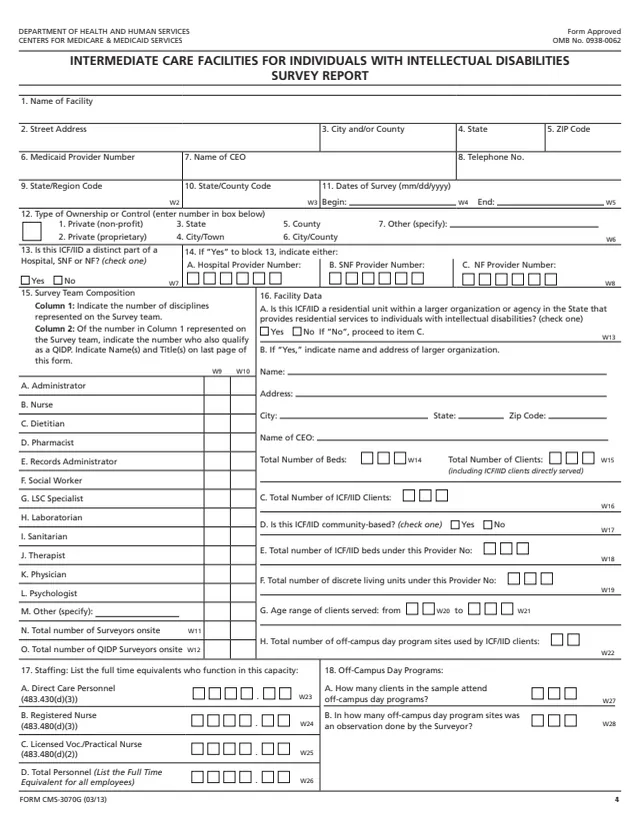
Form CMS-3070G is the Intermediate Care Facilities for Individuals with Intellectual Disabilities (ICF/IID) Survey Report from the Centers for Medicare & Medicaid Services. It records one survey of an ICF/IID: the facility's identity and ownership, who was on the survey team, facility and staffing data, off-campus day programs, and counts of client characteristics.
Most entries carry a code from W2 to W74. The last section counts allegations of abuse and neglect investigated and deaths, and comes with data entry instructions that quote the definitions of abuse and neglect in 42 CFR 488.301. The form carries OMB No. 0938-0062 and estimates an average of 3 hours per response.
You can fill it out free in your browser on this page and download the result without an account.
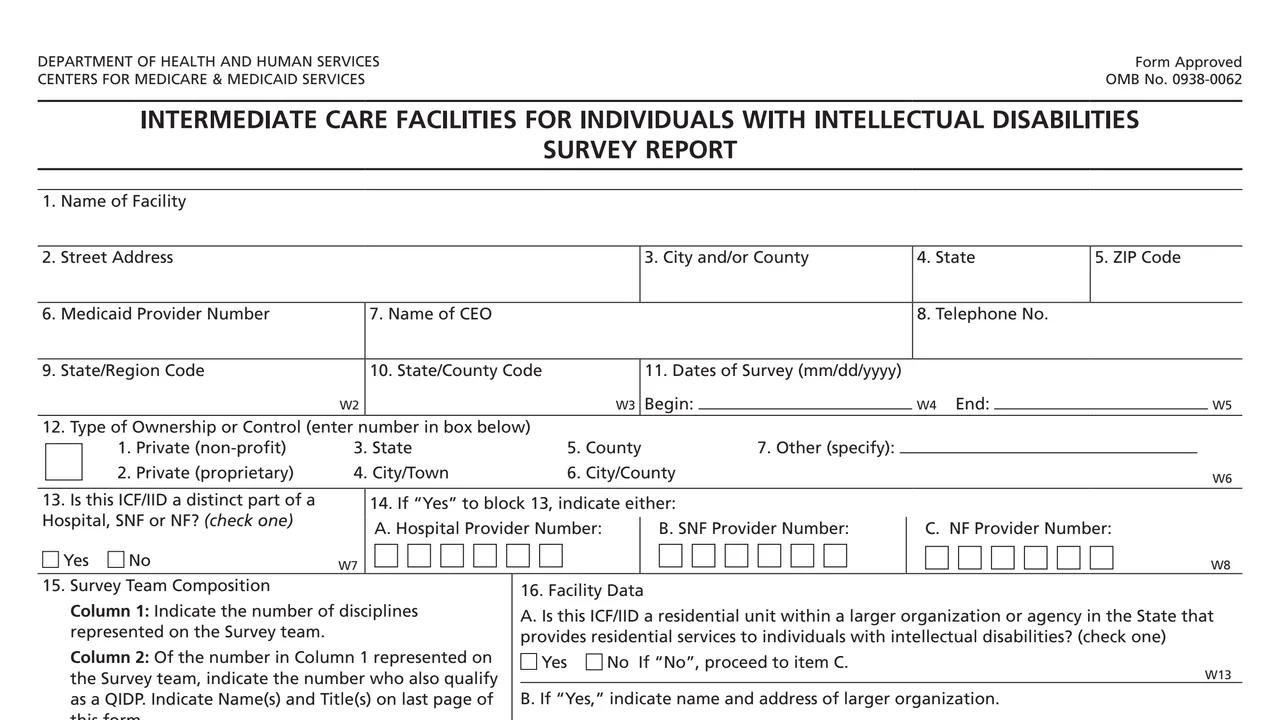
Facility name, street address, city or county, state, ZIP code, Medicaid provider number, CEO, phone, State/Region and State/County codes, and survey begin and end dates (mm/dd/yyyy).
Type of ownership or control from seven numbered choices, and whether the ICF/IID is a distinct part of a hospital, SNF or NF, with its provider number.
The number of surveyors from each discipline, from administrator to psychologist and other, and the totals of surveyors and QIDP surveyors onsite.
Beds, clients, whether the ICF/IID is community-based, living units, client age range and off-campus day program sites; full time equivalents for direct care personnel and nurses; and day program attendance and observations.
Counts of clients by age and sex, level of intellectual disability, autism, cerebral palsy, epilepsy, other disabilities, drugs to control behavior, physical restraints, time-out rooms, court-ordered admissions and more.
The number of allegations of abuse and of neglect investigated, and the number of deaths related to unusual incidents, to restraints, and for any other reason.
Fill in blocks 1 to 11, including the survey begin and end dates in mm/dd/yyyy format.
Enter the ownership number in block 12 and answer blocks 13 and 14.
Count each discipline in block 15, column 1, and those who also qualify as a QIDP in column 2. The form asks for names and titles on its last page.
Complete blocks 16 to 18. If the answer to 16A is No, the form says to go to item C.
Complete block 19 A to L. The form notes the totals in items B to L may exceed the facility's population because some clients have multiple disabilities.
Follow the data entry instructions for sections M and N. If there is nothing to report, they say to leave the field blank. Totals W70 and W74 are program generated.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form does not print a submission address. The CMS address in its Paperwork Reduction Act statement is for comments on the time estimate only.
The data entry instructions say to count allegations of abuse or neglect investigated, including investigations resulting from complaints, follow ups, initials or recertifications.
W71 counts unexpected or unanticipated deaths from unusual incidents, W72 deaths from the use of restraints, and W73 deaths for any reason not included in W71 and W72.
The form estimates an average of 3 hours per response, including reviewing instructions, gathering the data and completing the form.
The form does not name who fills it out. Its blocks describe the facility surveyed and the survey team.
No tool matches that search.
The form's title spells it out: Intermediate Care Facilities for Individuals with Intellectual Disabilities.
The form labels its entries with codes from W2 to W74, and its data entry instructions refer to fields by those codes.
Quoting 42 CFR 488.301, it defines abuse as the willful infliction of injury, unreasonable confinement, intimidation or punishment with resulting physical harm, pain or mental anguish, and neglect as the failure to provide goods and services necessary to avoid physical harm, mental anguish or mental illness.
No. The data entry instructions say those totals are program generated, so no data input is necessary.
The form notes that the totals in items B to L may exceed the facility's population because some clients have multiple disabilities.
The form estimates an average of 3 hours per response.