Section 1: General information
Station number and VISN, both marked required, the month and year, the report quarter, To (the VA Medical Center of jurisdiction), From (level of care and State Home) and Pay To.
10-5588
State Home Report and Statement of Federal Aid Claimed
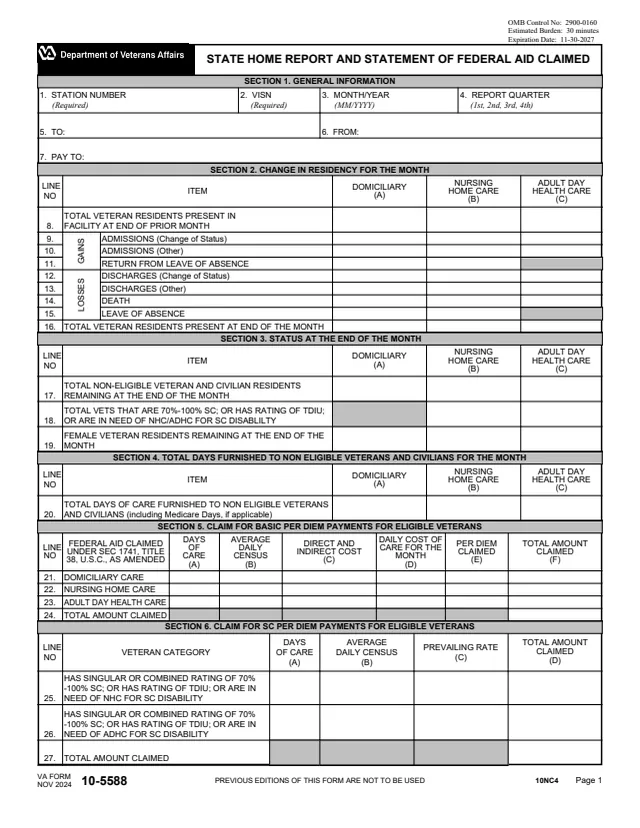
VA Form 10-5588 is the U.S. Department of Veterans Affairs State Home Report and Statement of Federal Aid Claimed. Its instructions describe it as a monthly statement of gains and losses, days of care, average daily census, allowable cost, total per diem cost, per diem claimed and total amount claimed for nursing home, domiciliary and adult day health care. They say monthly payments will be made to the State Home only after the State submits a completed VA Form 10-5588 and required supporting documentation.
The PDF has five pages: the report on pages 1 and 2, then three pages of instructions. Section 8 is the certification by the State Veterans Home (SVH) administrator, or a State employee when a contractor runs the facility, and Section 9 is a receiving report marked for VA use only. The form asks for facility counts and costs, not an individual Veteran's details. You can fill out the PDF free in your browser on this page and download the result without an account.
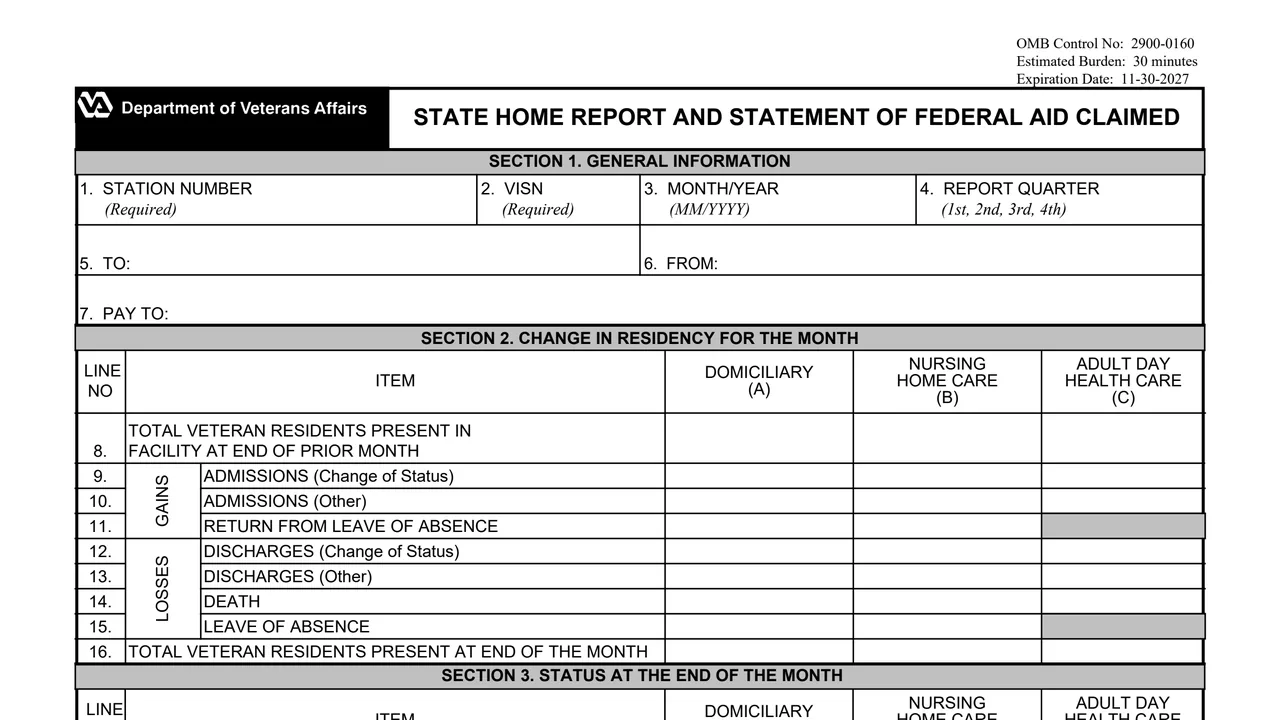
Station number and VISN, both marked required, the month and year, the report quarter, To (the VA Medical Center of jurisdiction), From (level of care and State Home) and Pay To.
Residents at the end of the prior month, admissions, returns from leave, discharges, deaths, leave of absence and residents at the end of the month, then non-eligible residents, Veterans who are 70% to 100% SC, TDIU or need care for an SC disability, and female Veteran residents.
Total days of care furnished to non-eligible Veterans and civilians, including Medicare days if applicable, for each level of care.
Basic per diem by level of care: days of care, average daily census, direct and indirect cost, daily cost of care, per diem claimed and total. Then SC per diem at the VA prevailing rate for the 70% to 100% SC, TDIU or SC need categories.
Recognized beds approved by VA for DOM, NHC and ADHC, then the certification signed by the SVH Administrator or, when applicable, a State employee, and remarks.
For VA use only: the total amount approved for payment, the VA approving official, obligation numbers and amounts due by level of payment, and the auditor.
Enter the station number and VISN of the VA Medical Center of jurisdiction, the month and year, and the fiscal quarter: 1 for October to December, 2 for January to March, 3 for April to June, 4 for July to September.
Line 8 matches line 16 of the prior month. Line 16 equals the sum of lines 8, 9, 10 and 11 minus lines 12, 13, 14 and 15 in each column.
Divide the month's direct and indirect cost in column C by all residents' days of care for that level of care, computed under the cost principles in 2 CFR 200.400 to 200.475.
Column E is the current fiscal year per diem rate or one-half the daily cost of care, whichever is the lesser. In Section 6, multiply the days of care by the VA prevailing rate published by the SHPDP Office.
Enter the beds approved by VA during the latest recognition survey in blocks 28 to 30. The SVH Administrator, or a State employee at a contractor-run home, prints a name and title, signs and dates.
The VA approving official and auditor complete the receiving report. The form notes that if it is not completed in its entirety, it could result in an improper payment.
These steps follow the form's own instructions.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The PDF and VA's form page print no mailing address, fax number or email. Item 5 is addressed To the VA Medical Center of jurisdiction, not the Health Care System.
The notice says completion is voluntary, but VA will be unable to provide reimbursement for services rendered without a completed form.
The form cites Title 38 CFR Parts 51 and Title 38, U.S.C., Sections 1741, 1742, 1743 and 1745.
The PDF is dated NOV 2024 and says previous editions are not to be used. It carries OMB Control No: 2900-0160, Expiration Date: 11-30-2027, with an estimated burden of 30 minutes.
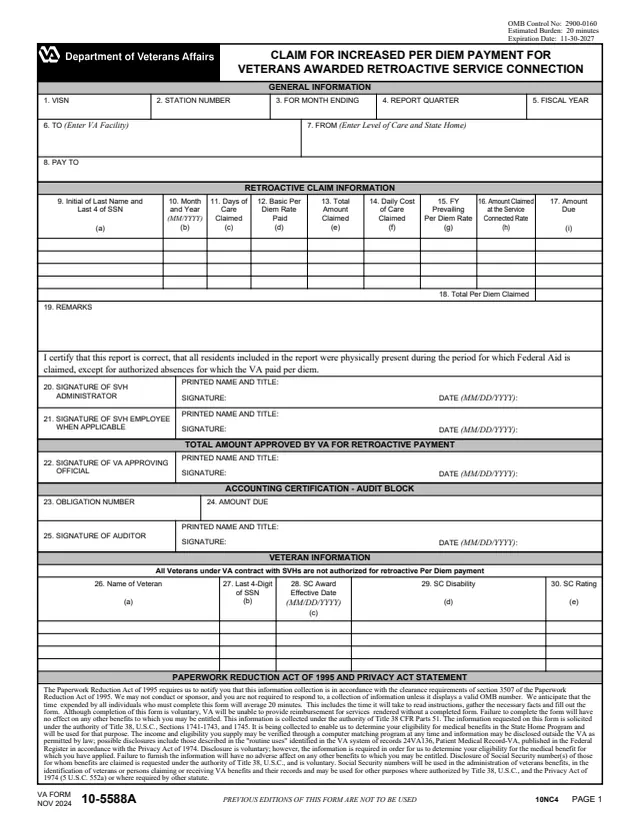
10-5588A
80 fields, 2 pages

10-3567
370 fields, 4 pages
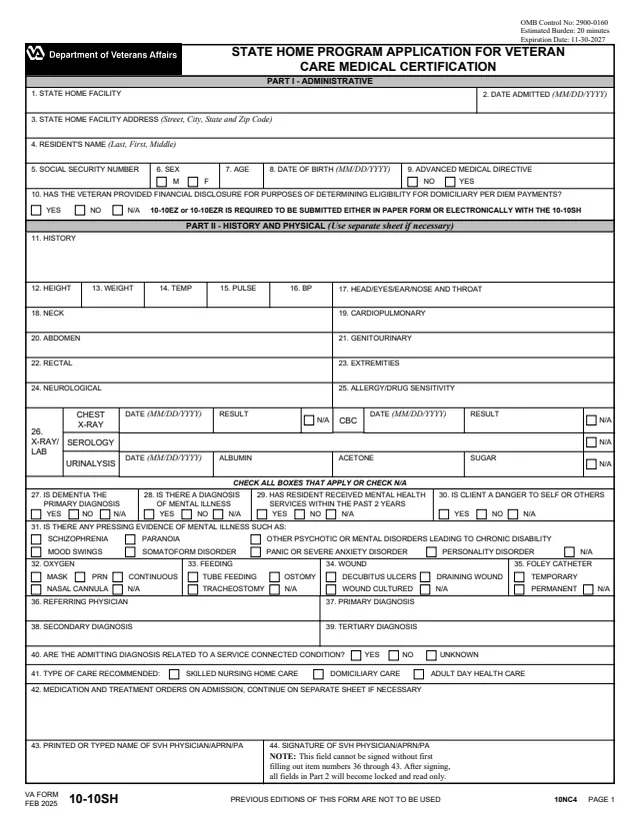
10-10SH
159 fields, 6 pages
10-0460
76 fields, 3 pages
10-0430
23 fields, 2 pages
The form is a claim from a State Home to VA, with a final section for VA staff.
No tool matches that search.
It is the State Home Report and Statement of Federal Aid Claimed, a monthly statement of residents, days of care, costs and per diem claimed for nursing home, domiciliary and adult day health care.
The SVH Administrator signs Item 31. When an entity contracting with the State runs the facility, a State employee signs Item 32 instead. A VA approving official and an auditor sign Section 9.
The instructions say column E is the current fiscal year per diem rate or one-half the daily cost of care, whichever is the lesser, and column F is the product of columns A and E.
For domiciliary and nursing home care, an overnight stay by an eligible Veteran. For adult day health care, at least six hours in one calendar day or any two periods of at least 3 hours each in any two calendar days in a calendar month. The day of discharge is not counted.
The instructions say to enter 1 for October to December, 2 for January to March, 3 for April to June and 4 for July to September.
No. The NOV 2024 edition says previous editions of this form are not to be used.