Burden and Privacy Act information
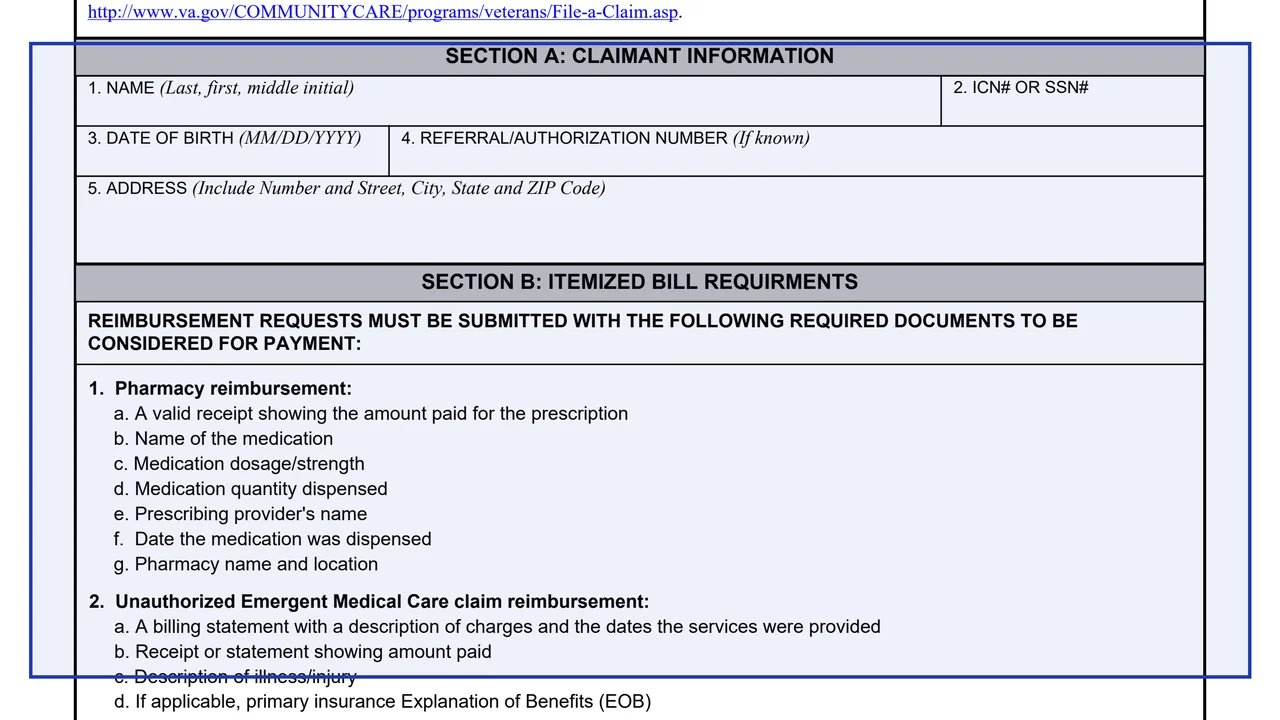
OMB Control No. 2900-0940, an estimated burden of 10 minutes, and a Privacy Act notice saying the information is used to help determine entitlement to reimbursement for services rendered.
10-320
Veteran Reimbursement Claim Form
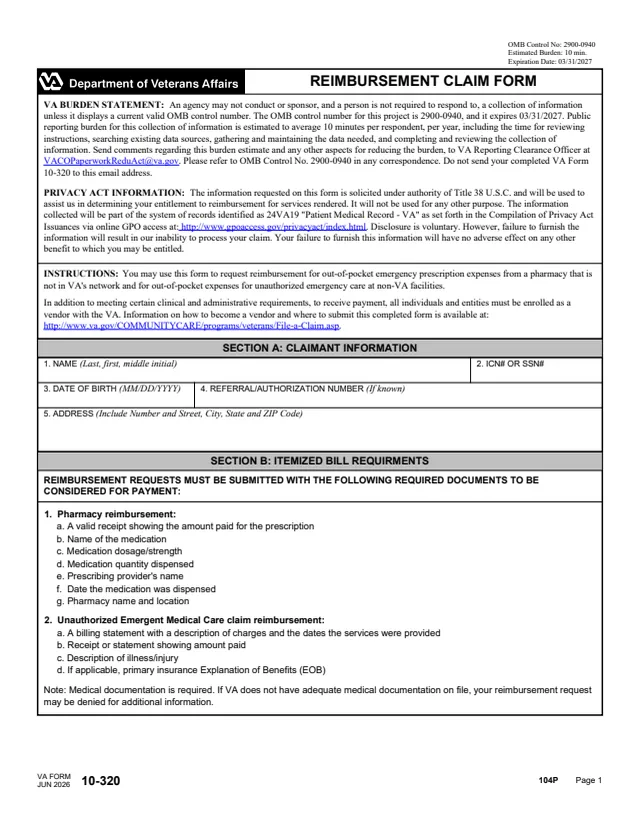
VA Form 10-320 is the U.S. Department of Veterans Affairs Veteran Reimbursement Claim Form, listed under health care on VA's page. VA's page says to use it to request reimbursement for out-of-pocket emergency prescription expenses from a pharmacy that's not in VA's network, and out-of-pocket expenses for unauthorized emergency care at non-VA facilities.
The form says that, in addition to meeting certain clinical and administrative requirements, to receive payment all individuals and entities must be enrolled as a vendor with the VA. It says information on how to become a vendor and where to submit the completed form is available at http://www.va.gov/COMMUNITYCARE/programs/veterans/File-a-Claim.asp.
The form is two pages: Section A for claimant information, Section B for the itemized bill requirements and Section C for a signed written explanation of why services were not obtained through VA. You can fill out the PDF free in your browser on this page and download the result without an account.

OMB Control No. 2900-0940, an estimated burden of 10 minutes, and a Privacy Act notice saying the information is used to help determine entitlement to reimbursement for services rendered.
Name, ICN or SSN, date of birth, a referral or authorization number if known, and address.
A valid receipt showing the amount paid for the prescription, the medication name, dosage or strength, quantity dispensed, prescribing provider's name, date dispensed, and pharmacy name and location.
A billing statement with a description of charges and the dates of service, a receipt or statement of the amount paid, a description of the illness or injury and, if applicable, the primary insurance Explanation of Benefits (EOB).
A written explanation of why services were not obtained through VA, a signature declaring under penalty of perjury that the information is true and accurate, and the date.
The instructions point to VA's community care File a Claim page for how to become a vendor and where to submit the completed form.
Enter the claimant's name, ICN or SSN, date of birth, address and any known referral or authorization number.
Section B says reimbursement requests are submitted with the listed documents to be considered for payment. Its note says medical documentation is required.
Write why services were not obtained through VA, then sign and date the declaration.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form prints no mailing address. It says where to submit the completed form is available at http://www.va.gov/COMMUNITYCARE/programs/veterans/File-a-Claim.asp.
The burden statement gives [email protected] for comments on the burden estimate and says do not send your completed VA Form 10-320 to this email address.
The form says that if VA does not have adequate medical documentation on file, the reimbursement request may be denied for additional information.
JUN 2026, matching the June 2026 revision date on VA's form page. OMB Control No. 2900-0940 expires 03/31/2027.

10-10143g
31 fields, 1 page
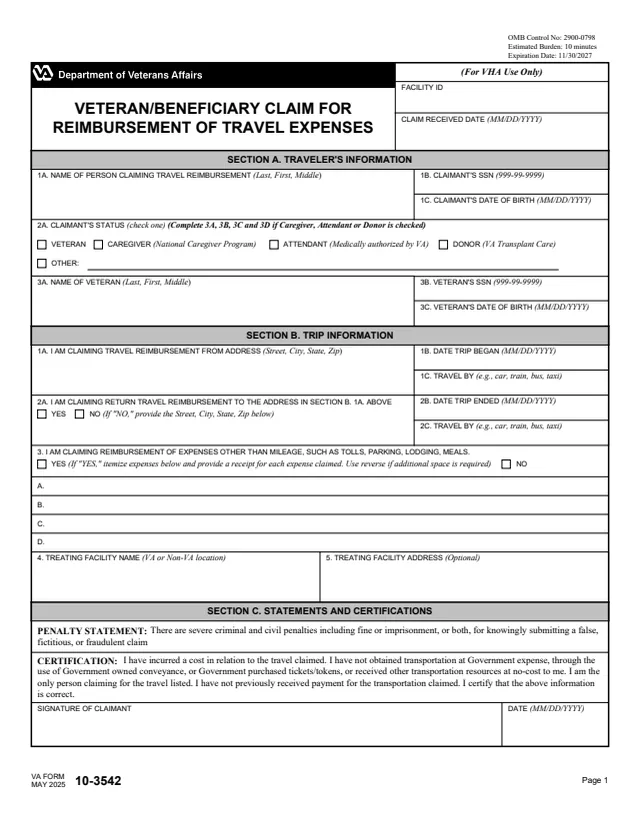
10-3542
26 fields, 2 pages

10-10EZ
122 fields, 6 pages

10-5345
61 fields, 2 pages
VA's page and the form describe these uses.
No tool matches that search.
VA's page says it is for out-of-pocket emergency prescription expenses from a pharmacy that's not in VA's network and out-of-pocket expenses for unauthorized emergency care at non-VA facilities.
Section B lists a valid receipt showing the amount paid, plus the medication name, dosage or strength, quantity dispensed, prescribing provider's name, date dispensed, and pharmacy name and location.
A billing statement describing the charges and the dates of service, a receipt or statement showing the amount paid, a description of the illness or injury and, if applicable, the primary insurance Explanation of Benefits.
The form says that to receive payment, all individuals and entities must be enrolled as a vendor with the VA, and points to VA's community care File a Claim page for how to become one.
Section C asks for a signed written explanation of why services were not obtained through the VA.
The form does not print an address. It says where to submit it is available at http://www.va.gov/COMMUNITYCARE/programs/veterans/File-a-Claim.asp.