Items 1 to 3: VA station
Name of the VA station, its address and telephone number.
10-2410
Agreement to Provide Home Care for Patient
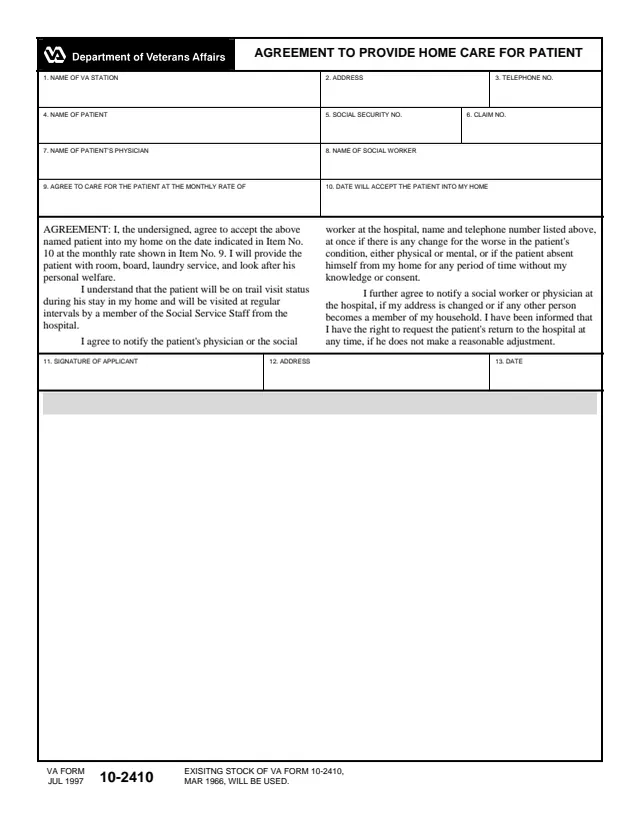
VA Form 10-2410 is the U.S. Department of Veterans Affairs Agreement to Provide Home Care for Patient. VA's form page lists it under VHA. The person signing agrees to accept the named patient into their home on the date in Item 10 at the monthly rate in Item 9, and to provide room, board, laundry service and look after the patient's personal welfare.
The form says the patient will be on visit status from the hospital during the stay and will be visited at regular intervals by a member of the hospital's Social Service Staff. The person providing the home agrees to tell the hospital about changes in the patient's condition, absences, a change of address or a new member of the household. The form says they have the right to request the patient's return to the hospital at any time if the patient does not make a reasonable adjustment.
The form is one page with 13 items. It does not print a rate. You can fill out the PDF free in your browser on this page and download the result without an account.
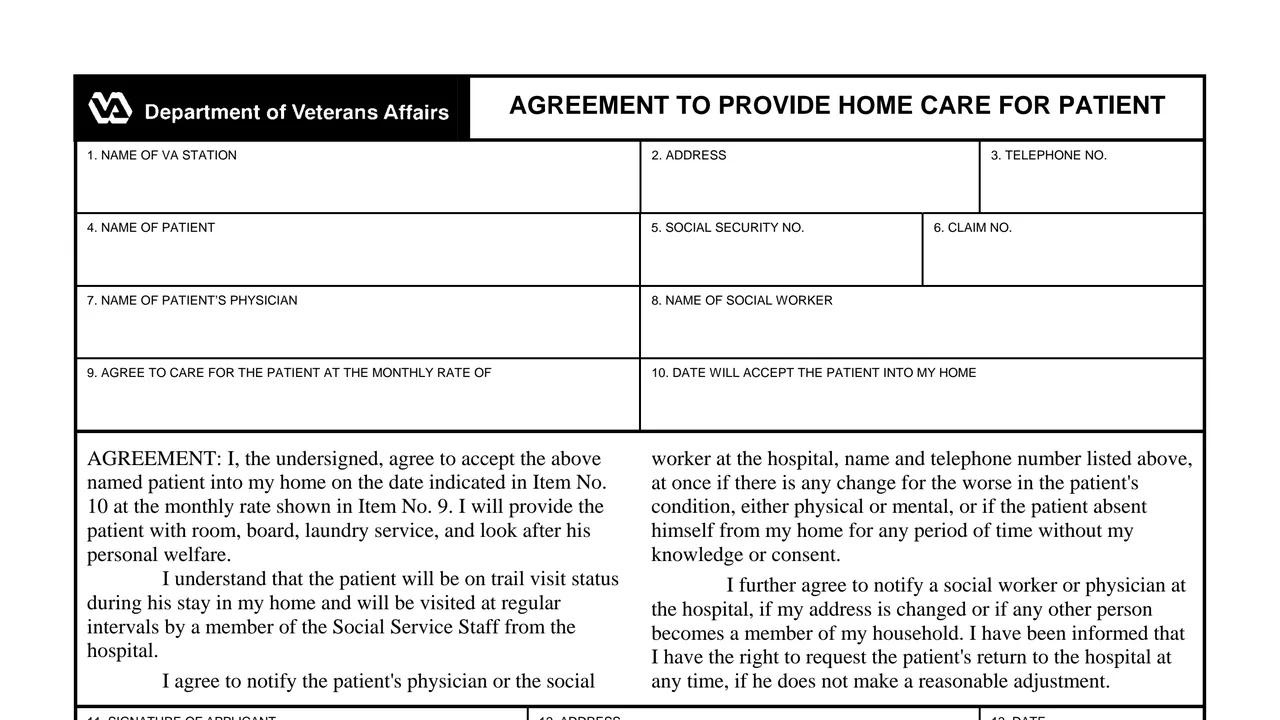
Name of the VA station, its address and telephone number.
The patient's name, Social Security number and claim number, and the names of the patient's physician and social worker.
The monthly rate at which the applicant agrees to care for the patient, and the date the applicant will accept the patient into the home.
Room, board, laundry service and looking after the patient's personal welfare, regular visits by Social Service Staff, and the duties to notify the hospital of changes.
Signature of the applicant, the applicant's address and the date.
Fill in Items 1 to 3 with the VA station's name, address and telephone number.
Enter the patient's name, Social Security number and claim number in Items 4 to 6.
Enter the patient's physician in Item 7 and the social worker in Item 8.
Item 9 holds the monthly rate and Item 10 the date the patient will be accepted into the home. The form leaves both blank.
Sign Item 11, give the address in Item 12 and date Item 13.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form and VA's page do not print a mailing address. Items 1 to 3 name the VA station, and Item 8 names the social worker.
The applicant agrees to notify a social worker or physician at the hospital if the applicant's address is changed or if any other person becomes a member of the household.
The form says the applicant has the right to request the patient's return to the hospital at any time if the patient does not make a reasonable adjustment.
The PDF is dated JUL 1997 and says existing stock of VA Form 10-2410, MAR 1966, will be used.
The form names the person providing the home and the people it reports to.
No tool matches that search.
An agreement in which a person agrees to accept a named patient into their home at a monthly rate and to provide room, board, laundry service and look after the patient's personal welfare.
The applicant, the person agreeing to provide the home, signs Item 11. The form has no signature line for the patient, physician or social worker.
No. Item 9 is a blank field for the monthly rate. The form prints no amount.
Any change for the worse in the patient's physical or mental condition, any absence from the home without the applicant's knowledge or consent, a change of the applicant's address, and any other person becoming a member of the household.
The form says the applicant has the right to request the patient's return to the hospital at any time if the patient does not make a reasonable adjustment.