Instructions block
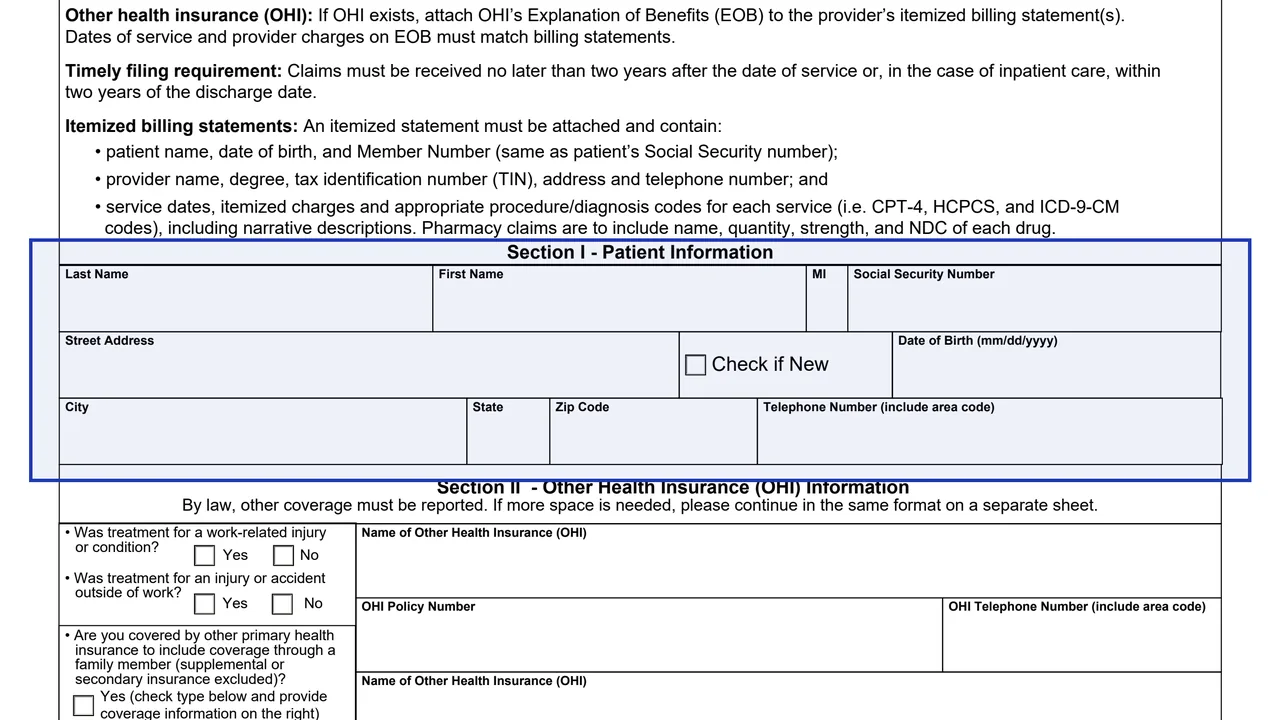
Where to return the form, who completes it, how to attach an other health insurance Explanation of Benefits, the timely filing requirement and what an itemized billing statement contains.
10-10068a
Camp Lejeune Family Member Program Claim Form
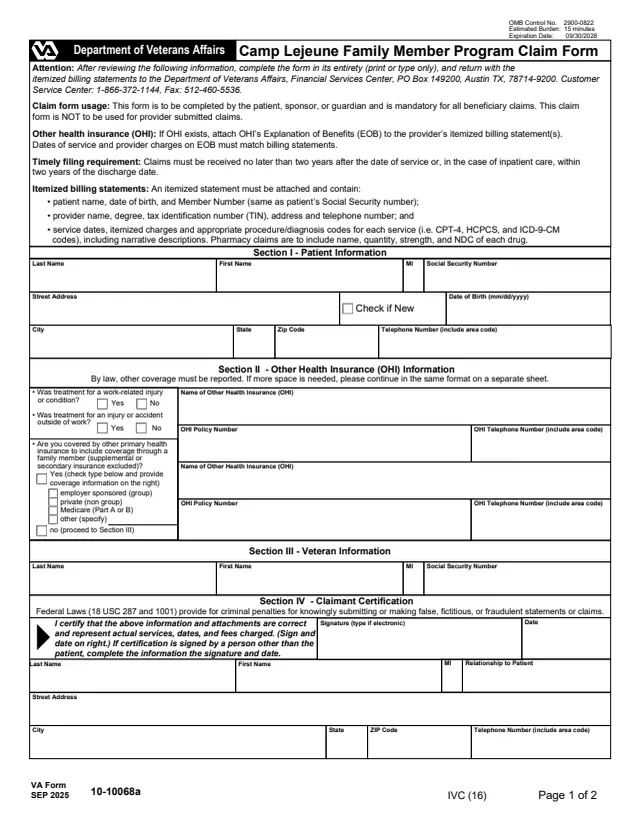
VA Form 10-10068a is the U.S. Department of Veterans Affairs Camp Lejeune Family Member Program Claim Form. VA's form page says to use it to file a claim through the Camp Lejeune Family Member Program. The form says it is completed by the patient, sponsor or guardian, is mandatory for all beneficiary claims, and is not to be used for provider submitted claims.
The claim goes to VA's Financial Services Center with itemized billing statements attached. The top of page 1 explains other health insurance, the timely filing requirement and what an itemized statement contains. Sections I to IV ask for patient information, other health insurance, Veteran information and a certification. Page 2 holds the burden and Privacy Act notices.
You can fill out the PDF free in your browser on this page and download the result without an account.
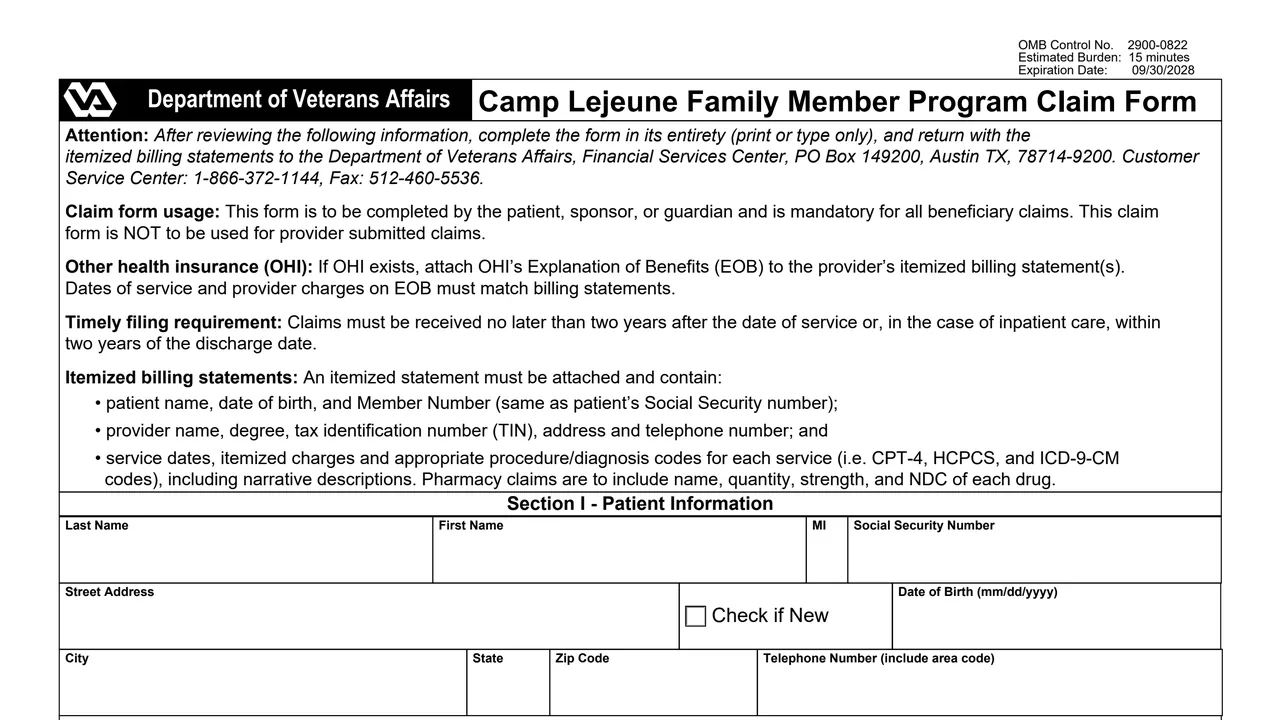
Where to return the form, who completes it, how to attach an other health insurance Explanation of Benefits, the timely filing requirement and what an itemized billing statement contains.
Patient name, Social Security number, street address with a Check if New box, date of birth, city, state, ZIP code and phone number.
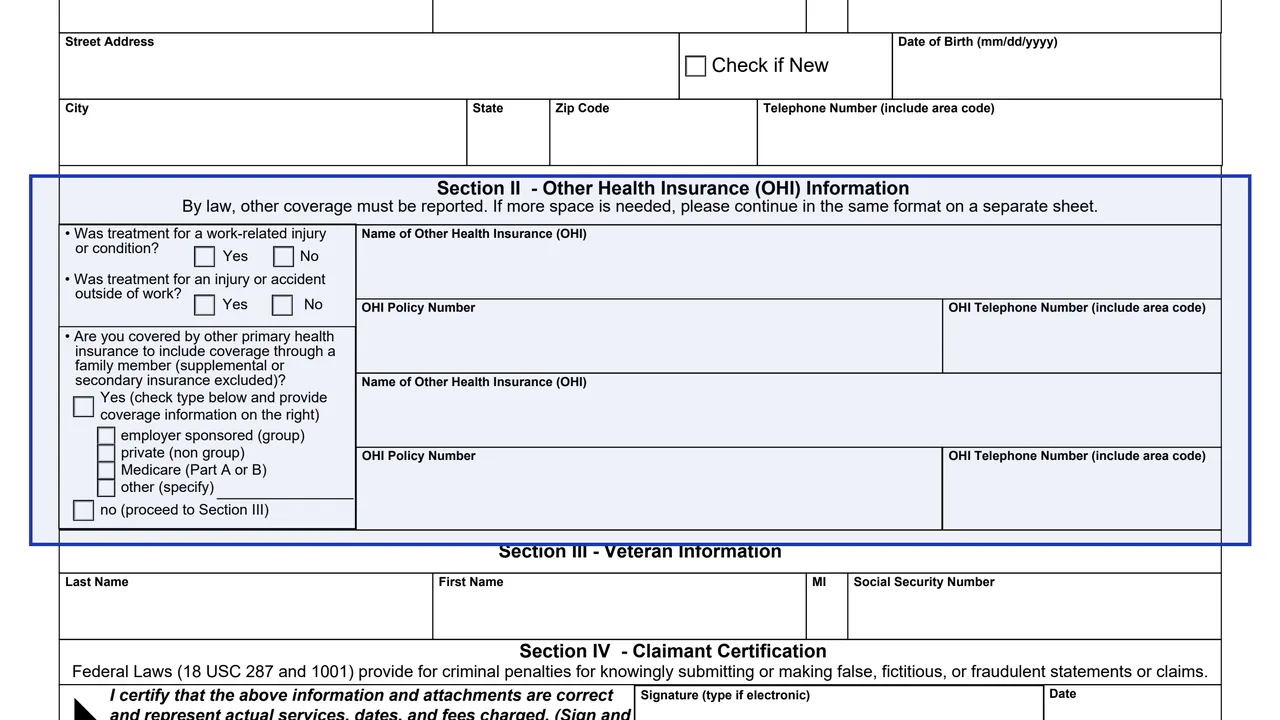
Whether treatment was for a work-related injury or an accident outside work, whether other primary health insurance covers you, its type, and each insurer's name, policy number and phone.
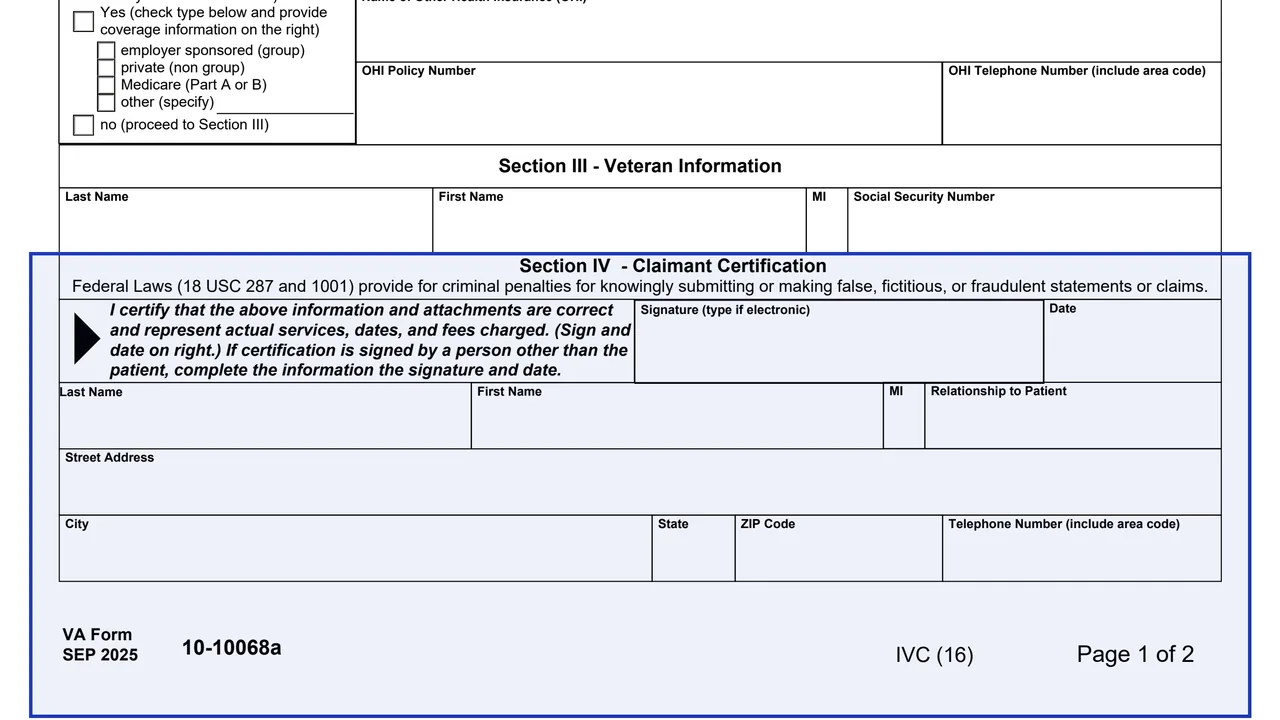
The Veteran's last name, first name, middle initial and Social Security number.
A certification that the information and attachments are correct and represent actual services, dates and fees charged, a signature (typed if electronic) and date, and details of anyone signing for the patient.
The form says to review the information at the top, then complete the form in its entirety, print or type only.
Each statement shows patient name, date of birth and Member Number, the provider's name, degree, TIN, address and phone, and service dates, itemized charges and procedure and diagnosis codes with descriptions.
If other health insurance exists, attach its Explanation of Benefits to the provider's itemized billing statements. The form says dates of service and charges on the EOB and the billing statements match.
Enter the patient's details, the other health insurance answers and the Veteran's name and Social Security number. Use a separate sheet in the same format if more space is needed for insurance.
Sign and date Section IV. A person other than the patient also enters their name, relationship to the patient, address and phone.
Send the form with the itemized billing statements to the Financial Services Center in Austin, Texas, within the timely filing requirement the form prints.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
Department of Veterans Affairs, Financial Services Center, PO Box 149200, Austin TX, 78714-9200.
The form says claims must be received no later than two years after the date of service or, in the case of inpatient care, within two years of the discharge date.
The form lists 1-866-372-1144 and fax 512-460-5536.
The form says pharmacy claims include the name, quantity, strength and NDC of each drug.
The edition is dated SEP 2025. The form carries OMB Control No. 2900-0822, which expires 09/30/2028, and an estimated burden of 15 minutes.
10-10068
84 fields, 3 pages

10-10068b
53 fields, 2 pages
10-10068c
60 fields, 2 pages
10-7959A
42 fields, 2 pages
10-7959C
51 fields, 2 pages
10-10d
73 fields, 3 pages
The form's claim form usage note says who completes it.
No tool matches that search.
VA's form page says to use it to file a claim through the Camp Lejeune Family Member Program.
The form says it is completed by the patient, sponsor or guardian and is mandatory for all beneficiary claims.
No. The form says it is NOT to be used for provider submitted claims.
The form says claims must be received no later than two years after the date of service or, in the case of inpatient care, within two years of the discharge date.
Itemized billing statements with the patient, provider and service details the form lists, plus the other health insurance Explanation of Benefits if other coverage exists.
The form lists Department of Veterans Affairs, Financial Services Center, PO Box 149200, Austin TX, 78714-9200.