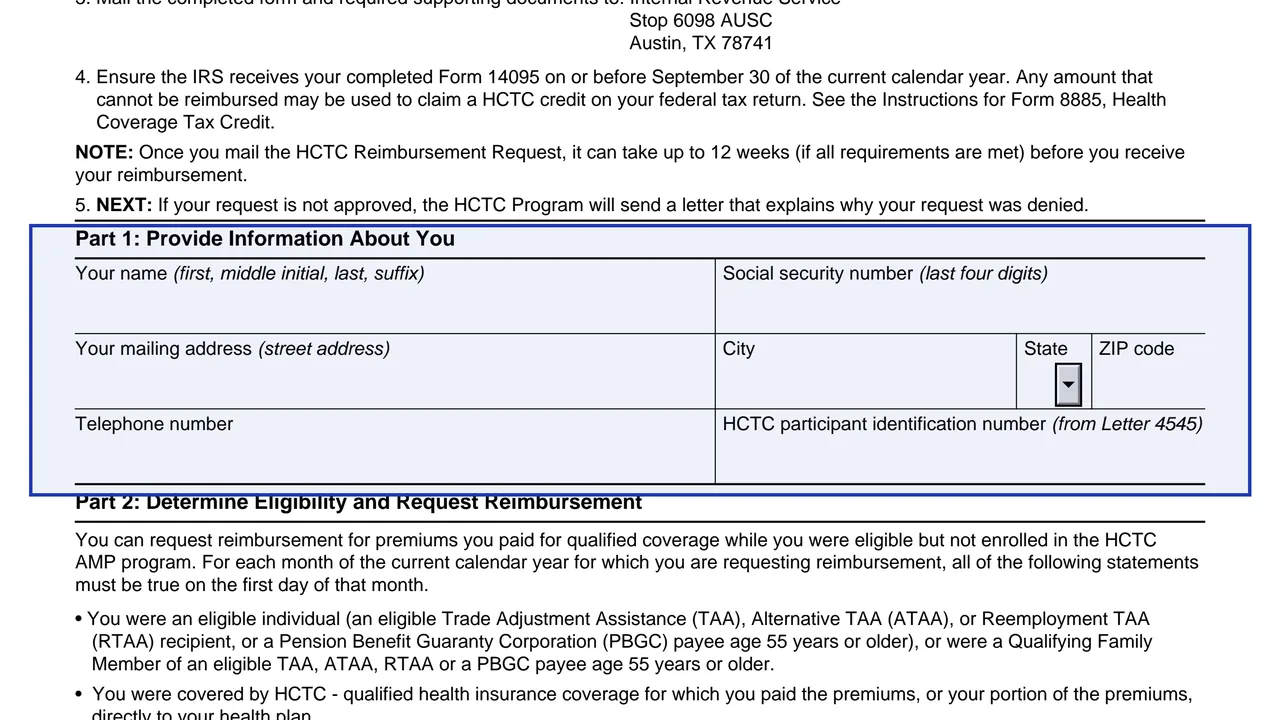
Part 1: information about you
Name, the last four digits of the Social Security number, mailing address, telephone number and the HCTC participant identification number from Letter 4545.
14095
The Health Coverage Tax Credit (HCTC) Reimbursement Request

Form 14095 is The Health Coverage Tax Credit (HCTC) Reimbursement Request. The form says to use it to request a reimbursement for premiums paid directly to a qualified health plan for any month in the current calendar year while eligible for but not enrolled in the HCTC Advanced Monthly Payment (AMP) program.
The form adds that the IRS can consider a request only if the person is eligible to participate in the HCTC AMP program in the coverage month requested and has made at least one premium payment through the program in the current calendar year. The request is figured on page 2, where line 6 multiplies the qualifying premiums by 72.5% (0.725).
The form is mailed with copies of health insurance bills and proof of payment. Its own instructions are printed on page 1. You can fill out the PDF free in your browser on this page and download it without an account.

Name, the last four digits of the Social Security number, mailing address, telephone number and the HCTC participant identification number from Letter 4545.
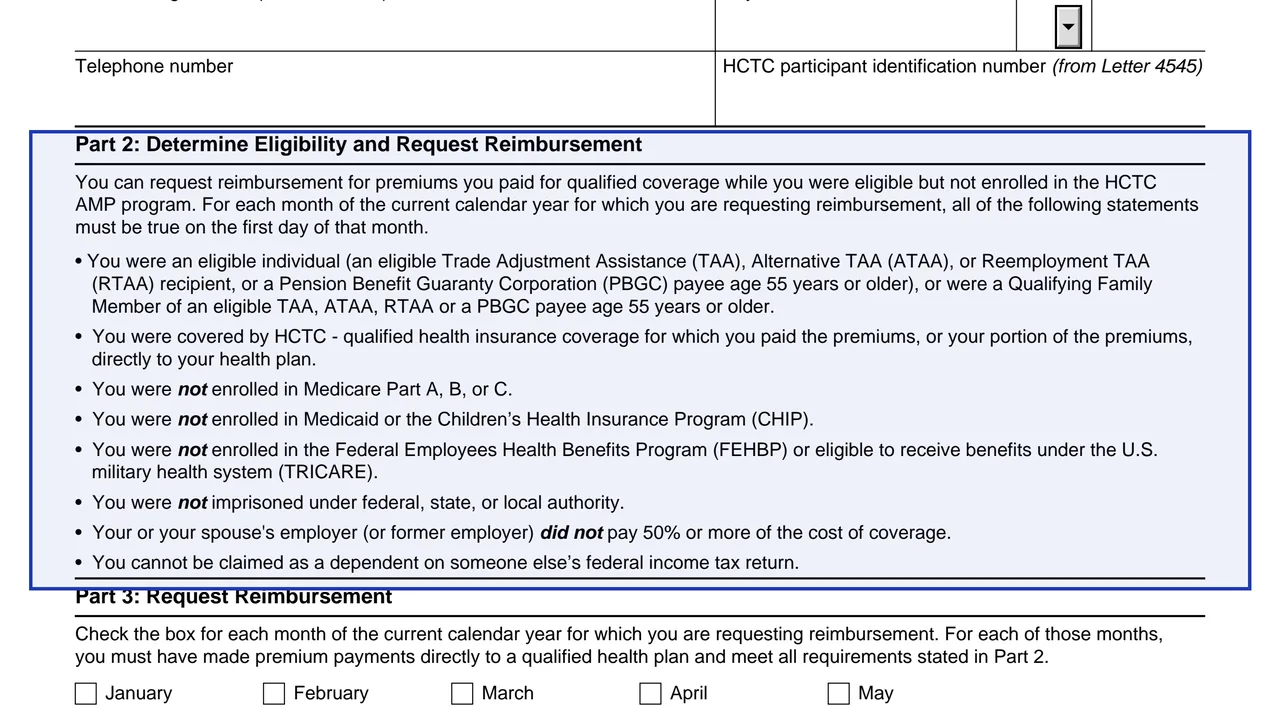
Eight statements about eligibility and coverage that the form says are true on the first day of each month requested.
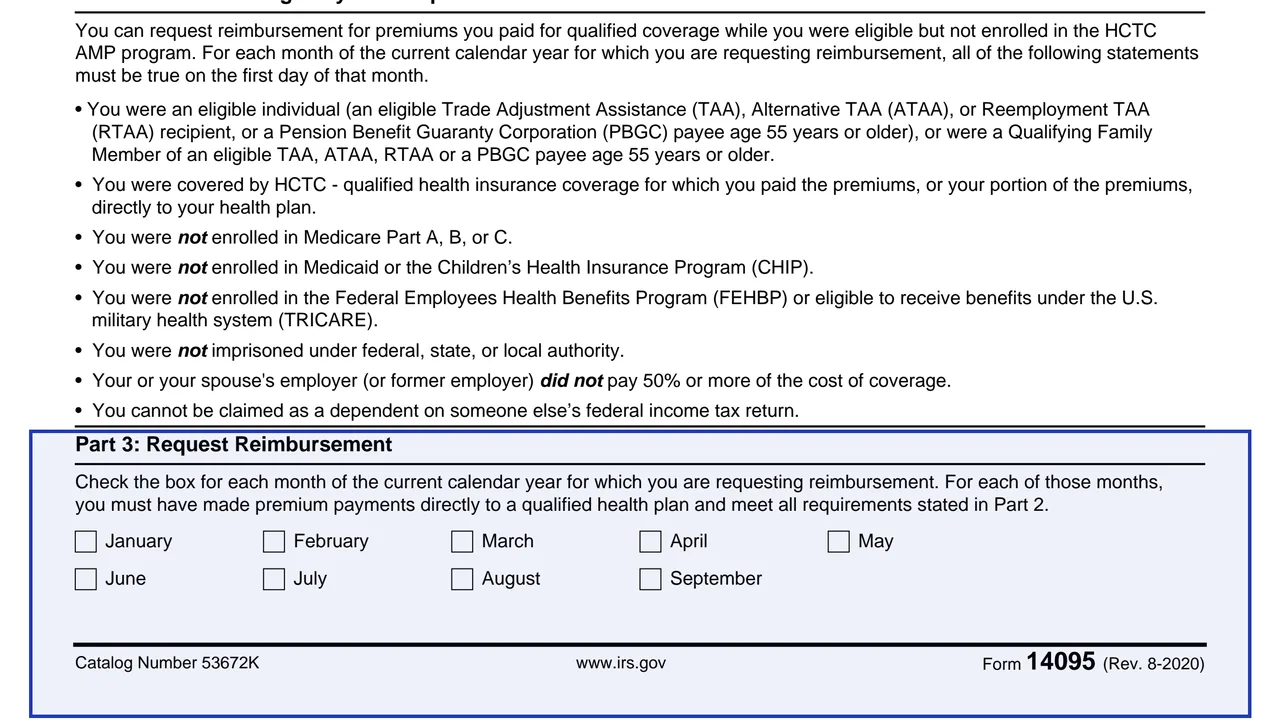
Check boxes for January through September of the current calendar year.
Premiums paid, minus dental or vision amounts and amounts for family members who do not qualify, then line 6 multiplies the result by 72.5% (0.725).
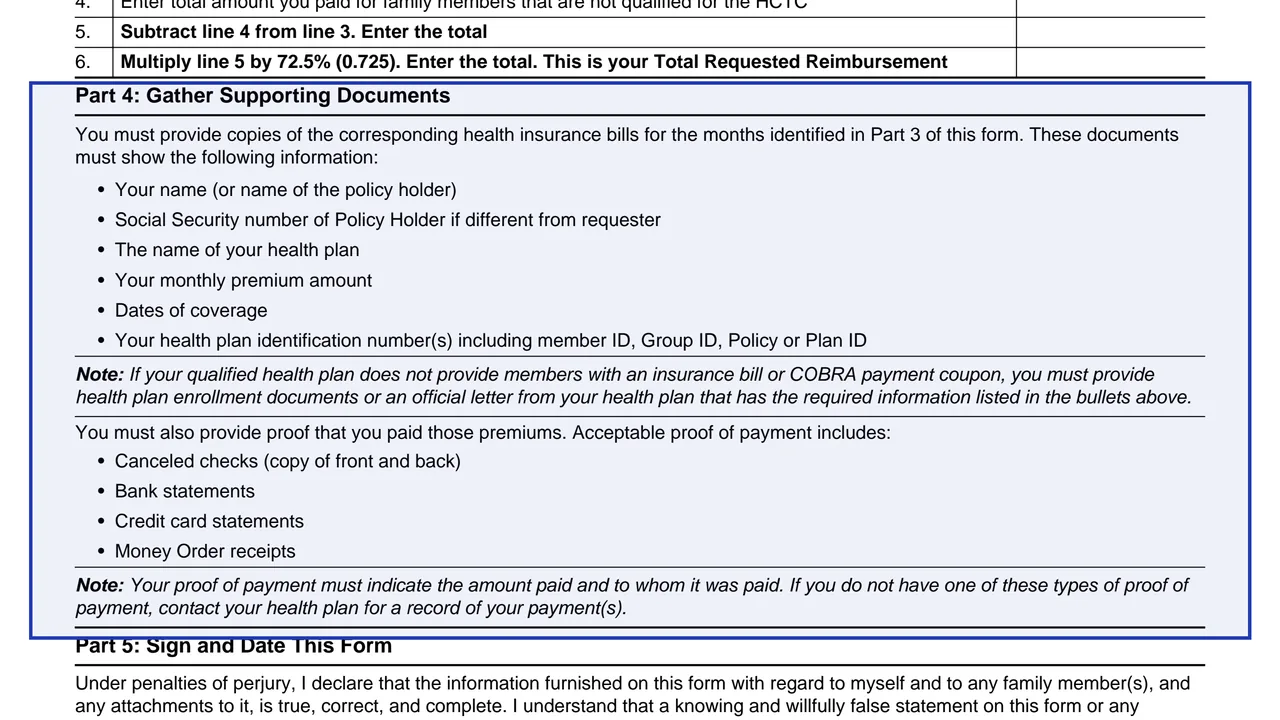
Copies of health insurance bills with the listed details, and proof that the premiums were paid.
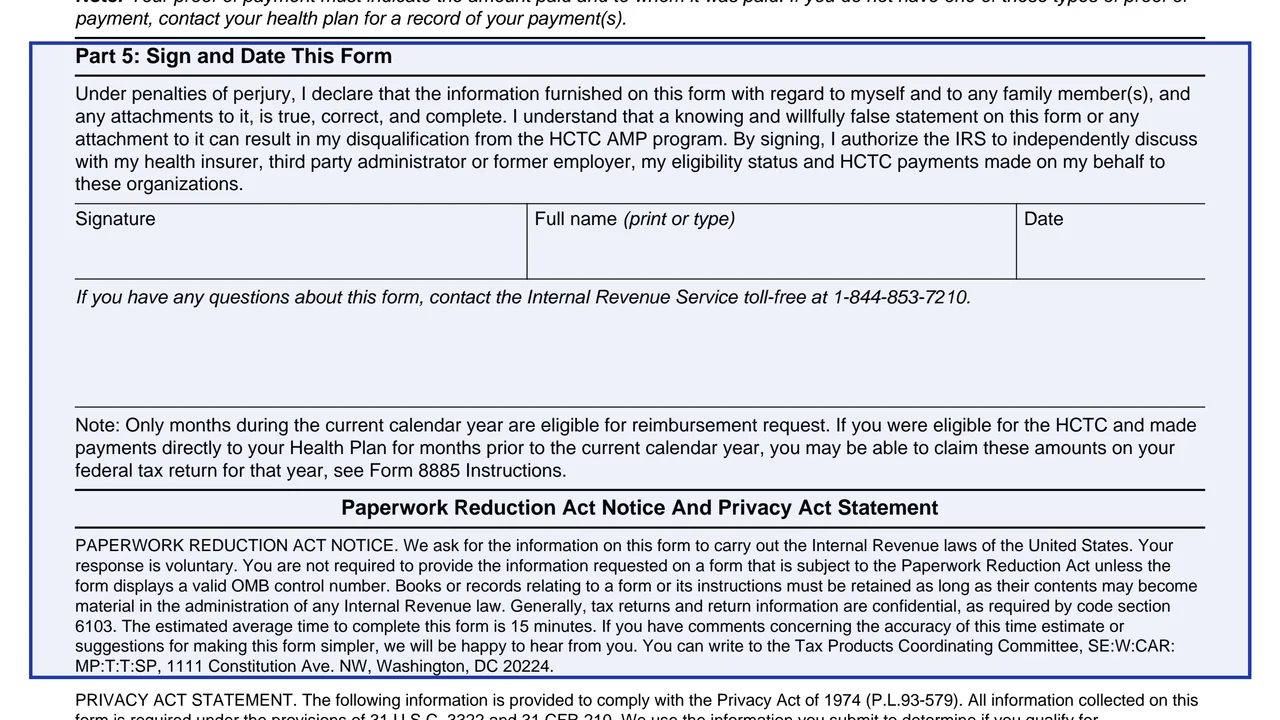
A penalties of perjury declaration and an authorization for the IRS to discuss eligibility with the health insurer, third party administrator or former employer.
The form says to print or type the responses and complete all parts. Enter the name, last four Social Security number digits, address, phone and the participant number from Letter 4545.
Read the eight statements. The form says all of them are true on the first day of each month for which reimbursement is requested.
Check the box for each month of the current calendar year with premiums paid directly to a qualified health plan.
Enter the total paid to the plan, subtract dental or vision amounts, subtract amounts for family members who do not qualify, and multiply line 5 by 72.5% (0.725) for the Total Requested Reimbursement.
Attach bills showing the policy holder, plan name, monthly premium, coverage dates and plan ID numbers, plus proof of payment such as canceled checks (front and back), bank or credit card statements, or money order receipts.
Sign, print the full name and date the form.
You get the real form, filled in a browser tab, with nothing standing between you and the finished PDF.
The form gives the address as Internal Revenue Service, Stop 6098 AUSC, Austin, TX 78741, with the supporting documents.
The form says the IRS should receive it on or before September 30 of the current calendar year.
The form says it can take up to 12 weeks (if all requirements are met) before the reimbursement arrives.
The HCTC Program sends a letter that explains why the request was denied.
The form says any amount that cannot be reimbursed may be used to claim a HCTC credit on the federal tax return, and points to the Instructions for Form 8885.
The form lists the Internal Revenue Service toll-free number 1-844-853-7210.
The person requesting the reimbursement completes and signs it. Part 2 lists the statements the form says are true on the first day of each month requested.
No tool matches that search.
Line 6 multiplies the qualifying total on line 5 by 72.5% (0.725). The form calls the result the Total Requested Reimbursement.
Only months in the current calendar year. Part 3 has boxes for January through September. For earlier years, the form points to the Instructions for Form 8885.
No. Line 2 says dental and vision benefits do not qualify for the HCTC, so they are subtracted.
The form says the IRS should receive it on or before September 30 of the current calendar year.
The form says up to 12 weeks after mailing, if all requirements are met.
The form lists canceled checks (copy of front and back), bank statements, credit card statements and money order receipts, showing the amount paid and to whom.